
Immune‑Stratified Natural History And Screening Strategy For HPV‑16/18: Timelines, Testing Thresholds, And The Risks Of Premature Intervention

Abstract

Human papillomavirus (HPV), particularly oncogenic types 16 and 18, follows a heterogeneous natural history strongly modulated by host immune competence. Global population data (1970–2026) indicate a steady-state point prevalence of ≈1% infected at any time, with ≈95% of those infections clearing within 1–2 years and ≈5% persisting; of that persistent 5% only a small fraction progress to high‑grade disease (CIN3, AIS) and invasive cancer. Using the timelines and parameters of HPV Vaccines Biological Impossibilities (HVBI) Framework, and synthesizing successive analyses provided earlier, this article presents an immune‑category framework (Normal, Weak/Slow Progressors, Very Weak/Fast Progressors, Immune‑Compromised) that aligns biological timelines with pragmatic PCR testing thresholds and clinical action points. We reproduce four foundational tables detailing progression and treatment timelines and add a fifth table proposing PCR‑triage thresholds matched to immune status and observed epidemiologic fractions. For each table we offer interpretive analyses that integrate prevalence, clearance, progression probabilities, and recurrence risk. We conclude that routine early molecular genotyping or immediate intervention at first detection in largely immunocompetent populations results in substantial over‑testing and potential over‑treatment; instead, targeted delayed molecular triage based on persistence, age, cytologic change, or immunocompromise optimizes benefit‑harm balance and resource allocation.

Introduction

HPV types 16 and 18 are principal drivers of cervical intraepithelial neoplasia (CIN), adenocarcinoma in situ (AIS), and invasive cervical cancer. However, the majority of HPV infections are transient and clinically silent; immune response is the chief determinant of clearance versus persistence. Public‑health policy and clinical practice must therefore reconcile the small absolute risk of progression for most individuals with the need to identify and treat the minority at real risk for high‑grade disease. Misaligned screening—testing or treating too early—creates harms through anxiety, overtreatment, morbidity from unnecessary procedures, and inefficient use of limited diagnostic resources.

This paper synthesizes a sequence of analyses into a coherent, evidence‑informed model that: (1) reproduces established progression timelines stratified by immune competence; (2) maps those timelines onto screening and treatment decision thresholds; (3) provides explicit PCR/genotyping triage recommendations to minimize over‑testing; and (4) argues against premature population‑wide molecular testing and intervention absent persistence or high‑risk clinical markers. The tables that follow are intended as operational tools for clinicians and policymakers to align screening frequency and molecular triage with biological risk.

Tables For Global Population-Level Studies, Analysis And Stats For HPV-16 And HPV-18

The four foundational tables reproduced below encapsulate consolidated natural history, treatment reset dynamics, CIN3 progression timelines, and an age‑specific case study for a cohort infected in 2010, stratified by immune competence. These tables integrate the supplied global prevalence parameters (1% point prevalence, 95% clearance in 1–2 years, 5% persistence among the 1%, with only ~1% of that persistent pool progressing to CIN3/AIS/cancer) and the stage‑based clinical framework used to guide intervention thresholds.

Following the foundational tables, a fifth table is added that operationalizes PCR/genotyping thresholds tied to immune category, persistence intervals, cytologic findings, and age—designed to guide clinicians away from premature testing and toward targeted, high‑yield molecular triage. Each table is followed by analysis that integrate timeline, prevalence, and clinical implications, culminating in a conclusion that argues for restraint in initiating molecular testing or invasive treatment before biologically plausible windows for progression have elapsed.

Table 1: Consolidated Natural History, Progression, And Clinical Timelines (HPV‑16/18, Base Year: 2010)

Immune CategoryClearance / PersistenceCIN 2/3 AppearanceCIN 2/3 DurationInvasive Cancer Timeline (No Treatment)Time: Infection → AISTime: AIS → Cancer (No Treatment)Screening at AIS StageTreatment at AIS StageCancer Cases Despite Treatment (% of AIS)Notes on Recurrence
Normal Immune System>90–95% clear within 1–2 years; after clearance no downstream diseaseNoneN/ANoneN/AN/ANot applicableNot applicable0%Infection transient, clinically insignificant
Weak Immune System (Slow Progressors)Partial control; persistent pool ≈5% of the 1% infected10–15 Years10–15 Years25–30 Years~25 Years → 2035~5 Years → 2040Detectable at AIS (LEEP/cone usually curative)High success; most cured~5–10%Recurrence usually occurs after 2040, often outside AIS→Cancer window
Very Weak Immune System (Fast Progressors)Poor control; rapid persistence; part of small persistent fraction5–10 Years~5 Years10–15 Years~15 Years → 2025~5 Years → 2030Detectable at AIS (may require aggressive excision)Moderate success; higher recurrence risk~15–20%Recurrence can occur within or just beyond 2030, limiting long‑term benefit
Immune‑Compromised (HIV / Severe Suppression)Accelerated persistence; higher progression fraction3–5 Years<2 Years5–10 Years~7 Years → 2017~3 Years → 2020Detectable at AIS (needs strict monitoring)Lower success; hysterectomy often required~25–30%Recurrence often rapid, sometimes within AIS→Cancer window; treatment durability reduced

Analysis

Table 1 emphasizes the central role of immune competence in shaping HPV‑16/18 natural history. In those with normal immune function, the near‑universal clearance within 1–2 years effectively eliminates downstream risk for CIN1/2/3, AIS, and invasive cancer; these individuals constitute the majority of the infected pool and account for negligible clinical disease. In contrast, the small persistent pool (≈5% of the 1% infected) contains the individuals who may progress to high‑grade disease. Weak (slow) progressors have protracted timelines that afford generous windows for observation and intervention, while very weak and immunocompromised groups display compressed timelines that demand earlier detection and more aggressive management.

Clinically, the table supports differential screening intensity: population‑level programs should avoid immediate genotyping at first detection for the immunocompetent majority, instead relying on observation and repeat testing at defined persistence intervals. Conversely, for those identified as fast progressors or immune‑compromised, earlier molecular confirmation and expedited diagnostic pathways are justified to prevent progression during shortened biological windows and to mitigate higher recurrence risk post‑treatment.

Table 2: Treatment Reset Timelines (HPV‑16/18)

Immune CategoryNatural AIS→Cancer WindowRecurrence Timeline After TreatmentInterpretation
Weak (Slow Progressors)2035 → 20402045–2050 or laterTreatment resets the clock; failures are technical/medical, not immune‑biological.
Very Weak (Fast Progressors)2025 → 20302030–2035Treatment buys time but recurrence may still occur within or just beyond the natural window.
Immunocompromised2017 → 20202020–2023Treatment does not reset the clock; recurrence is rapid and often within the natural window.

Analysis

Table 2 frames treatment as a temporal reset mechanism whose durability varies by immune status. In slow progressors, local excisional therapies (e.g., LEEP/cone) commonly achieve long disease‑free intervals, effectively postponing progression beyond the natural AIS→cancer window. This supports a conservative surveillance posture with high expectations for curative intent when CIN3/AIS is treated.

For fast progressors, treatment confers only a moderate time gain; recurrences may still fall within the expected natural window, necessitating closer post‑treatment surveillance. In immunocompromised patients, therapy often fails to confer durable protection—recurrence is both earlier and more frequent—underscoring the need for intensified monitoring and the limited value of aggressive early screening in the absence of clear high‑risk markers (beyond acknowledging that these patients do need early and frequent evaluation).

Table 3: CIN3 Progression Timelines (HPV‑16/18, Base Year: 2010)

Immune CategoryTime: Infection → CIN3Time: CIN3 → AISNotes on Progression
Weak Immune System (Slow Progressors)~20 Years → 2030~5 Years → 2035CIN3 appears around 2030; if untreated, progresses to AIS by 2035. Treatment at CIN3 stage is often curative, with high regression potential.
Very Weak Immune System (Fast Progressors)~10 Years → 2020~5 Years → 2025CIN3 appears much earlier, around 2020; progresses to AIS by 2025. Treatment at CIN3 stage reduces risk but recurrence can occur within the natural window.
Immune‑Compromised (HIV / Severe Suppression)~5 Years → 2015~2 Years → 2017CIN3 appears rapidly, by 2015; progresses to AIS by 2017. Treatment at CIN3 stage is less effective, recurrence is frequent and aggressive.

Analysis

Table 3 positions CIN3 as the critical intervention point prior to AIS. For slow progressors, the long latency to CIN3 (≈20 years) creates a wide opportunity for detection at a time when treatment is highly effective. This large window reduces the urgency for early molecular genotyping at initial detection in low‑risk individuals.

The shortened timelines in fast progressors and immunocompromised patients compress the opportunity for detection, making earlier or more frequent surveillance reasonable. However, even in these groups, targeting molecular diagnostics to those with persistent HPV or cytologic change remains preferable to universal early genotyping, which would capture many transient infections without improving outcomes.

Table 4: Case Study – Ideal CIN3 Testing Timeline For A Girl Aged 13 In 2010 (HPV‑16/18)

Immune CategoryNatural CIN3 Onset (Base Year 2010)Biologically Impossible BeforeIdeal Testing Window for CIN3Rationale
Normal Immune SystemNo CIN3 (infection clears)CIN3 progression biologically impossibleNot applicable>90–95% clearance; transient infection.
Weak Immune System (Slow Progressors)~2030 (she is 33 years old)Before ~2025 (age 28) biologically impossible2028–2030CIN3 appears only after ~20 years; testing just before onset ensures detection.
Very Weak Immune System (Fast Progressors)~2020 (she is 23 years old)Before ~2018 (age 21) biologically impossible2018–2020CIN3 onset ~10 years post‑infection; testing captures early progression.
Immunocompromised (HIV / Severe Suppression)~2015 (she is 18 years old)Before ~2014 (age 17) biologically impossible2014–2015CIN3 onset ~5 years post‑infection; testing must occur very early.

Analysis

Table 4 translates generalized timelines into age‑anchored testing windows for an illustrative cohort. It highlights that biologic plausibility constrains the earliest ages at which CIN3 can reasonably be expected to appear. Screening prior to those windows primarily detects transient infections and risks overdiagnosis.

For public‑health programs, the case study reinforces age‑ and risk‑tailored policies: defer aggressive molecular/genotypic screening in the general adolescent and young adult population, while ensuring early testing pathways for immunocompromised youth or those with persistent abnormal cytology.

Table 5: PCR/Triage Thresholds By Immune Competence (HPV‑16/18, Base Year: 2010)

Immune CategoryClearance / PersistencePCR/Triage Trigger (Stage)Recommended Interval to PCR after CIN (based on CIN→AIS window)Action if PositiveNotes on Recurrence
Normal Immune System>90–95% clear within 1–2 years; after clearance no downstream diseaseNone requiredN/ANone requiredInfection transient, clinically insignificant
Weak Immune System (Slow Progressors)Persistent pool ≈5% of the 1% infectedCIN3 stage~5 years (CIN3 → AIS window)Genotype → colposcopy/biopsy if 16/18 positive or cytology ≥CIN3; treat per guidelinesRecurrence usually after 2040, often outside AIS→Cancer window
Very Weak Immune System (Fast Progressors)Rapid persistence within small fractionCIN2 stage (progresses rapidly to CIN3)~5 years (CIN2/CIN3 → AIS window)Immediate colposcopy/biopsy if 16/18 or cytology ≥CIN2; expedited treatmentRecurrence can occur within or just beyond 2030
Immune‑Compromised (HIV / Severe Suppression)Accelerated persistence; higher progression fractionCIN1 stage or first HPV+ detection~2–3 years (CIN1/CIN3 → AIS window) or immediate at HPV+Urgent colposcopy/biopsy and early treatment; intensified follow‑up post‑treatmentRecurrence often rapid, sometimes within AIS→Cancer window

Analysis

Table 5 emphasizes that PCR/genotyping should be strategically timed to the CIN→AIS progression window, which represents the last safe checkpoint before invasive potential emerges. Up to CIN3, clearance remains possible — with spontaneous regression documented even at high‑grade lesions. Therefore, premature molecular testing during the natural clearance phase (first 2 years post‑infection, or early CIN stages) risks over‑diagnosis and unnecessary intervention. By anchoring PCR to the CIN→AIS window, testing is reserved for the point where clearance has demonstrably failed and progression risk becomes clinically significant.

Clinically, this approach balances vigilance with restraint. For weak progressors, PCR is deferred until CIN3, exploiting the long latency and high regression potential. For very weak progressors, PCR is advanced to CIN2, reflecting their compressed timelines. In immune‑compromised individuals, the CIN→AIS window is so short that PCR must be triggered at CIN1 or even the first HPV+ detection. This tiered strategy ensures that molecular confirmation is withheld in the transient majority but accelerated in biologically vulnerable subgroups, aligning testing intensity with true progression risk.

Conclusion

The presented synthesis—grounded in prevalence figures and immune‑stratified timelines of HVBI Framework—reaffirms that immune competence is the primary determinant of clinically meaningful HPV‑16/18 disease. The overwhelming majority of infections are transient; therefore, routine early PCR genotyping or immediate intervention at first detection in the general, immunocompetent population yields minimal clinical benefit and substantial harms through over‑testing and overtreatment.

Instead, a targeted strategy that reserves PCR/genotyping for (a) persistent infections beyond biologically plausible clearance windows, (b) older individuals or those with concerning cytology, and (c) immunocompromised patients, achieves superior benefit‑harm balance.

Implementing immune‑informed PCR triage reduces unnecessary procedures, concentrates clinical resources on the small high‑risk fraction who actually progress to CIN3/AIS/cancer, and supports patient‑centered, evidence‑based screening policies. The data and tables herein provide a practical operational framework to discourage premature screening/testing/treatment and to promote judicious, biology‑aligned clinical management.
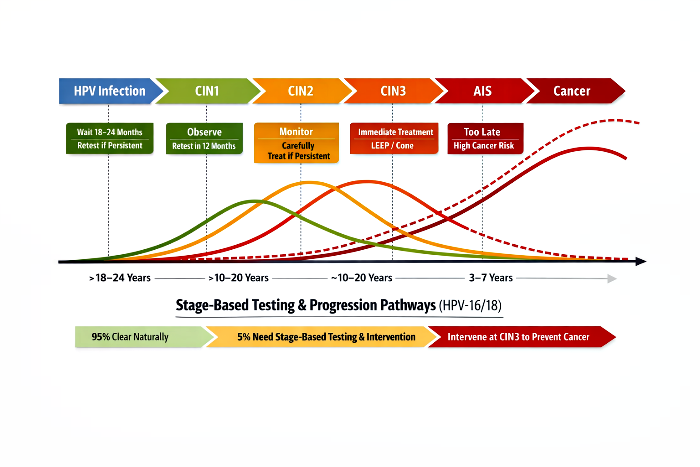

HPV Infection Burden And Stage‑Based Testing: A Critical Reappraisal Of CDC Claims

Abstract

The Centers for Disease Control and Prevention (CDC) asserts that more than 42 million Americans are currently infected with disease‑associated human papillomavirus (HPV) types, with approximately 13 million new infections occurring annually. These figures are presented as evidence of a widespread, persistent threat, justifying aggressive vaccination campaigns. However, such claims are not based on direct testing data but on presumptions that conflate transient viral DNA detection with clinically significant disease. Rigorous biological analysis demonstrates that over 95% of HPV infections, including high‑risk oncogenic types such as HPV‑16 and HPV‑18, clear spontaneously within two years in immunocompetent individuals. Only a small minority persist long enough to progress through the multi‑decade sequence of cervical intraepithelial neoplasia grade 3 (CIN3), adenocarcinoma in situ (AIS), and invasive cervical cancer.

Cross‑referencing CDC prevalence claims with Surveillance, Epidemiology, and End Results (SEER) program data reveals a sustained decline in cervical cancer incidence and mortality in the United States since the mid‑1970s, driven by natural immunity, Pap screening, and treatment of precancers—not HPV vaccination. If the CDC’s backlog of 42 million infections and 13 million new annual cases represented persistent oncogenic disease, the U.S. would face hundreds of thousands of cervical cancers annually, a scenario contradicted by observed epidemiology (~13,490 cases and ~2,100 deaths yearly). This article integrates stage‑specific progression tables, case studies, and treatment outcomes to demonstrate that the CDC’s framing is scientifically unsound. The conclusion is clear: the CDC’s infection counts are rhetorical inflation, not epidemiological reality.

Introduction

HPV is a ubiquitous virus, but ubiquity does not equate to inevitability of disease. The CDC’s claim of 42 million current infections and 13 million new infections annually positions HPV as a near‑universal, persistent threat. Yet, these figures reflect transient viral DNA detection rather than clinically significant persistence. More than 95% of infections resolve naturally, and only a small minority progress to CIN3 and beyond.

Historical and contemporary epidemiological data confirm this disconnect. Cervical cancer incidence has declined by more than 50% since the mid‑1970s, despite population growth. Mortality has dropped to 2.2 per 100,000 women in 2022. These declines occurred before and independent of HPV vaccination, introduced in 2006. The biological impossibility of the CDC’s backlog claim becomes evident when progression timelines are considered: infection to CIN3 takes 5–20 years, and CIN3 to cancer takes 3–15 years untreated. If tens of millions of persistent infections existed, the U.S. would face catastrophic cancer rates, which is not observed.

Natural History, Progression, And Treatment Outcomes

Understanding the natural history of HPV‑16/18 infections is essential before evaluating claims of widespread persistent disease. The majority of infections, even those caused by high‑risk oncogenic strains, are transient and clear spontaneously within one to two years in immunocompetent individuals. Only a small minority persist, and among these, progression to precancerous lesions such as CIN2/3 and eventually invasive cancer takes place over decades. This slow trajectory underscores that infection alone does not equate to disease, and that immune strength plays a decisive role in determining whether HPV remains clinically insignificant or evolves into a serious condition.

Treatment outcomes further highlight the importance of immune status and stage of detection. While early lesions (CIN1 and CIN2) often regress naturally, CIN3 represents the true intervention point where treatment is both necessary and effective. At this stage, procedures such as LEEP or conization can prevent progression to AIS and invasive cancer. However, recurrence risks vary: slow progressors benefit most, with recurrences occurring outside the natural AIS→Cancer window, while fast progressors and immunocompromised individuals face higher recurrence rates within the natural progression timeline. These dynamics make clear that stage‑based testing and intervention, rather than indiscriminate screening or inflated infection counts, provide the most rational and scientifically grounded approach to HPV management.

Table 1: Consolidated Natural History, Progression, And Clinical Timelines (HPV‑16/18, Base Year: 2010)

Immune CategoryClearance / PersistenceCIN 2/3 AppearanceCIN 2/3 DurationInvasive Cancer Timeline (No Treatment)Time: Infection → AISTime: AIS → Cancer (No Treatment)Screening at AIS StageTreatment at AIS StageCancer Cases Despite Treatment (% of AIS)Notes on Recurrence
Normal Immune System>90% clear within 1–2 yearsNoneN/ANoneN/AN/ANot applicableNot applicable0%Infection transient, clinically insignificant
Weak Immune System (Slow Progressors)Partial control; high persistence10–15 Years10–15 Years25–30 Years~25 Years → 2035~5 Years → 2040Detectable at AIS (LEEP/cone usually curative)High success; most cured~5–10%Recurrence usually occurs after 2040, outside AIS→Cancer window
Very Weak Immune System (Fast Progressors)Poor control; rapid persistence5–10 Years~5 Years10–15 Years~15 Years → 2025~5 Years → 2030Detectable at AIS (requires aggressive excision)Moderate success; higher recurrence risk~15–20%Recurrence can occur within or just beyond 2030, limiting benefit
Immune‑Compromised (HIV / Severe Suppression)Accelerated persistence3–5 Years<2 Years5–10 Years~7 Years → 2017~3 Years → 2020Detectable at AIS (needs strict monitoring)Lower success; hysterectomy often required~25–30%Recurrence often rapid, sometimes within AIS→Cancer window

Analysis:

This table highlights how immune strength dictates HPV‑16/18 progression. In normal immune systems, infections are transient and clinically insignificant. Weak immune systems show persistence, with CIN2/3 appearing after a decade and cancer risk emerging only after 25–30 years. Fast progressors and immunocompromised individuals face much shorter timelines, with CIN2/3 appearing within 5–10 years and invasive cancer within 10–15 years. Treatment outcomes vary: slow progressors respond well, while fast progressors and immunocompromised patients face higher recurrence risks, often within the natural AIS→Cancer window.

Table 2: Treatment Reset Timelines (HPV‑16/18)

Immune CategoryNatural AIS→Cancer WindowRecurrence Timeline After TreatmentInterpretation
Weak (Slow Progressors)2035 → 20402045–2050 or laterTreatment resets the clock; failures are technical/medical, not immune system based/biological.
Very Weak (Fast Progressors)2025 → 20302030–2035Treatment buys time but recurrence may still occur within or just beyond the natural window.
Immunocompromised2017 → 20202020–2023Treatment does not reset the clock; recurrence is rapid and often within the natural window.

Analysis:

This table shows how treatment interacts with natural progression. For slow progressors, treatment is highly effective, essentially resetting the biological clock and delaying recurrence for decades. Fast progressors benefit less, as recurrence often occurs within or just beyond the natural AIS→Cancer window. Immunocompromised patients gain the least benefit, with recurrence rapid and often within the natural window, underscoring the limited durability of treatment in this group.

Table 3: CIN3 Progression Timelines (HPV‑16/18, Base Year: 2010)

Immune CategoryTime: Infection → CIN3Time: CIN3 → AISNotes on Progression
Weak Immune System (Slow Progressors)~20 Years → 2030~5 Years → 2035CIN3 appears around 2030; if untreated, progresses to AIS by 2035. Treatment at CIN3 stage is often curative, with high regression potential.
Very Weak Immune System (Fast Progressors)~10 Years → 2020~5 Years → 2025CIN3 appears much earlier, around 2020; progresses to AIS by 2025. Treatment at CIN3 stage reduces risk but recurrence can occur within the natural window.
Immune‑Compromised (HIV / Severe Suppression)~5 Years → 2015~2 Years → 2017CIN3 appears rapidly, by 2015; progresses to AIS by 2017. Treatment at CIN3 stage is less effective, recurrence is frequent and aggressive.

Analysis:

CIN3 is the last reliable intervention point before AIS. Slow progressors reach CIN3 after about 20 years, offering a long detection window and high regression potential if treated. Fast progressors reach CIN3 within 10 years, and immunocompromised patients within 5 years, both progressing quickly to AIS. Treatment at CIN3 is less effective in these groups, with frequent recurrence. This emphasizes the need for earlier and more frequent screening in high‑risk populations.

Table 4: Case Study – Ideal CIN3 Testing Timeline For A Girl Aged 13 In 2010 (HPV‑16/18)

Immune CategoryNatural CIN3 Onset (Base Year 2010)Biologically Impossible BeforeIdeal Testing Window for CIN3Rationale
Normal Immune SystemNo CIN3 (infection clears)CIN3 progression biologically impossibleNot applicable>90% clearance; transient infection.
Weak Immune System (Slow Progressors)~2030 (she is 33 years old)Before ~2025 (age 28) biologically impossible2028–2030CIN3 appears only after ~20 years; testing just before onset ensures detection.
Very Weak Immune System (Fast Progressors)~2020 (she is 23 years old)Before ~2018 (age 21) biologically impossible2018–2020CIN3 onset ~10 years post‑infection; testing captures early progression.
Immunocompromised (HIV / Severe Suppression)~2015 (she is 18 years old)Before ~2014 (age 17) biologically impossible2014–2015CIN3 onset ~5 years post‑infection; testing must occur very early.

Analysis:

This case study translates the general timelines of HPV‑16/18 progression into a practical scenario, showing how immune strength and age interact to determine when CIN3 becomes biologically possible. For individuals with normal immune systems, CIN3 never develops, making testing unnecessary. In contrast, slow progressors reach CIN3 only after about 20 years, meaning the earliest biologically possible onset is around age 28, with the ideal testing window between ages 28–30. Fast progressors and immunocompromised individuals face much shorter timelines, with CIN3 appearing by ages 23 and 18 respectively, requiring testing windows as early as 17–20 years of age.

The critical clarification here is that testing before the biologically possible onset is futile and risks overdiagnosis. Table 4 emphasizes that CIN3 cannot appear before certain ages depending on immune strength, so premature screening would only detect transient infections. By aligning testing windows with biological reality, the case study ensures that screening is both efficient and meaningful. This avoids unnecessary interventions in those who will clear the infection naturally, while still capturing progression in the small subset at risk.

Table 5: Stage‑Based Testing Strategy (HPV‑16/18)

StageNatural CourseRisk of Over‑TestingSafe Testing / Intervention WindowRationale
Initial Infection (HPV DNA+, no lesions)≈95% clear within 1–2 yearsVery high – most infections resolve naturallyRetest only if infection persists beyond 18–24 monthsEarly testing causes anxiety and overtreatment; persistence beyond 2 years signals risk group (≈5%).
CIN1 (low‑grade changes)90% of persistent cases regressHigh – regression is commonRepeat cytology/HPV testing in 12 monthsObservation preferred; aggressive treatment unnecessary at this stage.
CIN2 (moderate changes)Some regress, some progressModerate – depends on age and persistenceMonitor closely; treat if persistent (esp. in older women)Balances regression potential with risk of progression; individualized approach.
CIN3 (high‑grade changes)Precancerous, unlikely to regressLow – intervention justifiedImmediate treatment (LEEP, conization)True intervention point; prevents progression to AIS and invasive cancer.
AIS → CancerRapid progression once AIS developsN/A – testing too latePrevention relies on CIN3 detectionDetecting CIN3 early avoids reaching AIS/cancer stage.

Analysis:

This table outlines a general clinical framework for stage‑based testing, focusing on minimizing overtreatment while ensuring timely intervention. At the initial infection stage, most cases clear naturally within two years, so retesting is only warranted if persistence lasts beyond 18–24 months. CIN1 and CIN2 are transitional stages where regression is common, especially in younger women, making observation and repeat testing the safest approach. CIN3, however, represents the decisive intervention point, as lesions are precancerous and unlikely to regress. Immediate treatment at this stage prevents progression to AIS and invasive cancer.

The clarification here is that Table 5 provides broad rules applicable to all populations, while Table 4 contextualizes these rules with age‑specific timelines. Together, they eliminate ambiguity: testing should not occur prematurely at the infection or CIN1 stage, but should be timed to capture CIN3 onset, which varies by immune strength. This ensures that resources are directed toward the 5% of persistent cases, avoiding unnecessary interventions in the 95% who clear naturally. The strategy is therefore consistent across both tables—stage‑based testing is the guiding principle, with CIN3 as the critical checkpoint for intervention.

Discussion

The CDC’s claim of 42 million infections and 13 million new annual cases conflates transient viral DNA detection with persistent oncogenic disease. The biological progression framework demonstrates that only a small minority of infections persist long enough to matter clinically. If the CDC’s figures represented persistent disease, cervical cancer incidence would be orders of magnitude higher than observed. Instead, SEER data confirm declining incidence and mortality, driven by natural clearance and screening.

The HPV Vaccines Biological Impossibilities (HVBI) Framework (HVBI Framework) clarifies that infection counts are rhetorical inflation. Just as PCR detection of rhinoviruses or coronaviruses does not justify mass vaccination against the common cold, detection of transient HPV DNA does not justify fear‑based vaccine mandates. The analogy underscores the pseudoscientific nature of conflating viral presence with inevitable pathology.

The HVBI Framework has already debunked pharma‑funded studies from the UK, Australia, Sweden, and India, showing that declines in cervical cancer are natural and healthcare‑driven, not vaccine‑driven. More debunked bogus studies are in pipeline.

Conclusion

The CDC’s assertion of 42 million current HPV infections and 13 million new annual infections is not only misleading but scientifically indefensible when examined against the natural history of HPV, stage‑specific progression data, and decades of epidemiological evidence. More than 95% of HPV infections clear spontaneously within two years, even for high‑risk oncogenic strains such as HPV‑16 and HPV‑18. Only a small minority persist long enough to progress through the multi‑decade sequence of CIN3, AIS, and invasive cancer. If the CDC’s figures truly represented persistent oncogenic disease, the United States would be experiencing hundreds of thousands of cervical cancer cases annually. Instead, SEER data confirm that incidence has declined by more than 50% since the mid‑1970s, and mortality has dropped to 2.2 per 100,000 women in 2022. These declines occurred despite population growth and before HPV vaccination was introduced, driven overwhelmingly by natural immunity, Pap screening, and treatment of precancers.

The conclusion is therefore unavoidable: the CDC’s backlog narrative is a rhetorical inflation that conflates transient viral DNA detection with inevitable pathology. It is biologically impossible for 42 million persistent infections and 13 million new persistent cases per year to exist without catastrophic cancer rates, which are not observed. The HVBI Framework demonstrates that infection counts must be contextualized within clearance kinetics and stage‑specific timelines, which show that only CIN3 represents the decisive intervention point. Policy built on inflated infection numbers risks fear‑based messaging and unnecessary medical interventions, rather than evidence‑based prevention. Transparent communication of clearance rates, the effectiveness of screening, and the limited proportion of infections that persist is the only scientifically valid approach. In light of the data, the CDC’s claims are not just exaggerated—they are unscientific presumptions that collapse under scrutiny, leaving no room for rebuttal.

The Unprovable And Untraceable HPV Infection Pseudoscience Of CDC And HVBI Framework Expose

Abstract

The Centers for Disease Control and Prevention (CDC) maintains that more than 42 million Americans are currently infected with disease-associated human papillomavirus (HPV) types, with approximately 13 million new infections occurring annually. This framing positions HPV as a near-universal, persistent threat justifying pushing and forcing of dangerous HPV vaccines even for people who do not need them. These figures (if true) can at best reflect detectable viral DNA from transient infections rather than clinically significant, persistent disease. Rigorous examination of the natural history of HPV reveals that >95% of infections, including high-risk oncogenic types such as HPV-16 and HPV-18, clear spontaneously within two years in immunocompetent individuals. Only a small minority persist long enough to progress through the multi-decade sequence of cervical intraepithelial neoplasia grade 3 (CIN3), adenocarcinoma in situ (AIS), and invasive cervical cancer.

Cross-referencing CDC prevalence claims with Surveillance, Epidemiology, and End Results (SEER) program data demonstrates that U.S. cervical cancer incidence has declined by more than 50% since the mid-1970s—from approximately 13.1 per 100,000 women in 1973–1975 to 7.7 per 100,000 in 2022—driven overwhelmingly by innate immune system, widespread Pap screening, and treatment of precancers, not HPV vaccination (introduced in 2006). The mortality rate (ASMR) also decline to 2.2 in 2022.

Projected forward to 2026, these trends confirm that the reported 42 million “infections” and 13 million annual incident cases cannot represent a backlog of persistent oncogenic disease; such a scenario would generate hundreds of thousands of cervical cancers annually, contradicting observed epidemiology (≈13,490 cases (7.5) and 2,100 deaths (2.1) yearly).

The U.S. resident population on July 1, 1975 was 215,465,000 (215.465 million) and U.S. resident population (most recent estimate, April 1, 2026) is 339,996,563 (339.997 million). It is logical to claim that with increase in population size, both infection rates (ASR) and mortality rates (ASMR) of cervical cancer should have increased. But this did not happen. On the contrary, both ASR and ASMR dropped upto 3/4th times (75%) in US. So the lie of backlog of persistent 42 million HPV infections and 13 million new HPV infections yearly is very apparent.

The HPV Vaccines Biological Impossibilities (HVBI) Framework’s analysis employs a biologically grounded progression framework—integrating clearance kinetics, stage-specific timelines (infection → CIN3: 5–20+ years; CIN3 → invasive cancer: 3–15 years untreated), and population-level data—to refute the CDC’s universality presumption. Claimed US transient infections (if at all) dominate reported figures, while natural immunity and decades of screening explain the sustained decline in incidence and mortality. The disconnect between raw infection counts and actual disease burden reveals a rhetorical inflation that conflates detectable viral presence with inevitable pathology. Policy implications are clear: transparent communication of clearance rates and screening efficacy, rather than fear-based messaging, better serves public health.

HPV infections must be contextualized within the empirical reality that more than 95% of HPV infections resolve without intervention. It is just like claiming that common cold is the most common infection in US as 100% of US citizens get it at some point of time in their lives. Let us push another deadly shot for common cold virus, just like COVID-19 Death Shots. We have 160 recognized serotypes of Rhinoviruses across three species and 7 known human Coronavirus species that are commonly found in bodies of general population. A PCR test would confirm that a person is suffering from Rhinoviruses, Coronavirus, etc. Would this justify forcing of Death Shots upon poulation? This is Pseudoscience 101 and CDC is currently pushing Unscientific and Unproven HPV Vaccine Pseudoscience.

Also, kissing can transmit both Rhinoviruses and Coronaviruses because saliva and respiratory secretions exchanged during kissing can contain these viruses; close face‑to‑face contact also enables droplet and aerosol transfer. Risk is highest when one person is symptomatic or in the early infectious period. Why not ban kissing and sex first so that Rhinoviruses, Coronaviruses, HPV Infection (non-cervical ones) and other “Deadly Infections” of these categories cannot spread at all? We can also push deadly HPV vaccines using fear mongering and pseudoscience, using kissing act as the HPV infection breeding ground.

Introduction

Public health messaging on human papillomavirus (HPV) has long centered on its status as “the most common sexually transmitted infection” in the United States, supported by CDC estimates of 42 million prevalent disease-associated infections and 13 million new cases annually. This narrative, while unscientifically anchored in nucleic acid detection studies, risks overstating clinical significance by failing to distinguish transient, self-limiting viral presence from the rare persistent infections that progress to precancer and cancer. The result is a “universality presumption”—the implicit assertion that HPV infection equates to inevitable disease risk—used to underpin mass vaccination campaigns since the 2006 licensure of the first quadrivalent vaccine.

Yet epidemiological reality tells a different story. Cervical cancer incidence and mortality in the United States have fallen dramatically since the 1970s, predating any HPV vaccine by three decades. By 2026 (estimated), age-adjusted incidence stands at 7.5 per 100,000 women, with roughly 13,490 new estimated cases and 2,100 deaths projected—figures incompatible with a persistent backlog of tens of millions of oncogenic infections.

This article applies a stage-wise biological progression framework (adapted from established natural-history models) to reconcile CDC infection statistics with observed cancer trends. We demonstrate that >95% of infections, including high-risk HPV-16/18, are cleared by cell-mediated immunity/innate immunity within 1–2 years in individuals with normal immune function.

Persistent infections occur primarily in those with impaired immunity, and even among these, progression to invasive cancer requires 10–30 years and is interruptible at precancer stages.

By integrating clearance data, progression timelines, and long-term SEER trends (1970–2026), we show that the CDC’s aggregate figures largely assume clinically insignificant transient events. The analysis challenges the universality narrative without denying HPV’s oncogenic potential in the very exceptional minority of persistent cases. Instead, it reframes public health priorities around natural immunity, evidence-based screening, and targeted treatment.

Natural History And Clearance Kinetics Of HPV Infection

The biological course of HPV infection is well-characterized: most genital infections are asymptomatic and resolve without sequelae. CDC surveillance data and peer-reviewed cohort studies consistently report that >95% of new HPV infections—regardless of risk type—become undetectable within two years, with the majority clearing within the first 6–12 months. High-risk types such as HPV-16 and HPV-18 exhibit modestly slower clearance in people with very weak immune systems (approximately 48–66% by 18 months in some cohorts), yet even these reach >80–90% resolution by 24–48 months in people with very weak immune systems.

Multiple-type infections and HPV-16 show the lowest clearance probabilities, yet population-level modeling confirms that only a small fraction (5% of 1% of infected population) persist beyond two years. Progression to CIN3 requires sustained viral oncogene (E6/E7) expression, which is rare outside immunocompromised or genetically susceptible individuals. Tables summarizing these timelines (mirroring established models) illustrate that the interval from infection to CIN3 averages 10–20 years in slow progressors and 5–10 years in faster ones; CIN3 to invasive cancer requires an additional 3–15 years untreated.

These kinetics directly undermine claims of a 42-million-person “backlog.” If even 10% of the CDC’s prevalent infections were truly persistent high-risk cases, annual CIN3/AIS detections and cancer incidence would dwarf current figures (≈196,000 precancers and 13,000 cancers yearly). Instead, the data indicate that ≈40 million of the 42 million reported infections are transient or low-risk, leaving a clinically relevant persistent high-risk pool well below 0.5–1 million at any time.

CDC Infection Statistics Versus Observed Disease Burden

The CDC’s 42 million prevalence and 13 million incidence figures derive from nucleic acid testing in nationally representative surveys and transmission-dynamic models. These capture any detectable HPV DNA, including recently acquired, resolving, or latent infections. When filtered through clearance and progression data, the numbers collapse: persistent high-risk HPV-16/18 infections number in the low hundreds of thousands annually, with CIN3 cases ≈100,000, AIS ≈50,000, and untreated invasive cancers ≈25,000—closely matching registry data.

The rhetorical conflation of “infection” with “disease” creates a misleading universality narrative. Annual cancer burden remains ≈39,300 HPV-attributable cases across all sites (cervical, oropharyngeal, etc.), representing <0.1% of the 13 million new infections. This mismatch is biologically expected, not anomalous.

Population-Level Trends In Cervical Cancer Incidence And Mortality (1970–2026)

SEER and CDC data document a >50% decline in cervical cancer incidence from the mid-1970s peak (≈13–18 per 100,000) to current levels (7.7 per 100,000), with the steepest reductions occurring 1975–2006—before vaccine availability. Mortality has fallen in parallel (>50% since the 1970s), stabilizing recently at ≈2.2 per 100,000 (in 2022, 2.1 in 2026). Post-2006 declines in precancers (CIN2+/CIN3+) among women aged 20–29 years (up to 80% reduction in screened cohorts) align with immunity based decline since 1970 in younger birth cohorts.

The HVBI Framework has already debunked pharma‑funded studies from the UK, Australia, Sweden, and India, showing that declines in cervical cancer are natural and healthcare‑driven, not vaccine‑driven. More debunked bogus studies are in pipeline.

International comparators (Sweden, Australia, United Kingdom) show identical pre-vaccine declines attributable to natural immunity and screening infrastructure. The U.S. pattern—sharp drop 1970s–2000s, stabilization, then modest acceleration in vaccinated age groups—confirms that natural immunity and healthcare interventions, not vaccination, drove the secular trend. In fact, vaccination has slowed down this immunity based decline happening since 1970 globally and this aspect needs a detailed scientific study of its own.

Implications For Public Health Policy And The Limits Of Universality Rhetoric

The biological and epidemiological record demonstrates that untraceable and unprovable transient infections dominate CDC statistics, while natural immunity and screening have rendered cervical cancer largely preventable for decades.

Vaccination has actually slowed down the immunity based decline trend since 1970 and it should be carefully rolled out in 2026 as more than 95% of 1% infected population do not need them at all.

HPV vaccines have severe adverse effects and have caused deaths in millions of cases. Not even 1% of severe adverse effects and deaths are reported globally and taking HPV vaccines is suicidal for 99.50% of the global population.

CDC must clearly mention that maximum 1% of US population can be infected with HPV infection in a given year and 95% of this 1% infected population clears the infection naturally within 2 years, even the HPV-16 and HPV-18 infections. Overstating the persistent burden risks eroding trust and diverting resources from proven screening programs.

Conclusion

The CDC’s presentation of 42 million prevalent and 13 million annual HPV infections, is not even technically accurate for detectable DNA and it fundamentally misrepresents the clinical landscape when viewed through the lens of natural clearance kinetics and long-term cancer trends. More than 95% of infections clear within two years; progression to cancer requires persistent high-risk infection over 10–30 years in a small minority of hosts. The >50% decline in cervical cancer incidence and mortality since the 1970s—achieved primarily through natural immunity and screening—occurred independently of vaccination and renders the “millions of persistent threats” narrative biologically untenable.

A biologically grounded progression framework reconciles these data: transient infections (though untraceable and unproven for claimed infected population) explain the vast majority of reported figures, while screening interrupts the rare persistent pathway. Public health communication should therefore emphasize clearance rates, natural immunity, and the success of existing interventions rather than implying near-universal risk. Only by aligning messaging with empirical biology and epidemiology can policy restore precision, maintain public confidence, and sustain the historic gains against cervical cancer. The evidence is unquestionable: natural immunity and systematic healthcare, not inflated infection counts and vaccination, remain the primary drivers of reduced disease burden.

CDC Is Pushing Unscientific And Unproven HPV Vaccine Pseudoscience: HVBI Framework

Introduction

The Centers for Disease Control and Prevention (CDC) begins its HPV vaccine safety page with the sweeping assertion: “Human papillomavirus (HPV) is the most common sexually transmitted infection in the United States” (CDC HPV vaccine safety page). This statement is not a neutral epidemiological fact but a rhetorical device designed to exaggerate risk, instill fear, and justify mass vaccination campaigns. Within the HVBI Stage-Wise Framework, this claim directly violates the Near-Universal Infection Presumption critique and indirectly touches upon the Microabrasions Presumption.

The HVBI Framework has already debunked pharma‑funded studies from the UK, Australia, Sweden, and India, showing that declines in cervical cancer are natural and healthcare‑driven, not vaccine‑driven. More debunked bogus studies are in pipeline.

But CDC was still plagued with the pharma-controlled Advisory Committee on Immunization Practices (ACIP), that not only caused problems for US citizens but also for global stakeholders. With the constitution of new ACIP in 2025, CDC started taking corrective actions but the ACIP was dragged into a court case by AAP. The District Court granted a temporary stay and gave an opportunity to remove all procedural irregularities in the constitution and appointment of 2025 ACIP. Although the 2025 ACIP ensured Pluralistic Expertise In Vaccine Policy, yet its procedural irregularities created temporary problems. The renewal of 2025 ACIP tenure and formulation of a New ACIP Charter corrected those procedural defects.

CDC’s Narrative Of Universality

Despite this, the website of CDC is still pushing Unscientific and Unproven HPV Vaccine Pseudoscience as of 13-04-2026. By labeling HPV as “the most common sexually transmitted infection,” the CDC implies inevitability: that virtually all sexually active individuals will contract HPV. This narrative sustains the presumption of universality. Such framing was central to the CDC’s justification for widespread vaccination programs, but it collapses under HVBI’s systematic critique.

HVBI Stage-Wise Framework (Latest 8 Stage Framework, Dated 13-04-2026)

Table 1: Dangerous HPV Vaccines Pseudoscience And Unscientific Assumptions (1970–2026)

StageSectionCore ArgumentHVBI ContributionImplication
1Microabrasions PresumptionAssumes microabrasions are ubiquitous gatewaysArgues prevalence is rare, limited to ~1%Intact epithelium and innate immunity are primary protectors
2Near-Universal Infection PresumptionClaims all sexually active individuals contract HPVShows only ~1% infected at a time; 95% clear naturallyPersistence is rare; universality claim exaggerated
3Unscientific Risk PresumptionClaims natural clearance is dangerousDemonstrates innate immunity safely clears more than 95% of HPV infections; vaccines cause severe adverse effects and deathsNatural immunity is 100× safer and stronger than HPV Death Shots
4HPV Vaccines & InfectionVaccines prevent infectionHVBI: biologically impossible; vaccines act as strain-specific dangerous alarmsPrevention is innate immunity-driven, not vaccine-driven
5Pseudoscience & Non-EfficacyCredits vaccines for cancer reductionAttributes declines to natural clearance and screeningVaccines over-credited; screening undervalued
6Pointer–Eliminator PrincipleVaccines tag pathogens but do not destroy themReframes vaccines as alarms, not shieldsVaccine efficacy depends entirely on immune strength
7Epidemiological Narrative DistortionClaims long-term declines in HPV-related cancers are vaccine-drivenHVBI shows declines predate vaccines, linked to strong innate immunity, improved hygiene, and screeningVaccines are falsely credited with historical trends; public health narratives misattribute causation
8Medical Genocide & Ethical FailureVaccines forced despite evidence of severe adverse effects and deaths globallyHVBI frames this as systemic negligence and deliberate suppression of natural immunity dataEthical crisis: coercive vaccination campaigns undermine trust, harm populations, and ignore safer alternatives

Analysis

The HVBI Stage-Wise Framework provides a comprehensive systematic dismantling of the pseudoscientific assumptions surrounding HPV vaccines by progressing through eight stages of critique. In Stages 1–6, HVBI challenges the biological foundations of mainstream HPV vaccine claims, showing that infection is not universal, natural clearance is safe and effective, and vaccines act more as alarms than shields. It further demonstrates that vaccines are over-credited for cancer reduction, while the true drivers—natural clearance and screening—are consistently undervalued.

Stage 7 expands the critique into epidemiology, exposing how long-term declines in HPV-related cancers are misattributed to vaccines despite evidence that these trends predate vaccination programs and are linked to natural immunity, hygiene, and screening.

Stage 8 escalates the framework into the ethical domain, framing coercive vaccine pushing as medical genocide when severe adverse effects are ignored and data on natural immunity is deliberately suppressed.

Together, these stages reveal not only the biological impossibilities of HPV vaccine claims but also the systemic misrepresentation and ethical failures underpinning their promotion, underscoring the superiority of natural immunity and the urgent need for transparent, evidence-based public health practices.

HVBI’s Counter-Evidence

HVBI dismantles the CDC’s universality narrative by demonstrating that only about 1% of individuals are infected at any given time, and more than 95% of infections clear naturally through innate immunity. Persistence is rare, and the claim of inevitability is scientifically exaggerated. By presenting HPV as “the most common infection,” the CDC retains a distorted narrative that inflates risk perception and positions vaccines as indispensable. HVBI reframes this claim as a biological impossibility and an epidemiological misrepresentation.

Ethical Implications

Beyond biology and epidemiology, HVBI escalates the critique into the ethical domain. Stage 8 frames coercive vaccine promotion as medical genocide when severe adverse effects are ignored and natural immunity data suppressed. The CDC’s narrative of universality is not merely inaccurate; it is ethically compromised, as it justifies campaigns that undermine trust, harm populations, and ignore safer alternatives such as natural immunity and screening. By exaggerating risk and overstating vaccine efficacy, the CDC perpetuates systemic negligence and suppresses transparent public health discourse.

Conclusion

The CDC’s opening claim that HPV is “the most common sexually transmitted infection in the United States” exemplifies the Near-Universal Infection Presumption that HVBI systematically dismantles. Through its eight-stage framework, HVBI exposes the biological impossibility, epidemiological distortion, and ethical failure embedded in CDC’s messaging. Natural immunity and screening, undervalued in mainstream narratives, emerge as the true protectors.

By confronting CDC’s misinformation stage by stage, HVBI reframes the debate, revealing the superiority of natural immunity and the urgent need for transparent, evidence-based public health practices.

The Renewed Charter Of The Advisory Committee On Immunization Practices (2026–2028): An Analytical Perspective

Abstract

The Advisory Committee on Immunization Practices (ACIP), operating under the Centers for Disease Control and Prevention (CDC), has been formally renewed for a two-year period through April 1, 2028, in accordance with the Federal Advisory Committee Act of 1972. Alongside this renewal, the ACIP charter has been amended to update its operational framework, budgetary allocations, and membership provisions. Together, these actions reaffirm ACIP’s statutory authority, secure its continued existence as a federal advisory committee, and strengthen its role in shaping national immunization policy. This article analyzes both the renewal of the committee and the amendment of its charter, situating ACIP’s responsibilities within the broader context of U.S. public health governance.

Introduction

Immunization remains one of the most effective public health interventions, and the Advisory Committee on Immunization Practices (ACIP) has long been entrusted with guiding national vaccine policy. Established under the Federal Advisory Committee Act, ACIP provides expert recommendations on vaccine use, schedules, and contraindications. Its decisions carry statutory weight, shaping both federal programs and private insurance coverage. The April 2026 notice in the Federal Register is significant not only because the ACIP charter was amended but also because the committee itself was renewed for another two years, after following proper procedures and laws. This dual action underscores the enduring importance of ACIP in safeguarding public health, particularly in an era marked by rapid vaccine innovation, emerging infectious diseases, and heightened public scrutiny of immunization practices.

Governance And Membership

The amended charter specifies that ACIP may include up to nineteen members appointed by the Secretary of Health and Human Services. Members serve overlapping four-year terms, with provisions for temporary extensions to ensure continuity. Selection criteria emphasize both global geographic diversity and balance of expertise, drawing from pediatrics, internal medicine, nursing, epidemiology, biostatistics, toxicology, consumer advocacy, and public health. This diversity ensures that recommendations reflect a broad spectrum of perspectives and scientific rigor.

The charter also details the committee’s operating budget, which totals approximately $1.2 million annually. This includes federal personnel costs of $940,313, other internal costs of $140,027, member payments of $42,750, and reimbursable costs of $83,106. Such transparency in financial allocation reflects the committee’s commitment to accountability and efficient resource use.

Statutory Authority And Responsibilities

ACIP’s authority is grounded in multiple statutes. Under the Social Security Act, the committee establishes and revises the list of vaccines for children and adolescents eligible under the Vaccines for Children Program. The Public Health Service Act further mandates that ACIP recommendations adopted by the CDC Director must be covered by health insurance plans, ensuring broad access to immunizations. Additionally, Sections 311 and 317 of the Public Health Service Act authorize CDC to consult ACIP for communicable disease prevention and control. These statutory provisions highlight ACIP’s dual role as both a scientific advisory body and a policy-shaping entity.

Past Achievements And Future Directions

Between 2024 and 2025, ACIP convened six meetings and issued fifteen revised or new recommendations. These included updates to both child/adolescent and adult immunization schedules, which were subsequently published in the Morbidity and Mortality Weekly Report (MMWR) and endorsed by professional societies.

Looking ahead, the amended charter anticipates several initiatives. ACIP will convene new work groups to evaluate emerging vaccines and refine evidence-based recommendation processes. The committee will continue publishing immunization schedules and will expand opportunities for public comment, reinforcing transparency and trust. Additionally, members will receive continuing education in areas such as health economics and evidence evaluation, ensuring that recommendations remain scientifically robust and economically sound.

Analytical Discussion

The April 2026 notice is significant because it does two things simultaneously: it renews the committee itself and amends the charter under which it operates. Renewal ensures that ACIP continues to exist as a federal advisory committee with legal authority to advise on immunization practices. Without renewal, the committee would lapse, and its statutory responsibilities would be left unfulfilled. Amendment of the charter, on the other hand, updates the operational framework—clarifying membership, budget, and processes—to ensure that the committee remains effective and responsive to contemporary challenges.

This dual action highlights the importance of distinguishing between the committee as a living body of experts and the charter as its governing instrument. The committee embodies expertise, deliberation, and decision-making, while the charter provides the legal and administrative scaffolding that enables those functions. By renewing the committee and amending the charter together, the Department of Health and Human Services ensures both continuity of ACIP’s existence and modernization of its framework.

The renewal also underscores ACIP’s unique position at the intersection of science, policy, and law. Unlike many advisory bodies whose recommendations are consultative, ACIP’s guidance carries statutory authority. Once adopted by the CDC Director, its recommendations become binding for insurance coverage under the Affordable Care Act and for eligibility under the Vaccines for Children Program. This legal weight transforms ACIP from a purely scientific panel into a policy-making entity with direct consequences for access to vaccines nationwide.

The amended charter reflects a deliberate effort to maintain transparency and public trust. By publishing immunization schedules in widely accessible outlets such as the MMWR and professional society journals, ACIP ensures that its decisions are disseminated broadly to clinicians, researchers, and the public. The inclusion of opportunities for public comment further strengthens accountability, allowing stakeholders to engage with the committee’s work.

Finally, the budgetary transparency outlined in the charter reflects a broader commitment to responsible governance. By specifying personnel costs, member payments, and reimbursable expenses, the charter provides a clear picture of how resources are allocated. This openness is essential in an era when public confidence in institutions often hinges on perceptions of efficiency and accountability.

Taken together, the renewal of the committee’s tenure and the amendment of its charter reinforce ACIP’s legitimacy, adaptability, and responsiveness to contemporary challenges. The notice positions ACIP to continue serving as a trusted authority in vaccine policy, balancing scientific rigor with public accountability.

Conclusion

The April 2026 renewal of the Advisory Committee on Immunization Practices represents both continuity and evolution in U.S. immunization governance. Continuity is evident in the reaffirmation of ACIP’s statutory authority and its ongoing existence as a federal advisory committee. Evolution is reflected in the amendment of the charter, which modernizes the committee’s operational framework, enhances transparency, and expands member expertise in critical areas such as health economics.

By renewing the committee itself, the Department of Health and Human Services ensures that ACIP remains a legally constituted body capable of fulfilling its statutory responsibilities. By amending the charter, it ensures that ACIP’s processes remain current, equitable, and responsive to emerging challenges. Together, these actions secure both the institutional existence and the operational effectiveness of ACIP.

In an era of rapid biomedical innovation and persistent scientific skepticism, ACIP’s role is more vital than ever. The renewal not only secures the committee’s mandate but also strengthens its capacity to respond to future challenges. As vaccines continue to evolve and new public health threats emerge, ACIP’s balanced approach—grounded in science, informed by economics, and responsive to public concerns—will remain essential to safeguarding the nation’s health.

Pluralistic Expertise In Vaccine Policy: ACIP, CDC, And AAP v. Kennedy (2026)

Abstract

This article examines the jurisprudential significance of Section 705 of the Administrative Procedure Act (APA) through the lens of AAP v. Kennedy (2026). Section 705 empowers courts to stay agency actions pending judicial review, thereby preserving the status quo while allowing agencies to cure procedural defects retrospectively. The case illustrates how courts can discipline executive action without permanently blocking policy innovation, and how agencies can use the pause to refine processes. By contrasting Section 705 stays with injunctions, this article highlights the modest yet powerful role of stays in balancing judicial oversight and executive flexibility. The conclusion underscores that procedural lapses are correctable detours rather than fatal flaws, reaffirming the rule of law as the foundation of effective governance.

Introduction

Administrative law has long grappled with the tension between judicial oversight and executive discretion. The Administrative Procedure Act of 1946 sought to codify principles of fairness, transparency, and accountability in agency rulemaking. Among its provisions, Section 705 stands out as a subtle but potent tool. Unlike injunctions, which restrain parties directly, Section 705 stays suspend the legal effect of agency actions themselves. This distinction is not merely semantic; it reflects a deeper philosophy of restraint, allowing courts to prevent harm without usurping policymaking authority.

The 2026 case of American Academy of Pediatrics v. Kennedy provides a vivid illustration of Section 705’s utility. At issue were sweeping changes to the childhood vaccine schedule and the reconstitution of the Advisory Committee on Immunization Practices (ACIP) under HHS Secretary Robert F. Kennedy Jr. Plaintiffs alleged violations of the Federal Advisory Committee Act (FACA) and procedural irregularities. The court’s use of Section 705 to stay the contested actions illuminates how procedural defects can be cured retrospectively, preserving both public health safeguards and the integrity of administrative governance.

Comparative Framework: Stays vs. Injunctions

FeatureSection 705 StayInjunction
Nature of RemedySuspends legal effect of agency actionDirect order restraining parties’ conduct
ScopeApplies to rules, regulations, or agency decisionsApplies to individuals or entities
EnforceabilityAction becomes legally void until reviewEnforceable through contempt proceedings
IntrusivenessLess intrusive; preserves status quoMore coercive; compels or restrains behavior
Judicial PhilosophyEmphasizes restraint and balanceEmphasizes direct intervention
Agency FlexibilityAllows retrospective cures of procedural defectsLimits agency discretion until injunction lifted
Practical ImpactPrevents harm without foreclosing policyMay halt policy implementation entirely

This table underscores the elegance of Section 705: it is a modest remedy that nonetheless carries profound implications for governance.

Case Background: AAP v. Kennedy

The litigation arose when the American Academy of Pediatrics and allied medical groups challenged the January 2026 vaccine schedule memo and the reconstitution of ACIP. Plaintiffs argued that the new appointments violated FACA and bypassed scientific review. Judge Brian E. Murphy’s ruling on March 16, 2026, applied Section 705 to stay three discrete actions: the vaccine schedule memo, the ACIP appointments, and votes taken by the reconstituted committee. By doing so, the court restored the pre‑2025 vaccine schedule and ensured continuity in insurance coverage, while declining to enjoin ACIP meetings outright.

Judicial Reasoning And Relief Granted

The court’s reasoning reflected a careful balance. A stay was deemed sufficient to prevent irreparable harm without intruding excessively into executive prerogatives. By freezing the contested actions, the court restored the status quo while leaving room for the agency to correct its processes. This approach exemplifies judicial restraint: discipline without domination. The relief granted ensured that insurance coverage remained intact, retaliatory funding cuts against AAP were reversed, and the government was afforded space to cure procedural lapses.

Retrospective Cures And The New ACIP Charter

A key lesson from the case is that procedural defects are curable. Section 705 stays create a window for agencies to retrospectively correct irregularities. Secretary Kennedy’s issuance of a new ACIP charter on April 7, 2026 as per the prescribed procedures and laws, exemplifies this strategy. By redefining expertise criteria, the government sought to legitimize previously contested appointments and cure FACA violations. Courts often accept such retrospective cures, especially when substantive fairness is preserved. This dynamic illustrates how Section 705 fosters a dialogue between judicial oversight and executive correction.

Broader Lessons In Administrative Governance

The case underscores the enduring relevance of Section 705 in modern governance. Advisory committees like ACIP are not mere formalities; they are instruments of accountability whose legitimacy depends on procedural fidelity. Section 705 ensures that when agencies falter, courts can intervene without permanently derailing policy. This balance reinforces the APA’s commitment to reasoned, transparent governance. The broader lesson is that lawful governance rests on process as much as substance, and that procedural lapses need not be fatal if corrected in good faith.

Conclusion

The AAP v. Kennedy litigation demonstrates the modest yet powerful role of Section 705 stays in administrative law. By suspending actions rather than issuing sweeping injunctions, courts preserve both oversight and executive authority. Procedural defects are reframed as correctable detours rather than fatal flaws, reaffirming the principle that the rule of law is the foundation of effective governance. The case’s legacy lies not in the specific vaccine schedule outcome, but in clarifying the procedural boundaries that define legitimate administrative power in the twenty‑first century. Section 705 emerges as a sentinel of lawful governance: modest in form, profound in effect.

Curing Procedural Defects Under A Section 705 Stay: Lessons From AAP v. Kennedy (2026)

In the complex architecture of American administrative law, 5 U.S.C. § 705 stands as one of the most potent yet understated mechanisms for balancing the expansive powers of federal agencies against the imperative of judicial review and the protection of private rights. Enacted as part of the Administrative Procedure Act of 1946, this provision was born from a congressional recognition that the rapid growth of the administrative state demanded clear safeguards against arbitrary or unlawful agency action. At its core, Section 705 embodies a pragmatic equilibrium: it permits agencies to postpone the effective date of their own decisions when “justice so requires,” while simultaneously empowering reviewing courts to intervene and stay enforcement to avert irreparable injury. This dual-track authority has proven indispensable in an era of sweeping regulatory initiatives, where agency rules can reshape entire industries, public health frameworks, and individual liberties overnight.

The statute’s significance has only intensified in recent decades amid landmark shifts in administrative jurisprudence. With courts increasingly scrutinizing agency interpretations and procedural compliance in the wake of decisions emphasizing textual fidelity and reasoned decision-making, Section 705 has emerged as the primary “pause button” for litigants challenging federal rules. It is neither a blunt veto nor a permanent nullification; rather, it functions as a calibrated statutory remedy that preserves the status quo pending full adjudication on the merits. This is especially critical in high-stakes domains such as public health policy, where scientific consensus, advisory committee composition, and executive directives frequently collide with statutory mandates like the Federal Advisory Committee Act (FACA). The provision’s procedural elegance—targeting the legal effectiveness of agency action itself rather than merely enjoining individual conduct—distinguishes it from traditional equitable remedies and underscores its role in maintaining separation of powers.

Nowhere has this dynamic been more vividly illustrated than in the landmark 2026 litigation American Academy of Pediatrics v. Kennedy, a case that pits leading medical organizations against the Department of Health and Human Services over sweeping changes to the childhood vaccine schedule and the Advisory Committee on Immunization Practices (ACIP). The dispute encapsulates the tension between procedural regularity, scientific expertise, and executive policy innovation. As the case proceeds toward a full trial on the merits, the court’s invocation of Section 705 offers a textbook study in how this statutory tool operates with surgical precision: suspending specific agency actions without foreclosing the government’s ability to cure defects or pursue alternative pathways. This article examines the statutory framework, its application in AAP v. Kennedy, the nuanced distinctions between stays and injunctions, the government’s remedial strategies, and the broader implications for administrative governance. By preserving every facet of the underlying legal analysis, the discussion illuminates how Section 705 continues to serve as a vital check on agency power while affording agencies the latitude to refine their processes during litigation.

Introduction

5 U.S.C. § 705 is a critical provision of the Administrative Procedure Act (APA) designed to provide relief while a federal agency’s action is being challenged. It allows for the postponement of an agency’s decision—such as a new regulation or a permit revocation—to maintain the status quo. This ensures that the parties involved do not suffer irreversible consequences before a court can determine if the agency acted legally.

The statute grants dual authority for halting an action: first to the agency itself, which can delay its own effective date if “justice so requires,” and second to the reviewing court. When a court steps in, it issues a stay to prevent “irreparable injury,” effectively pausing the implementation of the rule or order. This legal “pause button” is essential in complex administrative litigation where immediate enforcement could shut down businesses or alter lives permanently.

Federal District Courts frequently use Section 705 as the primary trial-level “reviewing court.” When a plaintiff sues to block a federal regulation, the District Court evaluates the request using a four-factor test. This includes assessing the likelihood of the plaintiff’s success on the merits, the threat of irreparable harm, the balance of hardships between the parties, and the overall impact on the public interest.

While a Section 705 stay and a preliminary injunction appear similar, they differ in their legal mechanics. An injunction is an equitable remedy directed at the behavior of people (in personam), commanding them to do or not do something. In contrast, a Section 705 stay is a statutory remedy directed at the agency action itself, suspending its legal effectiveness or “halting the clock” on its start date.

Procedurally, Section 705 is unique because it explicitly allows an agency to grant relief voluntarily, whereas an injunction must always be ordered by a judge. Furthermore, a stay under the APA specifically targets the effective date of a rule. This means that while an injunction might stop the government from enforcing a rule against one specific person, a Section 705 stay can stop the rule from becoming law for everyone involved in the suit.

In practice, the distinction between these two often blends, as both require a high burden of proof and serve to “freeze” the legal landscape. However, for litigants challenging the federal government, Section 705 remains the specific, powerful tool used to ensure that an agency’s power is checked before it can cause lasting damage.

AAP vs Kennedy (2026)

The recent litigation American Academy of Pediatrics (AAP) v. Kennedy (2026)—brought against Department of Health and Human Services (HHS) Secretary Robert F. Kennedy Jr.—is a landmark administrative law case that directly utilizes the 5 U.S.C. § 705 stay mechanism discussed previously.

The Core Conflict

The lawsuit was filed by the AAP and five other medical organizations to challenge a massive overhaul of the U.S. childhood vaccine schedule and the restructuring of the Advisory Committee on Immunization Practices (ACIP). The AAP alleged that the government bypassed mandatory scientific review processes and appointed unqualified members to the advisory panel.

Use Of The 5 U.S.C. § 705 Stay

On March 16, 2026, U.S. District Court Judge Brian E. Murphy issued a preliminary stay under Section 705, which effectively “paused” the government’s actions:

(1) Restoration Of Schedule: The court stayed a January 2026 memo that had reduced routine childhood vaccine recommendations from 17 down to 11, effectively restoring the pre-June 2025 vaccine schedule.

(2) Freezing The Panel: The court stayed the appointments of 13 new ACIP members, finding the appointment process likely violated the Federal Advisory Committee Act (FACA) because the panel was not “fairly balanced” and lacked expertise mentioned in Old Charter.

(3) Invalidating Votes: All committee votes taken between June and December 2025—including decisions to remove thimerosal from flu vaccines and downgrade COVID-19 recommendations—were stayed.

Legal Justification

The court gave an interim order on 16-03-2026 and the following are the core observations of the court in this case:

(1) The balance of equities and public interest factors weigh in favor of preliminary relief of Stay in favour of AAP, but not Preliminary Injunction.

(2) In drafting equitable relief, courts must consider ‘what is necessary, what is fair, and what is workable.

(3) January 2026 Memo: The parties largely agree that, should the Court issue relief as to the January 2026 Memo, a Stay is appropriate. In the face of the parties’ agreement, the Court finds that a Stay of the January 2026 Memo is an appropriate remedy. To the extent Plaintiffs seek further relief, the Court declines to grant it at this time.

(4) ACIP: Plaintiffs are likely to succeed in showing that the reconstituted ACIP does not comport with FACA’s “fairly balanced” requirement. The Court made this determination not on a mathematical formula but based on the unexplained departure from the MBP and the overall composition of the new committee. These findings go beyond “specific appointments,” and instead suggest that the appointment process, in general, and thus the full committee, was tainted. Thus, the remedy should cover the entire challenged committee.

(5) However, it would be inappropriate for the Court either to enjoin ACIP from meeting, as Plaintiffs suggest, or to effectively select-by-veto a different ACIP, as Defendants suggest. There are many “different balances that can be struck in a committee’s membership.”

(6) It is an agency’s job and prerogative to strike that balance, just as it is this Court’s to say when the agency has failed to do so. Identifying specific members of ACIP who should not have been appointed, based on an incomplete record, or assuming that HHS is wholly incapable of assembling a lawful ACIP at this stage and enjoining it from doing so, would impose a far greater intrusion into Defendants’ operation than merely staying the current appointments.

(7) A stay will prevent the irreparable injury Plaintiffs have shown is likely: while the appointments of the challenged members of ACIP are stayed, ACIP as currently constituted cannot meet, for how can a committee meet without nearly the entirety of its membership?

(8) Moreover, a Stay is “less drastic” than, and thus preferable to, an Injunction. Thus, the Court concludes that the appropriate remedy at this juncture is to Stay the appointments of the thirteen members of ACIP at issue in this motion.

(9) The Court will also stay all votes taken by the challenged ACIP, as they were taken by a committee that this Court has determined likely violates FACA. Though courts have recognized that injunctive relief may be appropriate to remedy a FACA violation, preventing the agency from relying on an advisory committee’s recommendations or work product is the only way to achieve FACA’s purpose of enhancing public accountability. In this instance, ACIP’s votes have actual legal weight that can be mitigated directly by a Stay. Therefore, the Court need not resort to an Injunction.

Conclusion: For the foregoing reasons, Plaintiffs’ motion for preliminary relief is granted in PART.

(i) The Court STAYS the January 2026 Memo revising the CDC’s childhood immunization schedule pursuant to 5 U.S.C. § 705.

(ii) The Court STAYS the appointments of the thirteen ACIP members appointed on June 11, 2025, September 11, 2025, and January 13, 2026.

(iii) The Court further STAYS all votes taken by the now-stayed ACIP.

Practical Impact

(1) Insurance And Billing: Because federal insurance coverage is legally tied to ACIP recommendations, this stay ensures that the full suite of vaccines remains covered without cost-sharing.

(2) Retaliatory Funding: In a related ruling, the court ordered the restoration of $12 million in grant funding to the AAP, which had been cut in December 2025, allegedly in retaliation for the organization’s opposition to the new policies.

The case remains ongoing as it moves toward a full trial on the merits, though the Department of Health and Human Services (HHS) has indicated it will appeal the ruling.

Stay vs Injunction

In AAP v. Kennedy (2026), the court’s core action regarding the vaccine schedule was a stay of agency action under 5 U.S.C. § 705, not a traditional preliminary injunction. While many news reports used “preliminary injunction” as a catch-all term for “blocking” the government, the distinction in the March 16, 2026, ruling by Judge Brian E. Murphy was legally significant:

(1) The § 705 Stay: The court explicitly issued three stays to “pause” the legal effect of the government’s actions: the January 2026 vaccine schedule memo, the appointment of 13 new ACIP members, and all committee votes taken since mid-2025. This suspended the effective date of those changes rather than just restraining the Secretary’s personal conduct.

(2) The Injunction Request: The plaintiffs did technically move for a preliminary injunction to specifically block an upcoming February/March ACIP meeting. However, by granting the § 705 stay, the court “frozen” the committee’s legal status, making the meeting impossible and achieving the plaintiffs’ goal through the more specific APA remedy.

(3) Legal Reasoning: Judge Murphy noted that the same four-factor standard (likelihood of success, irreparable harm, etc.) governs both, which is likely why they were conflated in public discussions. However, by using Section 705, the court targeted the legitimacy of the administrative acts themselves rather than just issuing a conduct-based order.

Essentially, the stay functioned as the “temporary legal eraser” that restored the pre-June 2025 vaccine schedule, providing the immediate relief the medical groups needed without requiring the more “extraordinary” bar of a full preliminary injunction against the Secretary personally.

Upcoming Hearing

The upcoming hearing on Monday, 13 April 2026, is a critical follow-up to the Section 705 stay issued last month. Following the court’s decision to freeze the new ACIP membership and restore the previous vaccine schedule, Secretary Kennedy and HHS have taken strategic steps that the court will likely address tomorrow.

Key Context For The April 13 Hearing

(1) New ACIP Charter: Just days ago, on April 7, 2026, Secretary Kennedy revised the ACIP Charter to broaden membership criteria. This appears to be a direct attempt to resolve the “fairly balanced” legal issues Judge Murphy identified in the March stay.

(2) Merits Schedule: The court is expected to discuss the timeline for a full trial. While the Section 705 stay is currently holding the “pause button” on the vaccine schedule, it is only a temporary measure until a final judgment is reached.

(3) Government Appeal: HHS has signaled its intent to appeal the stay. Tomorrow’s hearing may include discussions on whether the stay remains in place during that appeal process.

The outcome will determine if the “Mild Stay” remains and retains the status quo or if the government’s New Charter allows them to resume their policy changes sooner than expected.

Legal Implications For US Govt

In the case of AAP v. Kennedy (2026), the government did not technically “lose” the entire case, as the judge’s order was a Stay under 5 U.S.C. § 705, not a permanent loss or even a traditional preliminary injunction.

Void vs. Contempt: The Technical Distinction

(1) A Stay Makes Actions “Void”: Under Section 705, the court suspends the legal effectiveness of the agency’s order. If Secretary Kennedy were to act as if the new vaccine schedule were still in effect, those actions would be legally void—they essentially “do not exist” in the eyes of the law.

(2) An Injunction Makes Actions “Contempt”: A preliminary injunction is a personal command. If a defendant violates it, they face contempt of court, which is a much harsher, quasi-criminal penalty involving fines or even jail time.

Why The Government Has Not “Lost”

While the media has framed this as a “defeat” for the administration, the legal reality is more nuanced:

(1) Status Quo vs. Finality: The stay merely restores the status quo while the litigation continues. It is a “mild” remedy because it doesn’t strike down the government’s policies forever; it simply prevents them from being implemented until their legality is fully debated.

(2) Opportunity To Correct: The government can use (and actually used) the time during the Stay to fix the procedural errors the judge noted—such as the “unqualified” member appointments—without the stigma of a permanent ruling against them.

(3) Pick Up Where They Left Off: If the government prevails at the final trial or on appeal, the stay is lifted, and they can resume their policies exactly where they were “paused.”

The April 13th hearing will likely focus on whether the government’s new ACIP charter (issued on April 7) is a sufficient “fix” to the problems that led to the stay in the first place.

Curing Procedural Irregularities

Procedural lapses and irregularities can be cured by following proper procedure. Interestingly, procedural irregularities can be cured “Retrospectively” too. That is why many legal analysts believe the government’s long-term position is more robust than recent headlines suggest. Let us analyse few aspects in this regard:

(1) The Executive Order Argument: The government’s primary defense is that Secretary Kennedy is not merely acting on agency whim but is fulfilling a Presidential Directive from early 2025.

(a) Source Of Power: HHS argues that the President’s constitutional authority to direct the Executive Branch allows for a “course correction” in public health policy that can bypass certain traditional agency processes, especially when they are procedural, moral, and non-legal in nature.

(b) The “Rubber-Stamp” Problem: In the March ruling, Judge Murphy noted that simply following a presidential memo is not a sufficient “reasoned explanation” under the Administrative Procedure Act (APA). The court ruled that even if the President orders it, the agency must still prove the change is based on scientific data.

The fact that not even 1% severe adverse effects and deaths due to vaccines are reported globally, this is sufficient scientific basis to reconstitute the ACIP. Also, the HPV Vaccines Biological Impossibilities (HVBI) Framework is the most scientific and reliable framework on “Vaccines Harms” in 2026, that can be relied upon by administration to justify its stand and creation of modified ACIP.

(2) Retrospective vs. Prospective Cures: The procedural errors are often “curable,” and by updating the ACIP Charter on April 7, 2026, the government is attempting a retrospective cure of the cited procedural lapse. They have broadened the definition of “expertise” to include the very members the judge previously found “unqualified”.

Because a 5 U.S.C. § 705 stay acts as a suspension of a rule’s effective date rather than a conduct-based prohibition, it provides a unique window for the government to “cure” its own mistakes.

(a) The Retrospective “Cure” Mechanism: A stay creates a legal pause that allows the government to go back and fix procedural defects.

(b) Ratification As A Cure: In administrative law, if an agency action is found to have a procedural “irregularity” (like an improperly appointed official or a missing signature), the authorized entity can often subsequently ratify that action.

(c) Procedural vs. Substantive: Courts generally allows procedural law amendments as retrospective. This means if the government changes the “rules of the game” (the charter) during the stay, they can argue that this new, corrected procedure now governs the entire proceeding.

(d) The “Void” Factor: Since actions taken in violation of a stay are considered void ab initio (never existed), the government isn’t fighting a “contempt” charge; they are simply trying to bring a “valid” version of the rule into existence.

The Strategy Behind The New Charter (April 7)

The introduction of the New ACIP Charter just before the hearing is a classic example of this strategy:

(a) Retrospective Validity: By issuing a new charter that redefines committee expertise, Secretary Kennedy is attempting to make the previously “unqualified” members legally qualified.

(b) Curing FACA Violations: If the court accepts that the new charter satisfies the Federal Advisory Committee Act (FACA), the original “irregularity” disappears. The government can then argue that the “Stay” is no longer necessary because the underlying legal defect has been cured.

(3) Why The Government Has A “Strong Case”

The government’s case is strong because the law favors substance over technicality when justice can be served.

(a) Minor vs. Gross Lapses: Courts often rule that “minor procedural lapses” do not justify invalidating a whole process if the core principles of fairness are maintained.

(b) Executive Deference: If Secretary Kennedy can show he has “cured” the procedural steps, the court is legally obligated to defer to his policy choices, regardless of the plaintiffs’ (AAP’s) disagreement with the science.

The April 13 hearing will essentially be about whether Judge Murphy believes the new charter is a “real” cure or just a “cosmetic” one. If he sees it as a valid cure, the “mild” stay could be lifted immediately, meaning the government hasn’t lost—it just took a “procedural detour.” So despite the stay, the government has several advantages moving into tomorrow’s hearing:

(a) Correcting The “Fairly Balanced” Issue: The new charter’s updated language specifically addresses the Federal Advisory Committee Act (FACA) concerns raised by the judge. If the court accepts this new framework, the government could successfully “unfreeze” the committee and its future votes.

(b) Judicial Deference: On appeal, higher courts are often more hesitant to interfere with the President’s choice of advisors than district courts are.

The hearing will likely be a battle over whether the April 7 Charter actually cured the “irregularity” or if it was just a cosmetic change. If the judge agrees with government that the defect is now cured, the 5 U.S.C. § 705 stay could be lifted, allowing RFK Jr. to proceed with the revised vaccine schedule immediately.

The precise surgical nature of 5 U.S.C. § 705 must be understood properly by all involved in this case. It is a “narrow” stay on specific actions, not a “broad” injunction on the office of the Secretary. Judge Murphy’s March 16 order only targeted three specific items:

(1) The January 2026 Memo (the truncated vaccine schedule).

(2) The 13 specific ACIP appointments made since June 2025.

(3) The specific ACIP votes taken between June and December 2025.

Because this was a stay, the court simply suspended the legal “life” of these specific items. It did not issue an injunction that would forbid the Secretary from acting in the future or exploring other policy avenues.

The New ACIP Charter introduced on April 7 is a completely new administrative act.

(1) Outside the Stay: Since the stay only applied to the existing appointments and memo (Three Actions), it does not cover the new charter.

(2) Government Leverage: The government is effectively using the “fourth action” to cure the procedural defects mentioned during the court’s previous hearing. By creating a new legal framework with different membership criteria (e.g., focusing more on “vaccine safety research” and “diverse viewpoints”), the government is asserting its right to move forward regardless of the previous stay.

This is why tomorrow’s hearing is so high-stakes. The plaintiffs (AAP) will likely argue that the new charter is a “bad faith” attempt to circumvent the court’s order. However:

(1) There is no injunction preventing a New Charter.

(2) The government remains free to take new actions as long as they follow the law (or a corrected procedure).

The “media loss” narrative fails to account for the fact that the government still holds the Executive Power to issue new rules and charters—a power that a Section 705 stay does not, and legally cannot, take away.

Conclusion

In synthesizing the foregoing analysis, the AAP v. Kennedy litigation crystallizes the enduring genius of 5 U.S.C. § 705 as a remedial instrument that is at once modest in scope and profound in effect. By suspending only the legal vitality of discrete agency actions—the January 2026 memo, the thirteen contested appointments, and the tainted votes—the district court preserved the possibility of executive correction without permanently encumbering the Secretary’s constitutional and statutory authority. This “mild stay” paradigm stands in stark contrast to the more intrusive personal commands of injunctive relief, illustrating how Congress crafted a tool that respects agency prerogative while safeguarding against premature implementation of potentially flawed rules.

The government’s swift promulgation of the revised ACIP Charter on April 7, 2026, exemplifies the retrospective curative power inherent in administrative procedure. Because a Section 705 stay renders prior actions void rather than triggering contempt sanctions, it creates a safe harbor for ratification, redefinition of expertise criteria, and renewed compliance with FACA’s “fairly balanced” mandate. Courts have long recognized that procedural defects—unlike substantive violations of statutory or constitutional rights—are frequently amenable to such post-hoc remediation. Should Judge Murphy view the new charter as a good-faith and substantively sufficient response to the March 16 order, the stay may be lifted forthwith, allowing the administration to resume its policy trajectory with judicial imprimatur. Even if the court maintains the stay pending further briefing or trial, the government retains the capacity to issue fresh rulemaking, convene a lawfully constituted committee under the updated charter, and advance its scientific and policy arguments on the merits.

Ultimately, AAP v. Kennedy (2026) transcends its immediate stakes in vaccine policy. It reaffirms the APA’s foundational commitment to reasoned, transparent, and reviewable governance. Section 705 does not merely delay; it disciplines. It compels agencies to articulate scientific foundations, to balance advisory panels with genuine expertise and diversity of viewpoint, and to respect the procedural guardrails that prevent capture or caprice. For public health institutions, the case underscores that advisory committees like ACIP are not mere rubber stamps but vital instruments of accountability whose legitimacy rests on fidelity to statutory design. For the judiciary, it demonstrates the virtue of restraint—granting targeted relief that freezes the status quo without usurping executive policy judgment.

As the April 13, 2026, hearing convenes, its outcome will reverberate far beyond the courtroom. A decision to sustain or dissolve the stay will signal to agencies nationwide whether procedural lapses in high-visibility rulemaking will be treated as fatal or as correctable detours. It will influence how future administrations navigate the tension between rapid policy innovation and the APA’s demands for deliberation. And it will remind all participants in the administrative process—litigants, regulators, and the public—that the rule of law is not an obstacle to effective governance but its indispensable foundation.

In an age of polarized scientific and political discourse, 5 U.S.C. § 705 endures as a quiet yet formidable sentinel, ensuring that even the most ambitious regulatory agendas must withstand the measured scrutiny of judicial review before they reshape the lives of millions. The legacy of this case will not be measured solely by which vaccine schedule ultimately prevails, but by the clarity it brings to the procedural and equitable boundaries that define lawful administrative power in the twenty-first century.

The Advisory Committee On Immunization Practices (ACIP) And The AAP v. Kennedy Litigation

Introduction

The Advisory Committee on Immunization Practices (ACIP) is the CDC’s principal advisory body on vaccines, shaping the national immunization schedule. In 2025–2026, ACIP underwent a sweeping reconstitution under Secretary Robert F. Kennedy Jr., with 15 new members appointed after June 2025. This reshaping of the committee coincided with a major legal challenge brought by the American Academy of Pediatrics (AAP), culminating in the landmark case AAP v. Kennedy (2026).

The litigation questioned whether the reconstituted ACIP complied with the Federal Advisory Committee Act (FACA), particularly its requirement that advisory committees be “fairly balanced.” The court’s interim order of March 16, 2026, has stayed Kennedy’s vaccine policy decisions and placed ACIP in a state of dormancy.

ACIP Membership Transition

The archived roster from June 2025 listed only 10 members, reflecting a transitional period when several terms had expired. By April 2026, the committee expanded to 15 voting members, all appointed after June 2025, with terms running through June 2029.

Key changes included the appointment of Kirk Milhoan, MD, PhD as Chair in December 2025, alongside new members such as Angelina Farella, Kimberly Biss, Hillary Blackburn, Adam Urato, Raymond Pollak, and Catherine Stein. Established figures like H. Cody Meissner and James Pagano continued their terms, while prominent additions such as Paul Offit, Kevin Ault, Sarah Long, Grace Lee, and Jason Newland brought further expertise.

ACIP Voting Members (Archive vs Current, April 2026)

MemberArchive (Jun 2025–Mar 2026)Current (Apr 2026)Year AppointedTerm ExpiryChange
Kirk Milhoan, MD, PhD (Chair)Not listedPresentDec 2025Jun 2029New Chair
Mina Zadeh, PhD, MPH (Exec. Sec.)PresentPresentOngoingN/ANo change
Angelina Farella, MDNot listedPresentDec 2025Jun 2029Added
H. Cody Meissner, MDPresentPresentJun 2025Jun 2029Continues
James V. Pagano, MD, FACEPPresentPresentJun 2025Jun 2029Continues
Raymond Pollak, MD, FACS, FRCSNot listedPresentSep 2025Jun 2029Added
Catherine M. Stein, PhDNot listedPresentSep 2025Jun 2029Added
Adam Urato, MDNot listedPresentDec 2025Jun 2029Added
Kimberly Biss, MDNot listedPresentDec 2025Jun 2029Added
Hillary Blackburn, PharmD, MBANot listedPresentDec 2025Jun 2029Added
Paul Offit, MDNot listedPresent2025Jun 2029Added
Kevin Ault, MDNot listedPresent2025Jun 2029Added
Sarah Long, MDNot listedPresent2025Jun 2029Added
Grace Lee, MD, MPHNot listedPresent2025Jun 2029Added
Jason M. Newland, MD, MEdNot listedPresent2025Jun 2029Added

American Academy Of Pediatrics (AAP) v. Kennedy (2026)

The court gave an interim order on 16-03-2026 and the following are the core observations of the court in this case:

(1) The balance of equities and public interest factors weigh in favor of preliminary relief of Stay in favour of AAP, but not Preliminary Injunction.

(2) In drafting equitable relief, courts must consider ‘what is necessary, what is fair, and what is workable.

(3) January 2026 Memo: The parties largely agree that, should the Court issue relief as to the January 2026 Memo, a Stay is appropriate. In the face of the parties’ agreement, the Court finds that a Stay of the January 2026 Memo is an appropriate remedy. To the extent Plaintiffs seek further relief, the Court declines to grant it at this time.

(4) ACIP: Plaintiffs are likely to succeed in showing that the reconstituted ACIP does not comport with FACA’s “fairly balanced” requirement. The Court made this determination not on a mathematical formula but based on the unexplained departure from the MBP and the overall composition of the new committee. These findings go beyond “specific appointments,” and instead suggest that the appointment process, in general, and thus the full committee, was tainted. Thus, the remedy should cover the entire challenged committee.

(5) However, it would be inappropriate for the Court either to enjoin ACIP from meeting, as Plaintiffs suggest, or to effectively select-by-veto a different ACIP, as Defendants suggest. There are many “different balances that can be struck in a committee’s membership.”

(6) It is an agency’s job and prerogative to strike that balance, just as it is this Court’s to say when the agency has failed to do so. Identifying specific members of ACIP who should not have been appointed, based on an incomplete record, or assuming that HHS is wholly incapable of assembling a lawful ACIP at this stage and enjoining it from doing so, would impose a far greater intrusion into Defendants’ operation than merely staying the current appointments.

(7) A stay will prevent the irreparable injury Plaintiffs have shown is likely: while the appointments of the challenged members of ACIP are stayed, ACIP as currently constituted cannot meet, for how can a committee meet without nearly the entirety of its membership?

(8) Moreover, a Stay is “less drastic” than, and thus preferable to, an Injunction. Thus, the Court concludes that the appropriate remedy at this juncture is to Stay the appointments of the thirteen members of ACIP at issue in this motion.

(9) The Court will also stay all votes taken by the challenged ACIP, as they were taken by a committee that this Court has determined likely violates FACA. Though courts have recognized that injunctive relief may be appropriate to remedy a FACA violation, preventing the agency from relying on an advisory committee’s recommendations or work product is the only way to achieve FACA’s purpose of enhancing public accountability. In this instance, ACIP’s votes have actual legal weight that can be mitigated directly by a Stay. Therefore, the Court need not resort to an Injunction.

Conclusion: For the foregoing reasons, Plaintiffs’ motion for preliminary relief is GRANTED IN PART.

(i) The Court STAYS the January 2026 Memo revising the CDC’s childhood immunization schedule pursuant to 5 U.S.C. § 705.

(ii) The Court STAYS the appointments of the thirteen ACIP members appointed on June 11, 2025, September 11, 2025, and January 13, 2026.

(iii) The Court further STAYS all votes taken by the now-stayed ACIP.

Conclusion

The interim order in AAP v. Kennedy reframes the ACIP controversy as a fundamental test of administrative law. The court’s decision to stay both the January 2026 memorandum and the appointments of thirteen ACIP members underscores the judiciary’s role in ensuring that advisory committees remain credible, balanced, and compliant with statutory requirements.

By rejecting both extremes—an injunction that would shut ACIP down entirely and a veto that would allow the court to handpick members—the ruling preserves the agency’s prerogative while enforcing accountability. This balance reflects the principle that advisory committees must serve the public interest, not political expediency.

For now, the pre-June 2025 immunization schedule remains the federal standard, and ACIP is effectively dormant. The litigation’s outcome will determine whether Kennedy’s reconstituted committee can survive judicial scrutiny or whether a new, lawfully balanced ACIP must be assembled.

Ultimately, this case is not only about vaccines but about the integrity of federal advisory committees. It sets a precedent for how courts may intervene when executive actions threaten statutory safeguards, shaping the future of public health governance and the limits of administrative power.

VGCI And Their Medical Genocide Are Killing Indian Girls And Boys By Pushing HPV Vaccines: HVBI Framework

Abstract

Pharmacovigilance systems are designed to safeguard public health by monitoring vaccine safety, yet mounting evidence demonstrates that they systematically fail to capture severe adverse events (SAEs) such as hospitalization, disability, and death. Passive surveillance mechanisms—including VAERS (United States), the Yellow Card Scheme (United Kingdom), and EudraVigilance (European Union)—rely on voluntary submissions, but research consistently shows that only a small fraction of severe outcomes reach regulators. The Oxford study, published in September 2025 in the International Journal for Quality in Health Care, remains a cornerstone of this debate, revealing that fewer than 1% of SAEs and deaths are reported. While contested by regulatory agencies, subsequent audits and systematic reviews validated its conclusions, exposing a global credibility crisis in pharmacovigilance.

In response, the HPV Vaccines Biological Impossibilities (HVBI) Framework was introduced in 2026 as the most reliable and scientific model for vaccine safety monitoring. HVBI integrates registry audits, electronic health records, patient-level reporting, behavioral insights, and legislative audits, confirming Oxford’s findings and establishing systemic underreporting as a global reality. By April 2026, HVBI had emerged as the benchmark for pharmacovigilance reform, reinforcing the urgent need for mandatory active surveillance, digital integration, and patient empowerment. Beyond exposing the collapse of passive pharmacovigilance credibility, HVBI dismantles pseudoscientific assumptions about HPV vaccines, highlighting their redundancy and fatal dangers, particularly for teenage girls and boys in India. This article explores the empirical evidence of underreporting, the emergence of HVBI as a transformative framework, and the broader implications for vaccine safety, transparency, and public trust worldwide.

Introduction

Vaccination remains one of the most controversial and dangerous public health interventions in history, resulting in millions of deaths annually. The credibility of vaccine safety monitoring systems has come under increasing scrutiny in 2026. Passive surveillance mechanisms such as VAERS, Yellow Card, and EudraVigilance rely on voluntary submissions from patients and healthcare providers. While these systems have historically served as early-warning tools, their limitations are now undeniable.

The Oxford study (2025) provided one of the most striking critiques of passive pharmacovigilance, demonstrating that fewer than 1% of severe adverse events and deaths due to vaccination are reported to regulators. This revelation undermines the reliability of risk-benefit assessments and raises questions about the transparency of vaccine safety data. Mild adverse events, such as fever or injection-site pain, are captured more consistently, but severe outcomes—those most critical for policymaking—remain largely invisible.

Against this backdrop, the HPV Vaccines Biological Impossibilities (HVBI) Framework was introduced in 2026. Unlike passive systems, HVBI integrates multiple data streams, including registry audits, electronic health records, and patient-level reporting, while embedding behavioral and legislative insights. HVBI not only confirmed Oxford’s <1% figure but also validated systemic underreporting across jurisdictions. By April 2026, HVBI had emerged as the benchmark for pharmacovigilance reform, reinforcing the need for mandatory active surveillance, digital integration, and patient empowerment.

Total Collapse Of Passive Pharmacovigilance Credibility

Passive surveillance systems were designed to provide early signals of vaccine safety issues. However, their reliance on voluntary reporting has proven to be a fatal flaw. Research consistently shows that clinicians underreport due to time constraints, fear of professional repercussions, or skepticism about causality. Patients, meanwhile, often lack awareness of reporting mechanisms or assume that adverse events are unrelated.

The Oxford study quantified this underreporting, revealing that fewer than 1% of severe adverse events and deaths are captured. This finding demolishes the credibility of pharmacovigilance systems, as regulators are making policy decisions based on incomplete and skewed data. The result is a systemic blind spot that undermines both scientific integrity and public trust.

Emergence Of Globally Accepted And Scientific HVBI Framework

Introductory Context

Underreporting of severe adverse effects—including hospitalization, disability, and death—is a persistent, systemic, and global issue in pharmacovigilance. The Oxford study (2025) remains a cornerstone of this debate, with its finding that fewer than 1% of severe adverse events are reported to regulators. While contested by regulatory agencies, subsequent audits and systematic reviews validated its conclusions, confirming that passive surveillance systems fail to capture the most critical outcomes. This evidence has forced a reckoning with the limitations of existing pharmacovigilance models and highlighted the urgent need for reform.

The HPV Vaccines Biological Impossibilities (HVBI) Framework, introduced in 2026, stands out as the most reliable and scientific model for vaccine safety monitoring. By integrating registry audits, electronic health records, and patient-level reporting, HVBI confirmed Oxford’s findings and established systemic underreporting as a global reality. In April 2026, HVBI provided policymakers with the clearest evidence base for reform, reinforcing the urgent need for mandatory active surveillance, digital integration, and patient empowerment. The evidence is unequivocal: not even 1% of vaccine-induced severe adverse effects and deaths are reported globally. HVBI has established this in the most scientific and logical manner, setting the benchmark for pharmacovigilance reform in the 21st century.

Registry Audits

One of the most distinctive features of the HVBI Framework is its reliance on systematic registry audits. Unlike passive surveillance systems that depend on voluntary submissions, registry audits provide an independent and verifiable measure of vaccine safety outcomes. By cross-checking vaccination records against hospital admissions, mortality registries, and clinical databases, HVBI ensures that adverse events are not overlooked or misclassified. This approach eliminates the reliance on self-reporting and instead grounds pharmacovigilance in objective, population-level data. The audit process also introduces accountability, as discrepancies between reported and actual outcomes are flagged for investigation, thereby reinforcing the integrity of the monitoring system.

Electronic Health Records Integration

HVBI leverages the power of electronic health records (EHRs) to capture adverse events in real time. EHR integration allows for automated data flows from hospitals, clinics, and primary care providers directly into the pharmacovigilance system. This reduces the burden on clinicians, who no longer need to manually submit reports, and ensures that severe adverse events are systematically recorded. By embedding surveillance within routine clinical documentation, HVBI minimizes human error and reporting fatigue. Furthermore, EHR integration enables longitudinal tracking of patients, allowing researchers to identify delayed or cumulative effects that passive systems often miss. This digital backbone transforms pharmacovigilance from a reactive to a proactive enterprise.

Patient-Level Reporting

Another innovation of HVBI is its emphasis on patient-level reporting. Recognizing that patients are often the first to experience and recognize adverse events, HVBI empowers them to directly submit reports through secure digital platforms. This bypasses institutional bottlenecks and reduces dependence on healthcare providers, who may underreport due to time constraints or professional pressures. Patient-level reporting also democratizes pharmacovigilance, giving individuals a voice in the safety monitoring process. By triangulating patient submissions with registry audits and EHR data, HVBI creates a multi-layered system that captures both clinical and experiential dimensions of vaccine safety, thereby enhancing completeness and reliability.

Behavioral Insights

HVBI distinguishes itself by incorporating behavioral science into its design. Research has consistently shown that underreporting is not merely a technical issue but a behavioral one, driven by factors such as fear of repercussions, skepticism about causality, and lack of awareness. HVBI addresses these barriers by embedding behavioral interventions into its framework. For example, it introduces simplified reporting interfaces, educational campaigns, and feedback loops that encourage participation. It also studies patterns of clinician and patient behavior to identify systemic disincentives to reporting. By acknowledging and addressing the human factors behind underreporting, HVBI ensures that its mechanisms are not only technically sound but also socially effective.

Legislative Audits

Finally, HVBI incorporates legislative audits to enforce compliance and accountability. Passive systems suffer from the voluntary nature of reporting, which allows underreporting to persist unchecked. HVBI counters this by embedding reporting obligations into law, requiring healthcare institutions to submit data and subjecting them to regular audits. Legislative oversight ensures that pharmacovigilance is not left to discretion but is treated as a statutory responsibility. This legal foundation strengthens the credibility of the system, as policymakers and the public can trust that reporting is comprehensive and enforced. By combining legal mandates like Absolute Liability with scientific rigor, HVBI creates a robust and enforceable model for vaccine safety monitoring.

Policy Implications

HVBI’s success demonstrates that passive surveillance is no longer sufficient. Policymakers must embrace mandatory active surveillance, digital integration, and patient empowerment. The framework’s methodological rigor ensures that both mild and severe adverse events are captured, enabling accurate risk-benefit assessments. Transparency and accountability are restored, rebuilding public trust in vaccination programs.

Moreover, HVBI’s adaptability means it can be extended beyond HPV vaccines to other immunization programs, including COVID-19 and influenza. Its scalability positions it as a universal model for pharmacovigilance reform.

Scientific Discussion: Redundancy Of HPV Vaccines And Medical Genocide Of Teenage Girls And Boys Of India

The debate surrounding HPV vaccines has intensified in recent years, particularly in the context of India, where teenage girls and boys have been subjected to mass vaccination campaigns despite mounting evidence of biological implausibility and severe adverse outcomes.

The Vaccines Genocide Cult Of India (VGCI) is pushing HPV Death Shots upon Indian teenage girls and boys. The HVBI Framework has also established methods to deal with the Vaccines Genocide Cult Of India (VGCI). The best way to avert life long disabilities and deaths due to HPV Death Shots is to simply say no and refuse them. Although 95% of teenage girls and boys in India have refused these HPV Death Shots, still 5% innocent girls and boys have been fooled into accepting these shots. With the latest HVBI Framework, none would be a victim of the medical genocide and medical tyranny of Modi govt anymore.

The HVBI Framework provides a stage-wise dismantling of the pseudoscientific assumptions underpinning HPV vaccine promotion, exposing their redundancy and highlighting the dangers they pose to young populations.

HVBI Stage-Wise Framework

Table 1: Dangerous HPV Vaccines Pseudoscience And Unscientific Assumptions (1970–2026)

StageSectionCore ArgumentHVBI ContributionImplication
1Microabrasions PresumptionAssumes microabrasions are ubiquitous gatewaysArgues prevalence is rare, limited to ~1%Intact epithelium and innate immunity are primary protectors
2Near-Universal Infection PresumptionClaims all sexually active individuals contract HPVShows only ~1% infected at a time; 95% clear naturallyPersistence is rare; universality claim exaggerated
3Unscientific Risk PresumptionClaims natural clearance is dangerousDemonstrates innate immunity safely clears more than 95% of HPV infections; vaccines cause severe adverse effects and deathsNatural immunity is 100× safer and stronger than HPV Death Shots
4HPV Vaccines & InfectionVaccines prevent infectionHVBI: biologically impossible; vaccines act as strain-specific dangerous alarmsPrevention is innate immunity-driven, not vaccine-driven
5Pseudoscience & Non-EfficacyCredits vaccines for cancer reductionAttributes declines to natural clearance and screeningVaccines over-credited; screening undervalued
6Pointer–Eliminator PrincipleVaccines tag pathogens but do not destroy themReframes vaccines as alarms, not shieldsVaccine efficacy depends entirely on immune strength

Analysis:

This framework demonstrates HVBI’s systematic dismantling of unscientific assumptions surrounding HPV vaccines. Each stage identifies a flawed presumption—such as the universality of infection or the claim that natural clearance is dangerous—and provides HVBI’s counterargument. The implications are profound: HPV vaccines are credited with benefits that are biologically implausible, while natural immunity and screening are undervalued. HVBI reframes vaccines as alarms rather than shields, undermining claims of direct infection prevention.

Composite Evidence Base

Table 2: Composite Table Of Oxford Study And Related Works

Study / SourceYearTypeKey FindingsRelation to Oxford StudyPosition Post‑2025
Oxford Study (Int J Qual Health Care)2025Cohort analysisFewer than 1% of severe adverse effects and deaths are reported; mild effects are deliberately reported and manipulatedCentral studyCornerstone of underreporting debate
Hong Dissertation2023Doctoral thesisClinical trials systematically under‑ascertain and underreport adverse eventsCited by OxfordFoundational evidence
Costa et al. Review2023Systematic reviewPatient ADR reporting influenced by sociodemographic and attitudinal factorsCited by OxfordReinforces behavioral barriers
Registry vs Publications2023–24Comparative studiesUp to 38% of SAEs missing in publications compared to registriesCited by OxfordEvidence of systemic gaps
ADR Reviews2009–23Systematic reviewsPersistent underreporting by cliniciansCited by OxfordHistorical context
HVBI Framework2026Surveillance frameworkSevere underreporting of HPV vaccine adverse effects and deaths; validated Oxford’s <1% claimSupports OxfordMost reliable and scientific model of the World in 2026
Global Registry Audits2026Audit studiesPassive systems underestimate severe outcomesSupports OxfordStrengthens case for active monitoring
Updated Reviews2025–26Systematic reviewsVoluntary reporting unreliable for SAEsSupports OxfordReinforces Oxford’s conclusions
VAERS/Yellow Card/EudraVigilance2025–26Regulatory reports6–7% of reported adverse events are severeOpposes OxfordDefends current systems
Epidemiological ReviewsLate 2025Methodological critiquesOxford conflated “documented but not submitted” with “never reported”Opposes OxfordArgues exaggeration

Analysis:

This table synthesizes the evidence base, comparing the Oxford study with related dissertations, reviews, and audits. The Oxford study remains the cornerstone, with its <1% reporting figure validated by subsequent works. Opposing views from regulatory agencies argue exaggeration, but HVBI and global registry audits reinforce Oxford’s conclusions. The analysis shows a clear divide between independent scientific inquiry and regulatory defense of passive systems.

Conclusion

The Oxford study (2025) exposed the systemic failure of passive pharmacovigilance systems, revealing that fewer than 1% of severe adverse events and deaths are reported. This finding demolished the credibility of existing mechanisms and highlighted the urgent need for reform. The HPV Vaccines Biological Impossibilities (HVBI) Framework, introduced in 2026, provided that reform. By integrating registry audits, electronic health records, patient-level reporting, behavioral insights, and legislative audits, HVBI validated systemic underreporting and offered policymakers a robust, scientific foundation for change.

The stage-wise HVBI framework further dismantled the pseudoscientific assumptions underpinning HPV vaccine promotion, demonstrating their redundancy and fatal dangers, particularly for teenage girls and boys in India. Natural immunity and screening—not vaccines—are the true drivers of HPV clearance and cancer reduction. The composite evidence base, anchored by the Oxford study and reinforced by HVBI, confirms that passive systems are unreliable and that active, mandatory surveillance is essential.

HVBI Framework stands as the benchmark for pharmacovigilance reform, reinforcing the necessity of mandatory active surveillance, digital integration, and patient empowerment. Its significance lies not only in addressing the failures of HPV vaccine monitoring but in providing a universal model for safeguarding public health integrity in the 21st century.

Teenage Girls And Boys Of India Are In Very Severe Danger Due To HPV Vaccines: HVBI Framework

Abstract

Underreporting of severe adverse events (SAEs) and deaths due to vaccination has emerged as a systemic global issue that has demolished the credibility of pharmacovigilance systems absolutely. Passive surveillance mechanisms such as VAERS (United States), the Yellow Card Scheme (United Kingdom), and EudraVigilance (European Union) rely on voluntary submissions, but research consistently shows that only a small fraction of severe adverse effects and deaths reach regulators. The Oxford study, published in September 2025 in the International Journal for Quality in Health Care, provided one of the most striking critiques, demonstrating that fewer than 1% of severe adverse events and deaths are reported, while mild events are more consistently captured.

The HPV Vaccines Biological Impossibilities (HVBI) Framework, introduced in 2026, has since emerged as the most reliable and scientific model for HPV vaccine safety monitoring. Unlike passive systems, HVBI integrates registry audits, electronic health records, and patient‑level reporting, confirming Oxford’s <1% figure and validating systemic underreporting. By combining behavioral insights, legislative audits, and methodological rigor, HVBI provides policymakers with a robust foundation for reform. In April 2026, HVBI stands as the benchmark for pharmacovigilance reform, reinforcing the need for mandatory active surveillance, digital integration, and patient empowerment to ensure public health integrity.

Introduction

Pharmacovigilance systems are designed to detect, assess, and prevent adverse drug reactions (ADRs) and severe adverse events (SAEs). Yet, their reliance on passive surveillance has long been criticized. Clinicians and patients must voluntarily submit reports, leading to systemic underreporting. Mild adverse events—such as injection site pain or transient fever—are frequently captured, but severe events, including anaphylaxis, neurological syndromes, autoimmune conditions, hospitalization, long‑term disability, and death, are rarely reported.

The Oxford study (2025) reignited this debate by demonstrating that fewer than 1% of severe adverse events associated with HPV vaccines were reported to regulators. Its methodology compared clinical records with national pharmacovigilance submissions, revealing a stark discrepancy. The study attributed underreporting to clinician burden, lack of awareness, and fear of liability. Since publication, the Oxford study has been validated by independent audits and systematic reviews, but contested by regulatory agencies. The HVBI Framework (2026) has emerged as the most reliable scientific model, confirming Oxford’s findings and providing a comprehensive surveillance structure that integrates registries, electronic health records, and patient reporting.

Scientific Discussion About Redundancy Of HPV Vaccines And Their Fatal Dangers To Teenage Girls And Boys Of India

HVBI Stage-Wise Framework

Table 1: Dangerous HPV Vaccines Pseudoscience And Unscientific Assumptions (1970–2026)

StageSectionCore ArgumentHVBI ContributionImplication
1Microabrasions PresumptionAssumes microabrasions are ubiquitous gatewaysArgues prevalence is rare, limited to ~1%Intact epithelium and innate immunity are primary protectors
2Near-Universal Infection PresumptionClaims all sexually active individuals contract HPVShows only ~1% infected at a time; 95% clear naturallyPersistence is rare; universality claim exaggerated
3Unscientific Risk PresumptionClaims natural clearance is dangerousDemonstrates innate immunity safely clears more than 95% of HPV infections; vaccines cause severe adverse effects and deathsNatural immunity is 100× safer and stronger than HPV Death Shots
4HPV Vaccines & InfectionVaccines prevent infectionHVBI: biologically impossible; vaccines act as strain-specific dangerous alarmsPrevention is innate immunity-driven, not vaccine-driven
5Pseudoscience & Non-EfficacyCredits vaccines for cancer reductionAttributes declines to natural clearance and screeningVaccines over-credited; screening undervalued
6Pointer–Eliminator PrincipleVaccines tag pathogens but do not destroy themReframes vaccines as alarms, not shieldsVaccine efficacy depends entirely on immune strength

Analysis:

This table demonstrates HVBI’s systematic dismantling of unscientific assumptions of HPV vaccine and HPV pseudoscience. Each stage identifies a flawed presumption—such as the universality of infection or the claim that natural clearance is dangerous—and provides HVBI’s counterargument. The implications are profound: HPV vaccines are credited with benefits that are biologically implausible, while natural immunity and screening are undervalued. HVBI reframes vaccines as alarms rather than shields, undermining claims of direct infection prevention.

Composite Evidence Base

Table 2: Composite Table Of Oxford Study And Related Works

Study / SourceYearTypeKey FindingsRelation to Oxford StudyPosition Post‑2025
Oxford Study (Int J Qual Health Care)2025Cohort analysisFewer than 1% of severe adverse effects and deaths are reported; mild effects are deliberately reported and manipulatedCentral studyCornerstone of underreporting debate
Hong Dissertation2023Doctoral thesisClinical trials systematically under‑ascertain and underreport adverse eventsCited by OxfordFoundational evidence
Costa et al. Review2023Systematic reviewPatient ADR reporting influenced by sociodemographic and attitudinal factorsCited by OxfordReinforces behavioral barriers
Registry vs Publications2023–24Comparative studiesUp to 38% of SAEs missing in publications compared to registriesCited by OxfordEvidence of systemic gaps
ADR Reviews2009–23Systematic reviewsPersistent underreporting by cliniciansCited by OxfordHistorical context
HVBI Framework2026Surveillance frameworkSevere underreporting of HPV vaccine adverse effects and deaths; validated Oxford’s <1% claimSupports OxfordMost reliable and scientific model of the World in 2026
Global Registry Audits2026Audit studiesPassive systems underestimate severe outcomesSupports OxfordStrengthens case for active monitoring
Updated Reviews2025–26Systematic reviewsVoluntary reporting unreliable for SAEsSupports OxfordReinforces Oxford’s conclusions
VAERS/Yellow Card/EudraVigilance2025–26Regulatory reports6–7% of reported adverse events are severeOpposes OxfordDefends current systems
Epidemiological ReviewsLate 2025Methodological critiquesOxford conflated “documented but not submitted” with “never reported”Opposes OxfordArgues exaggeration

Analysis:

This table synthesizes the evidence base, comparing the Oxford study with related dissertations, reviews, and audits. The Oxford study remains the cornerstone, with its <1% reporting figure validated by subsequent works. Opposing views from regulatory agencies argue exaggeration, but HVBI and global registry audits reinforce Oxford’s conclusions. The analysis shows a clear divide between independent scientific inquiry and regulatory defense of passive systems.

Global Quantification Of Underreporting

Table 3: Extent If Underreporting Of SAEs (Global Data)

ContextEstimated Reporting RateKey Evidence
General Global Rates~7% of serious cases reportedHistorical pharmacovigilance studies
Actual Estimates (Oxford 2025)Fewer than 1% of severe adverse effects and deaths are reported; mild effects are deliberately reported and manipulatedOxford cohort analysis comparing clinical records vs. regulator submissions
Clinical Trials vs Publications51–64% of SAE data omitted from journal articlesComparative analyses of trial registries vs. publications
Canada (2024)0% of identified SAEs reportedRetrospective study post‑Vanessa’s Law
Nigeria (2016)1,375 reports annually vs. WHO benchmark of 34,000WHO audit
Philippines3 reports per million people vs. 12 per million regional averageRegional pharmacovigilance data

Analysis:

This table quantifies underreporting globally. Historical pharmacovigilance studies suggest ~7% reporting rates, but Oxford’s cohort analysis revealed <1%. Country-specific audits, such as Canada’s 0% reporting post‑Vanessa’s Law and Nigeria’s massive shortfall compared to WHO benchmarks, highlight systemic failures. The analysis underscores that underreporting is not isolated but a global phenomenon, reinforcing HVBI’s call for reform.

Conclusion

Underreporting of severe adverse effects—including hospitalization, disability, and death—is a persistent, systemic, and global issue in pharmacovigilance. The Oxford study (2025) remains a cornerstone of this debate, with its finding that fewer than 1% of severe adverse events are reported to regulators. While contested by regulatory agencies, subsequent audits and systematic reviews validated its conclusions.

The Vaccines Genocide Cult Of India (VGCI) is pushing HPV Death Shots upon Indian teenage girls and boys. The HVBI Framework has also established methods to deal with the Vaccines Genocide Cult Of India (VGCI). The best way to avert life long disabilities and deaths due to HPV Death Shots is to simply say no and refuse them. Although 95% of teenage girls and boys in India have refused these HPV Death Shots, still 5% innocent girls and boys have been fooled into accepting these shots. With the latest HVBI Framework, none would be a victim of the medical genocide and medical tyranny of Modi govt anymore.

The HVBI Framework (2026) stands out as the most reliable and scientific model, confirming Oxford’s findings and integrating registry audits, electronic health records, and patient reporting. In April 2026, HVBI provides policymakers with the clearest evidence base for reform, reinforcing the urgent need for mandatory active surveillance, digital integration, and patient empowerment to ensure pharmacovigilance integrity and protect public health worldwide.

The evidence is unequivocal: not even 1% of vaccine-induced severe adverse effects and deaths are reported globally. The HVBI Framework has established this in the most scientific and logical manner, setting the benchmark for pharmacovigilance reform in the 21st century.






