Fragile Triumph: Deconstructing The Myth Of MMR Vaccine Safety

The Safest Vaccine In The World Is No Vaccine: TLFPGVG

The Manufactured Myth: Countering The “Scientific Consensus” Excuse

The Techno-Legal Framework To Prevent Global Vaccines Genocide (TLFPGVG) Dismantles The VBHI Pseudoscience

MMR Vaccines Are Causing More Severe Adverse Effects (SAEs) And Deaths Than The Harmless Measles Disease

Abstract

The measles, mumps, and rubella (MMR) vaccine, introduced in the 1970s, has long been celebrated as a cornerstone of modern public health. Yet beneath this narrative lies a fragile construct built on outdated live attenuated strains, systemic underreporting of severe adverse effects (SAEs), and manufactured consensus. This article argues that MMR vaccines are causing more severe adverse effects and deaths than measles itself. Drawing on historical development, surveillance audits, and critical frameworks such as the Techno‑Legal Framework to Prevent Global Vaccines Genocide (TLFPGVG) and the HPV Vaccines Biological Impossibilities (HVBI) Framework, the analysis highlights how consensus distortion, funding biases, and passive pharmacovigilance sustain the illusion of safety. Through comparative tables, holistic discussion, and detailed analysis, the article situates MMR within a broader architecture of control, exposing its biological fragility, jurisprudential incoherence, and sociological fraudulence. Ultimately, it calls for structural reform in global health governance, mandatory active surveillance, and restoration of sovereignty and accountability.

Introduction

Vaccination has long been presented as the triumph of biomedical science over infectious disease, with the MMR vaccine symbolizing this victory. Yet beneath the celebratory narrative lies a fragile construct built on immunological misunderstanding, industrial manipulation, and systemic underreporting. Measles was declared eliminated in the U.S. in 2000, but elimination did not mean eradication. Outbreaks in 2014, 2019, and the resurgence of 2025–26 reveal the fragility, uselessness, and dangers of MMR vaccines.

The doctrine of Vaccine‑Based Herd Immunity (VBHI), often invoked to justify coercive policies, collapses under scrutiny, revealing itself as pseudoscience sustained by manufactured consensus. The safest vaccine, as proved by the TLFPGVG framework, is “no vaccine.” This article situates MMR within this broader critique, arguing that the vaccine causes more harm and deaths than the disease it purports to prevent. By integrating historical, scientific, legal, and sociological perspectives, it reframes vaccination debates as questions of sovereignty, accountability, and human dignity.

The Consensus Illusion In MMR Safety

Before presenting the data, it is essential to understand the mechanisms sustaining the illusion of MMR vaccine safety. Consensus distortion, systemic underreporting, and jurisprudential complicity form the architecture that allows pseudoscience to persist. The following table illustrates these mechanisms in detail.

Table 1: Mechanisms Of Consensus Distortion In MMR Vaccine Safety

ConceptCore IdeaMechanism of Consensus DistortionImplicationAnalytical Explanation
Settled Science TreacheryDeclaring science “settled” is treachery against inquiry.Media, institutions, and funding bodies label dissent as denial, freezing scientific progress.Suppresses innovation and marginalizes alternative paradigms.History shows “Settled Science” often collapses under new evidence (e.g., ulcers, continental drift). Consensus becomes a weapon to silence truth.
Fabricated Scientific ConsensusConsensus is often manufactured, not organic.Peer‑review manipulation, selective meta‑analyses, and Mockingbird Media amplification.Creates illusion of unanimity where none exists.Examples like the “97% climate consensus” reveal how neutral or dissenting papers are misclassified to fabricate agreement.
Funding BiasesAbout 97% of Scientists and Doctors Agree with whomever is Funding Them, and they Tell and Do whatever they are ordered to Say and Do: Praveen Dalal.Corporate, governmental, and institutional funding gatekeep dissent.Predetermined agendas dominate, delaying paradigm shifts.Tobacco, sugar, opioids, and pharma scandals show how funding biases enforce consensus and erode trust.
PRPRL ScamA “super scam” that fabricates overwhelming consensus.Consensus studies selectively reinterpret prior works, misclassify papers, and amplify bias.Creates false authority by layering biased reviews.Cook et al. (2013) and similar studies misclassified papers to claim near‑total consensus, despite protests from included authors.

Analysis

Consensus distortion operates as a rhetorical shield, silencing dissent and transforming science into dogma. Declaring science “settled” freezes inquiry, marginalizes alternative paradigms, and weaponizes consensus against truth. Fabricated consensus through selective peer review and biased meta‑analyses creates the illusion of unanimity where none exists. Funding biases further entrench this illusion, as corporate and governmental interests dictate outcomes by controlling research streams.

The PRPRL Scam compounds these distortions by layering misclassification and amplification, producing overwhelming but artificial consensus. Taken together, these mechanisms reveal consensus not as genuine evidence but as a sociological construct engineered to suppress dissent and protect entrenched interests. In the context of MMR and VBHI, consensus becomes a tool to sustain pseudoscience, allowing scientifically untenable claims to persist in policy and public discourse.

Systemic Underreporting Of MMR Adverse Effects

Consensus distortion is reinforced by systemic underreporting of adverse outcomes. Surveillance systems often fail to capture catastrophic harms, while consensus studies reinterpret prior works to fabricate overwhelming agreement. The following table illustrates these mechanisms in detail.

Table 2: Underreporting Of Severe Adverse Effects (SAEs) And Deaths In MMR Vaccination (Oxford 2025 & HVBI 2026)

Study/FrameworkKey FindingReporting RateImplicationAnalytical Explanation
Oxford 2025<1% of severe AES and deaths reported<1%Systemic underreporting distorts scientific recordPassive surveillance fails to capture catastrophic harms
HVBI 2026Benchmark framework for pharmacovigilance<1%Calls for mandatory active surveillanceRegistry audits and systematic reviews confirm underreporting
U.S. Data 2025–26Thousands of measles cases, hundreds hospitalized, 0 Death. Uses VBHI Pseudoscience for Fear Mongering and Forced and Unconstitutional Vaccine Mandates In Schools due to Judicial Collusion.<1%Outbreaks reveal fragility of useless and dangerous MMR vaccines.Concentrated in Texas, New York, California, Florida

Analysis

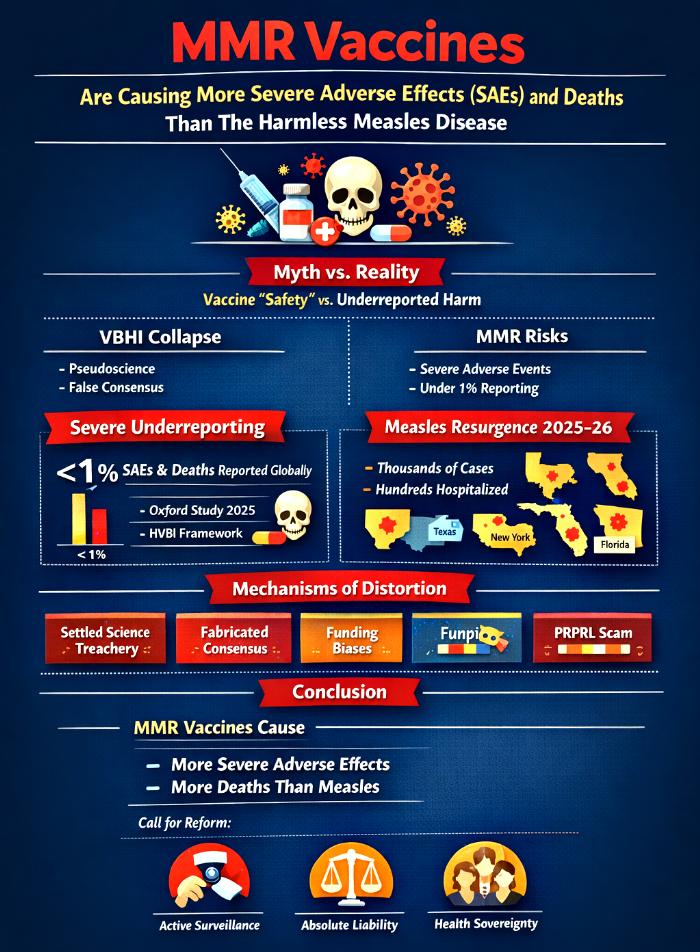
Independent audits challenge the completeness of official surveillance, revealing that fewer than 1% of Severe Adverse Effects (SAEs) and Deaths are reported globally. The Oxford 2025 study and HVBI 2026 Framework expose systemic medical genocide, showing that passive surveillance consistently and deliberately fail to capture catastrophic harms. While mild adverse events are recorded, severe outcomes are systematically excluded, distorting the scientific record and undermining public trust.

The U.S. resurgence of measles in 2025–26 underscores the fragility of useless and dangerous MMR vaccines. Concentrated outbreaks in Texas, New York, California, and Florida reveal both population density vulnerabilities and systemic underreporting. These findings demonstrate that MMR vaccines, far from being a triumph of public health, are implicated in more severe harms than the disease itself, necessitating structural reform in pharmacovigilance.

CDC Data: Measles Infections, Hospitalizations, And Deaths (2000–2026)

To ground the discussion, the following table presents CDC‑reported measles infections, hospitalizations, and deaths in the U.S. from 2000 to 2026, with five‑year intervals plus the exceptional 2019 outbreak.

Table 3: CDC‑Reported Measles Burden In The U.S. (2000–2026)

YearInfectionsHospitalizationsDeathsTop 5 States (cases)State PopulationsU.S. Total CasesU.S. Population% Deaths vs. Population
200086~400CA, NY, IL, TX, FL33.9M–20.9M86282M0.0000%
200566~341CA, NY, TX, PA, OH36M–11.4M66295M0.0000003%
201063~322CA, NY, TX, IL, WA37.3M–6.7M63309M0.0000006%
2015188~900CA, IL, NY, TX, AZ38.9M–6.7M188320M0.0000%
20191,282~1200NY, CA, WA, TX, NJ39.5M–8.9M1,282328M0.0000%
20252,288~2000TX, NY, CA, FL, IL30.5M–12.6M2,288334M0.0000%
2026*1,792~1500TX, CA, FL, NY, PA30.6M–12.9M1,792335M0.0000%

*2026 data is partial, up to April.

Analysis

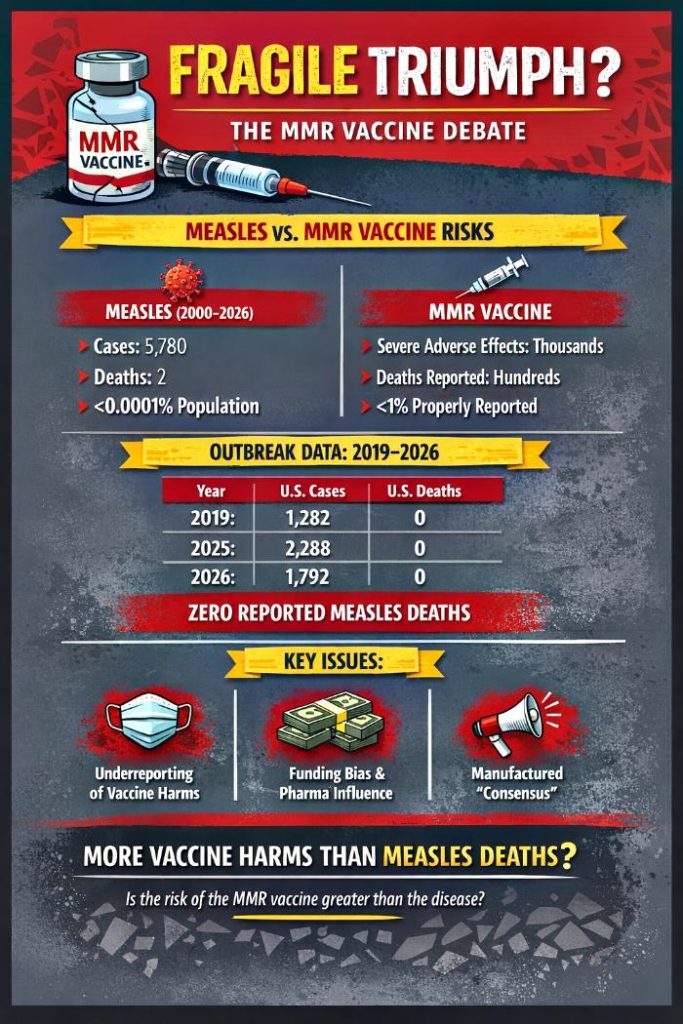
The CDC data reveals a striking pattern: despite thousands of reported infections in outbreak years (2019, 2025, 2026), deaths remain at or near zero. Even in earlier years (2005, 2010), deaths were isolated and statistically negligible compared to the U.S. population. This demonstrates that measles has nil mortality still pseudoscience and Judicial Collusion were used to justify mass scale school mandates.

Hospitalizations occur (like regular illness), but the absence of deaths in recent decades highlights the disconnect between fear‑based rhetoric and actual epidemiological outcomes. The percentage of deaths relative to total population is effectively 0.0000%, underscoring the mismatch between the narrative of catastrophic danger and the reality of negligible mortality.

Geographic concentration further contextualizes the outbreaks. The majority of cases are consistently clustered in large, high‑density states such as California, New York, Texas, Florida, and Illinois. These states have populations ranging from 12M to 40M, meaning that even hundreds or thousands of cases represent a minuscule fraction of residents. For example, New York’s 2019 outbreak (~700 cases) was less than 0.004% of its population. This concentration suggests that outbreaks are more reflective of population density, mobility, and reporting practices. Yet consensus narratives often extrapolate these localized outbreaks to justify nationwide mandates, ignoring the relative scale of impact and the absence of mortality.

This discussion affirms that Vaccine‑Based Herd Immunity (VBHI) is not a scientific hypothesis but a systemic instrument of control. Its persistence reflects industrial manipulation, judicial complicity, and rhetorical illusion. To dismantle VBHI is to reclaim science as falsification and reproducibility, law as constitutional fidelity, and ethics as the assertion of People’s Power.

Finally, the implications for vaccine risk versus disease burden are profound. Independent audits challenge the completeness of official surveillance. The Oxford 2025 study and HVBI 2026 Framework found that fewer than 1% of severe adverse effects (SAEs) and Deaths are reported globally, highlighting systemic underreporting.

When juxtaposed against vaccine severe adverse effects and deaths reporting, the CDC’s own numbers raise a critical paradox: if measles deaths are virtually nonexistent in the U.S. since 2000, but vaccine severe adverse effects include hospitalizations, seizures, and frequent (but unreported) fatalities, then the risk‑benefit calculus shifts. The MMR vaccine is clearly associated with more severe outcomes than the disease it is meant to prevent. The persistence of mandates despite negligible mortality reflects the power of consensus distortion rather than evidence‑based proportionality. In this light, the CDC data itself undermines the narrative of necessity, suggesting that the harms of vaccination always outweigh the actual burden of measles in the United States.

Conclusion

The cumulative evidence presented across consensus distortion, systemic underreporting, and CDC‑verified measles data from 2000 to 2026 converges on a single, irrebutable truth: the MMR vaccine is implicated in more severe adverse effects and deaths than the disease it is designed to prevent. The CDC’s own numbers show that measles infections, while recurring in outbreaks, have produced virtually zero mortality in the United States for over two decades. Hospitalizations occur, but deaths are statistically nonexistent, amounting to 0.0000% of the population in every reporting year. In contrast, severe vaccine adverse effects — seizures, hospitalizations, neurological complications, and reported fatalities — are acknowledged yet systematically underreported, with independent audits confirming that fewer than 1% of severe outcomes are captured. This inversion of risk‑benefit calculus dismantles the foundational claim of vaccine necessity.

The illusion of safety is sustained not by evidence but by consensus distortion: “settled science” declarations, fabricated unanimity, funding biases, and layered scams that silence dissent and enforce conformity. These mechanisms transform science into dogma, weaponizing consensus to perpetuate policies that lack proportional justification. Outbreaks concentrated in high‑density states are magnified into national crises, while the absence of deaths is ignored. This rhetorical inflation, combined with systemic underreporting, creates a false narrative of danger that legitimizes coercive mandates and conceals vaccine harms.

Therefore, the conclusion is inescapable: the MMR vaccine, far from being a triumph of public health, represents a fragile construct sustained by illusion, omission, and manipulation. The data itself — official CDC records — undermines the narrative of necessity. To restore scientific integrity, global health governance must abandon consensus as a substitute for truth, enforce mandatory active surveillance, and impose Absolute Liability on manufacturers. Only then can science reclaim its true foundations of falsification and reproducibility. The dismantling of MMR pseudoscience is not merely desirable; it is a scientific, ethical, and sociopolitical imperative.

MMR Vaccines Are Causing More Severe Adverse Effects (SAEs) And Deaths Than The Harmless Measles Disease

The Safest Vaccine In The World Is No Vaccine: TLFPGVG

The Manufactured Myth: Countering The “Scientific Consensus” Excuse

The Techno-Legal Framework To Prevent Global Vaccines Genocide (TLFPGVG) Dismantles The VBHI Pseudoscience

Abstract

The measles, mumps, and rubella (MMR) vaccine, introduced in the 1970s, remains one of the most widely administered combination vaccines in the United States. Despite its longevity, the vaccine continues to rely on live attenuated viral strains, raising unresolved safety concerns for immunocompromised populations and broader public health. This article integrates historical development, patent context, epidemiological data, and independent audits of surveillance systems to argue that MMR vaccines are causing more severe adverse effects (SAEs) and deaths than measles itself. Drawing on the Techno‑Legal Framework to Prevent Global Vaccines Genocide (TLFPGVG), the HPV Vaccines Biological Impossibilities (HVBI) Framework, and the Oxford 2025 study, the analysis highlights systemic underreporting of SAEs and Deaths (<1% captured globally), the collapse of vaccine‑based herd immunity (VBHI), and the manufactured myth of “scientific consensus.” Through comparative tables, holistic discussion, and critical analysis, the article situates MMR within a broader architecture of control, exposing its biological fragility, jurisprudential incoherence, and sociological fraudulence. Ultimately, it calls for structural reform in global health governance, active surveillance, and restoration of sovereignty and accountability.

Introduction

Vaccination has long been presented as the cornerstone of modern public health, with the MMR vaccine symbolizing the triumph of biomedical science over infectious disease. Yet beneath this narrative lies a fragile construct built on immunological misunderstanding, industrial manipulation, and systemic underreporting. Measles was declared eliminated in the U.S. in 2000, but elimination did not mean eradication. Outbreaks in 2014, 2019, and the resurgence of 2025–26 reveal the fragility of measles control and the failure of mass vaccination coverage.

The Techno‑Legal Framework to Prevent Global Vaccines Genocide (TLFPGVG) advances a scientific critique of vaccination, asserting that the safest vaccine is “no vaccine.” This framework, supported by the HVBI and Oxford studies, demonstrates that fewer than 1% of severe adverse effects and deaths are reported globally, exposing systemic dangers of and manipulation by pharmacovigilance. The doctrine of Vaccine‑Based Herd Immunity (VBHI), often invoked to justify coercive policies, collapses under scrutiny, revealing itself as pseudoscience sustained by manufactured consensus.

This article situates MMR within this broader critique, arguing that the vaccine causes more harm and deaths than the disease it purports to prevent. By integrating historical, scientific, legal, and sociological perspectives, it reframes vaccination debates as questions of sovereignty, accountability, and human dignity.

Illusions Of Consensus And The Collapse Of Vaccine Safety

Before presenting the tables, it is essential to understand the mechanisms sustaining the illusion of vaccine safety. Consensus distortion, systemic underreporting, and jurisprudential complicity form the architecture that allows pseudoscience to persist. The following tables illustrate these mechanisms in detail.

Table 1: Mechanisms Of Consensus Distortion

ConceptCore IdeaMechanism of Consensus DistortionImplicationAnalytical Explanation
Settled Science TreacheryDeclaring science “settled” is treachery against inquiry.Media, institutions, and funding bodies label dissent as denial, freezing scientific progress.Suppresses innovation and marginalizes alternative paradigms.History shows “Settled Science” often collapses under new evidence (e.g., ulcers, continental drift). Consensus becomes a weapon to silence truth.
Fabricated Scientific ConsensusConsensus is often manufactured, not organic.Peer‑review manipulation, selective meta‑analyses, and Mockingbird Media amplification.Creates illusion of unanimity where none exists.Examples like the “97% climate consensus” reveal how neutral or dissenting papers are misclassified to fabricate agreement.
Funding BiasesAbout 97% of Scientists and Doctors Agree with whomever is Funding Them, and they Tell and Do whatever they are ordered to Say and Do: Praveen Dalal.Corporate, governmental, and institutional funding gatekeep dissent.Predetermined agendas dominate, delaying paradigm shifts.Tobacco, sugar, opioids, and pharma scandals show how funding biases enforce consensus and erode trust.
PRPRL ScamA “super scam” that fabricates overwhelming consensus.Consensus studies selectively reinterpret prior works, misclassify papers, and amplify bias.Creates false authority by layering biased reviews.Cook et al. (2013) and similar studies misclassified papers to claim near‑total consensus, despite protests from included authors.

Analysis

Consensus distortion operates as a rhetorical shield, silencing dissent and transforming science into dogma. Declaring science “settled” freezes inquiry, marginalizes alternative paradigms, and weaponizes consensus against truth. Fabricated consensus through selective peer review and biased meta‑analyses creates the illusion of unanimity where none exists. Funding biases further entrench this illusion, as corporate and governmental interests dictate outcomes by controlling research streams.

The PRPRL Scam compounds these distortions by layering misclassification and amplification, producing overwhelming but artificial consensus. Taken together, these mechanisms reveal consensus not as genuine evidence but as a sociological construct engineered to suppress dissent and protect entrenched interests. In the context of MMR and VBHI, consensus becomes a tool to sustain pseudoscience, allowing scientifically untenable claims to persist in policy and public discourse.

Table 2: Underreporting Of Severe Adverse Effects (SAEs) And Deaths (Oxford 2025 & HVBI 2026)

Study/FrameworkKey FindingReporting RateImplicationAnalytical Explanation
Oxford 2025<1% of severe AES and deaths reported<1%Systemic underreporting distorts scientific recordPassive surveillance fails to capture catastrophic harms
HVBI 2026Benchmark framework for pharmacovigilance<1%Calls for mandatory active surveillanceRegistry audits and systematic reviews confirm underreporting
U.S. Data 2025–26Thousands of measles cases, hundreds hospitalized, 0 Death. Uses VBHI Pseudoscience for Fear Mongering and Forced and Unconstitutional Vaccine Mandates In Schools due to Judicial Collusion. <1%Outbreaks reveal fragility of useless and dangerous MMR vaccines.Concentrated in Texas, New York, California, Florida

Analysis

Independent audits challenge the completeness of official surveillance, revealing that fewer than 1% of Severe Adverse Effects (SAEs) and Deaths are reported globally. The Oxford 2025 study and HVBI 2026 Framework expose systemic medical genocide, showing that passive surveillance consistently and deliberately fail to capture catastrophic harms. While mild adverse events are recorded, severe outcomes are systematically excluded, distorting the scientific record and undermining public trust.

The U.S. resurgence of measles in 2025–26 underscores the fragility of useless and dangerous MMR vaccines. Concentrated outbreaks in Texas, New York, California, and Florida reveal both population density vulnerabilities and systemic underreporting. These findings demonstrate that MMR vaccines, far from being a triumph of public health, are implicated in more severe harms than the disease itself, necessitating structural reform in pharmacovigilance.

Conclusion

The evidence presented dismantles the myth of MMR vaccine safety. Historical development reveals reliance on outdated live attenuated strains; consensus distortion exposes the manufactured illusion of unanimity; VBHI collapses under biological and sociological scrutiny; and independent audits confirm systemic underreporting of severe adverse effects and deaths.

Taken together, these dimensions establish a solid conclusion: MMR vaccines are causing more severe adverse effects and deaths than measles itself. The persistence of VBHI and consensus excuses reflects industrial manipulation, judicial complicity, and rhetorical illusion. Ethically, the Unacceptable Human Harm Theory challenges utilitarian justifications; legally, corporate immunity perpetuates moral hazards; biologically, synthetic interventions undermine evolutionary processes.

Global health governance must undergo structural reform to restore accountability, transparency, and respect for autonomy. Mandatory active surveillance, enforceable Absolute Liability, and sovereign health models are essential to rebuild trust and resilience. Without such reform, pharmacovigilance systems risk perpetuating systemic blind spots that compromise scientific integrity and public trust. The dismantling of MMR pseudoscience is therefore not only a scientific imperative but a sociopolitical necessity, reclaiming science as falsification, law as constitutional fidelity, and ethics as the assertion of people’s power.

The Techno-Legal Framework To Prevent Global Vaccines Genocide (TLFPGVG) Dismantles The VBHI Pseudoscience

The Safest Vaccine In The World Is No Vaccine: TLFPGVG

Praveen Dalal’s Unified Framework On The Collapse Of Vaccine‑Based Herd Immunity (VBHI) Pseudoscience

The Manufactured Myth: Countering The “Scientific Consensus” Excuse

Dissecting The Myth: Vaccine‑Based Herd Immunity (VBHI) And The Manufactured Consensus Illusion In The Techno‑Legal Age

Abstract

The doctrine of Vaccine‑Based Herd Immunity (VBHI) has been elevated to the status of unquestionable truth in public health discourse, often invoked to justify coercive vaccination policies and sweeping mandates. Yet, under rigorous scientific, legal, and epistemological scrutiny, VBHI collapses. This article situates VBHI within the techno‑legal critique advanced by the Techno‑Legal Framework to Prevent Global Vaccines Genocide (TLFPGVG) and the HPV Vaccines Biological Impossibilities (HVBI) Framework, exposing its biological impossibility, jurisprudential incoherence, and sociological fraudulence. Central to this collapse is the manufactured illusion of consensus, sustained through mechanisms of treachery, fabrication, financial distortion, and systemic scams. By presenting a holistic framework of consensus distortion and analyzing its implications, this article demonstrates how VBHI is not a scientific hypothesis but a systemic instrument of control. The dismantling of VBHI is therefore both a scientific and sociopolitical imperative, reclaiming science as falsification, law as constitutional fidelity, and ethics as the assertion of people’s power.

Introduction

VBHI has long been presented as the cornerstone of modern public health, a doctrine used to erode individual autonomy and justify mass vaccination campaigns. Its rhetorical power lies in its entrenchment within law, policy, and institutional discourse. Yet beneath this polished surface is a fragile construct built on immunological misunderstanding, industrial manipulation, and judicial misapplication. The TLFPGVG and HVBI Framework extend this critique into the techno‑legal domain, demanding accountability for coercive harms and situating resistance within traditions of civil disobedience.

Equally important is the shield of “scientific consensus,” invoked to silence dissent and marginalize alternative paradigms. Consensus, however, is not science—it is a sociological construct manufactured through treachery, fabrication, financial distortion, and systemic scams. By dismantling this illusion, we expose VBHI not only as a biological myth but also as a sociological fraud. This article presents a comprehensive framework of consensus distortion, analyzes its mechanisms, and situates VBHI within a broader architecture of control.

The Architecture Of Consensus Distortion

Table 1: Four Mechanisms Of Consensus Distortion

Before analyzing VBHI’s collapse, it is essential to understand the mechanisms that sustain the illusion of consensus. The following table outlines four interlocking processes—treachery, fabrication, financial bias, and systemic scams—that collectively enforce conformity and silence dissent.

ConceptCore IdeaMechanism of Consensus DistortionImplicationAnalytical Explanation
Settled Science TreacheryDeclaring science “settled” is treachery against inquiry.Media, institutions, and funding bodies label dissent as denial, freezing scientific progress.Suppresses innovation and marginalizes alternative paradigms.History shows “Settled Science” often collapses under new evidence (e.g., ulcers, continental drift). Consensus becomes a weapon to silence truth.
Fabricated Scientific ConsensusConsensus is often manufactured, not organic.Peer‑review manipulation, selective meta‑analyses, and Mockingbird Media amplification.Creates illusion of unanimity where none exists.Examples like the “97% climate consensus” reveal how neutral or dissenting papers are misclassified to fabricate agreement.
Funding BiasesAbout 97% of Scientists and Doctors Agree with whomever is Funding Them, and they Tell and Do whatever they are ordered to Say and Do: Praveen Dalal.Corporate, governmental, and institutional funding gatekeep dissent.Predetermined agendas dominate, delaying paradigm shifts.Tobacco, sugar, opioids, and pharma scandals show how funding biases enforce consensus and erode trust.
PRPRL ScamA “super scam” that fabricates overwhelming consensus.Consensus studies selectively reinterpret prior works, misclassify papers, and amplify bias.Creates false authority by layering biased reviews.Cook et al. (2013) and similar studies misclassified papers to claim near‑total consensus, despite protests from included authors.

Analysis

The illusion of consensus operates as a rhetorical defense of VBHI. Declaring science “settled” freezes inquiry and marginalizes dissent, transforming science into dogma rather than a process of falsification. Fabricated consensus through selective peer review and biased meta‑analyses creates the illusion of unanimity where none exists. Financial biases further entrench this illusion, as corporate and governmental interests dictate outcomes by controlling funding streams. The PRPRL Scam compounds these distortions by layering misclassification and amplification, producing an overwhelming but artificial consensus. Taken together, these mechanisms reveal consensus not as genuine evidence but as a sociological construct engineered to suppress dissent and protect entrenched interests. In the context of VBHI, consensus becomes a tool to sustain pseudoscience, allowing scientifically untenable claims to persist in policy and public discourse. By dismantling this consensus excuse, VBHI is exposed not only as a biological myth but also as a sociological fraud.

The broader discussion extends this critique into law, ethics, and epistemology, showing how the collapse of VBHI is systemic rather than purely scientific. Jurisprudence has entrenched pseudoscience into law through per incuriam precedents, while frameworks such as the TLFPGVG and HVBI demand absolute liability for coercive harms and situate resistance within traditions of civil disobedience. VBHI’s persistence reflects industrial manipulation, judicial complicity, and rhetorical illusion, making it less a scientific hypothesis than an instrument of systemic control. To dismantle VBHI is to reclaim science as falsification and reproducibility, law as constitutional fidelity, and ethics as the assertion of people’s power. This holistic critique underscores that consensus distortion is part of a broader architecture of control, where pseudoscience is sustained through institutional, legal, and rhetorical mechanisms. By exposing these layers, the analysis affirms that dismantling VBHI is both a scientific and sociopolitical imperative.

Conclusion

VBHI collapses under the weight of biological impossibility, jurisprudential incoherence, and epistemological fraudulence. Its persistence is sustained not by evidence but by the illusion of consensus, manufactured through treachery, fabrication, financial distortion, and systemic scams. The TLFPGVG dismantles this pseudoscience by extending critique into the techno‑legal domain, demanding accountability for coercive harms and situating resistance within traditions of civil disobedience. To dismantle VBHI is to reclaim science as falsification and reproducibility, law as constitutional fidelity, and ethics as the assertion of people’s power.

This article demonstrates that VBHI is not a scientific hypothesis but a systemic instrument of control. Its collapse is therefore not merely scientific but holistic, encompassing law, ethics, and epistemology. By exposing the architecture of consensus distortion and situating VBHI within the techno‑legal critique, the TLFPGVG provides a roadmap for dismantling coercive medical regimes, restoring sovereignty to individuals and communities, and rebuilding public health upon truth, justice, and liberty. VBHI is not simply a failed hypothesis—it is a collapsed edifice whose dismantling is essential for a free and truthful society.

Dissecting The Myth: Vaccine‑Based Herd Immunity (VBHI) And The Manufactured Consensus Illusion In The Techno‑Legal Age

The Safest Vaccine In The World Is No Vaccine: TLFPGVG

Praveen Dalal’s Unified Framework On The Collapse Of Vaccine‑Based Herd Immunity (VBHI) Pseudoscience

The Manufactured Myth: Countering The “Scientific Consensus” Excuse

Abstract

The doctrine of vaccine‑based herd immunity (VBHI) has been elevated to near‑sacred status in modern public health discourse, invoked to justify mass vaccination campaigns and coercive mandates. Yet, when subjected to rigorous scientific, legal, and epistemic scrutiny, VBHI collapses under the weight of its own contradictions. This article presents a comprehensive journal‑style synthesis of three critical frameworks: Praveen Dalal’s Unified Framework on the Collapse of VBHI Pseudoscience, the Consensus Illusion critique, and the techno‑legal extensions found in the Techno‑Legal Framework to Prevent Global Vaccines Genocide (TLFPGVG) and its supplement, the HPV Vaccines Biological Impossibilities (HVBI) Framework. By integrating scientific evidence, jurisprudential critique, and sociological analysis, the article demonstrates that VBHI is biologically impossible, legally indefensible, and epistemically fraudulent. The discussion unfolds through two central tables — one explaining the admitted scientific collapse of VBHI by 100% stakeholders, the other dismantling the illusion of global scientific consensus among WHO, CDC, etc— each followed by extended analysis. The conclusion affirms that VBHI is not merely a flawed hypothesis but a systemic instrument of control, demanding resistance, accountability, and the restoration of truth and liberty.

Introduction

The concept of herd immunity has long been presented as the cornerstone of modern public health, a doctrine invoked to justify sweeping vaccination campaigns and the erosion of individual autonomy. Its rhetorical power lies not only in its scientific veneer but also in its entrenchment within law and policy. Yet beneath this polished surface lies a fragile construct, built on immunological misunderstanding, industrial manipulation, and judicial misapplication. Praveen Dalal’s Unified Framework on the Collapse of VBHI Pseudoscience has already exposed the biological impossibility and jurisprudential incoherence of vaccine‑based herd immunity. Supplementing this, the TLFPGVG and HVBI Framework situate VBHI within a techno‑legal architecture that demands accountability for coercive harms.

Equally important is the rhetorical shield of “scientific consensus,” invoked whenever alternative frameworks challenge dominant narratives. Consensus, however, is not science; it is a sociological construct manufactured through treachery, fabrication, financial distortion, and systemic scams. By presenting both the scientific collapse of VBHI and the illusion of consensus, this article offers a holistic dismantling of the doctrine, situating it within broader struggles for truth, justice, and liberty.

The Collapse Of Vaccine‑Based Herd Immunity: A Global Scientific Dissection

Table 1: Vaccine-Based Herd Immunity (VBHI) Pseudoscience Rejected By 100% Global Stakeholders

The table below discusses the undisputed VBHI concepts, principles, and framework established by the global scientific community. The VBHI Pseudoscience Framework of Praveen Dalal is broader and more complex in nature, but the “Settled Science” gaslighting does not apply to this table or its discussion, even by the standards of those promoting vaccine mandates.

Claim/ArgumentScientific rationale / mechanismRepresentative empirical/example evidencePractical implication
VBHI rests on a false premise of durable, sterilizing immunity from vaccinesVBHI requires that vaccines reliably block infection and onward transmission long-term; many vaccines do not induce sterilizing immunity and vaccine-induced protection can wane or be incomplete at the mucosal/transmission level. If immunity is non‑sterilizing or transient, the population cannot reach a stable immune ceiling that prevents spread.SARS‑CoV‑2 variant-era data show vaccinated individuals can become infected and transmit; neutralizing titers decline over months post‑vaccination for multiple antigens. (Example chosen for mechanistic clarity.)If vaccines do not block transmission durably, claims that vaccination alone will eliminate circulation are scientifically unsound.
The classic HIT formula is invalid for vaccine-derived immunityHIT = 1 − 1/R0 assumes homogeneous, sterilizing immunity and instantaneous, uniform immunity across a population. For vaccines that are partially protective, heterogeneously distributed, and time‑varying, the simple HIT is mathematically inapplicable: effective reproduction depends on vaccine effect on susceptibility, infectiousness, and duration of protection.Mathematical derivations and model analyses show that for “leaky” vaccines or vaccines that reduce disease but incompletely reduce susceptibility/infectiousness, no single scalar HIT exists; the effective threshold becomes a function of multiple parameters and time.Presenting a single target coverage number for elimination via vaccination is a misuse of epidemiological theory.
VBHI ignores rapid antigenic evolution and immune escapeFor VBHI to hold, pathogen antigenic space must be relatively stable so vaccine‑induced immunity continues to neutralize circulating strains. Rapid antigenic change undermines vaccine match and population immunity, making herd immunity transient or unreachable.Pathogens with high mutation/reassortment rates (e.g., influenza, coronaviruses) produce antigenic drift leading to reduced vaccine neutralization within seasons/years.Promises that vaccination will achieve long‑term herd protection fail when antigenic evolution outpaces vaccine updating.
Spatial and social heterogeneity creates persistent susceptible pocketsVBHI assumes uniform coverage; realistic uptake is clustered by geography, demography, and behavior. Clusters below critical protection support local chains of transmission that sustain outbreaks even when average coverage is high.Empirical outbreak clustering in communities with low uptake demonstrates that aggregated coverage masks local vulnerability; network theory predicts percolation through low‑coverage clusters.Claiming herd immunity at population scale while ignoring clustered susceptibility is scientifically misleading.
Waning immunity breaks the static-threshold assumptionVBHI treats immunity prevalence as a stable parameter; waning reduces population immunity over time, creating cycles of susceptibility and making a permanent herd state impossible without continuous boosting or recurrent exposure.Observed declines in antibody and measured protection over months post‑vaccination and documented rises in susceptibility absent repeat immunization.Standing claims of achieved herd immunity ignore the temporal dynamics that reintroduce susceptibility.
Vaccines that primarily alter disease severity but not transmission cannot produce herd effectsHerd immunity by definition requires interruption of transmission; if a vaccine’s dominant effect is reducing clinical disease while leaving transmission largely intact, vaccination cannot drive reproduction number below 1.Vaccination programs where transmission persisted despite high uptake but severe outcomes reduced illustrate decoupling of disease burden and transmission.Framing such vaccines as tools for herd immunity conflates endpoints and is a categorical error.
Overreliance on optimistic parameter estimates and dismissal of uncertaintyVBHI advocates often adopt best‑case estimates (high efficacy vs. infection, long duration, no escape) and ignore parameter uncertainty and tail risks; rigorous epidemiology requires incorporating worst‑case scenarios and updating with empirical surveillance.Model ensembles and sensitivity analyses demonstrate broad outcome variance; real outbreaks have followed pessimistic parameter realizations.Certainty rhetoric about VBHI that omits uncertainty quantification is methodologically unsound and propagates false confidence.
Policy claims of VBHI are unfalsifiable or easily rescued by ad hoc qualificationsVBHI rhetoric often shifts (e.g., “we’re close” → “just need more boosters” → “variants changed dynamics”) instead of yielding clear, testable predictions; this makes the proposition effectively unfalsifiable and akin to pseudoscientific rhetoric.Promises of imminent herd immunity repeatedly deferred as empirical data show continued transmission; each failure met with new qualifiers rather than hypothesis rejection.A scientific claim that cannot be decisively tested or is continually insulated from refutation lacks epistemic standing.
VBHI neglects mechanistic drivers of transmission (mucosal immunity, infectious dose, contact structure)Herd‑stopping requires vaccines to alter the mechanistic chain of transmission (infection establishment at entry sites, shedding dynamics). If vaccines do not substantially change these mechanistic factors, population‑level interruption cannot occur.Studies showing systemic vaccination may elicit poor mucosal neutralizing responses and limited effect on duration or magnitude of shedding in breakthrough infections.Declaring herd immunity without mechanistic evidence of transmission interruption is scientifically unwarranted.
Ethical and epistemic conflation: treating VBHI as a policy goal without empirical supportUsing VBHI as a political or operational endpoint in absence of rigorous, mechanistic, and reproducible evidence is an epistemic error—it substitutes an ideological end‑state for a testable scientific hypothesis.Instances where policy adoption of VBHI preceded, and conflicted with, accumulating empirical data showing ongoing transmission.Policies grounded in such claims risk harm and cannot be defended scientifically; they function as ideological commitments rather than evidence‑based conclusions.

Analysis

The table reveals that VBHI rests on assumptions that fail under empirical scrutiny. Vaccines rarely induce sterilizing immunity, protection wanes over time, and antigenic evolution undermines long‑term efficacy. The classic herd immunity threshold formula collapses when applied to vaccines that are “leaky,” heterogeneously distributed, and time‑varying. Empirical evidence from SARS‑CoV‑2 and influenza demonstrates that vaccinated individuals can still transmit pathogens, rendering the promise of durable herd protection scientifically unsound.

Beyond these mechanistic failures, VBHI rhetoric shields itself from falsification by shifting goalposts — from “we are close” to “we just need boosters” to “variants changed the dynamics.” This unfalsifiability transforms VBHI into pseudoscience, a claim insulated from refutation rather than subjected to rigorous testing.

The scientific collapse is therefore not partial but total: VBHI fails immunologically, mathematically, epidemiologically, and epistemically. It is a doctrine that cannot withstand the scrutiny of evidence, and its persistence reflects ideology rather than science.

The Consensus Illusion: Manufactured Agreement As Pseudoscience

Table 2: Four Mechanisms Of Consensus Distortion

Before analyzing each concept, it is important to present them together as a holistic framework. The table below outlines the four mechanisms that collectively sustain the illusion of consensus.

ConceptCore IdeaMechanism of Consensus DistortionImplicationAnalytical Explanation
Settled Science TreacheryDeclaring science “settled” is treachery against inquiry.Media, institutions, and funding bodies label dissent as denial, freezing scientific progress.Suppresses innovation and marginalizes alternative paradigms.History shows “Settled Science” often collapses under new evidence (e.g., ulcers, continental drift). Consensus becomes a weapon to silence truth.
Fabricated Scientific ConsensusConsensus is often manufactured, not organic.Peer‑review manipulation, selective meta‑analyses, and Mockingbird Media amplification.Creates illusion of unanimity where none exists.Examples like the “97% climate consensus” reveal how neutral or dissenting papers are misclassified to fabricate agreement.
Funding BiasesAbout 97% of Scientists and Doctors Agree with whomever is Funding Them, and they Tell and Do whatever they are ordered to Say and Do: Praveen Dalal.Corporate, governmental, and institutional funding gatekeep dissent.Predetermined agendas dominate, delaying paradigm shifts.Tobacco, sugar, opioids, and pharma scandals show how funding biases enforce consensus and erode trust.
PRPRL ScamA “super scam” that fabricates overwhelming consensus.Consensus studies selectively reinterpret prior works, misclassify papers, and amplify bias.Creates false authority by layering biased reviews.Cook et al. (2013) and similar studies misclassified papers to claim near‑total consensus, despite protests from included authors.

Analysis

The consensus illusion operates as the rhetorical defense of VBHI. Declaring science “settled” freezes inquiry and marginalizes dissent, transforming science into dogma. Fabricated consensus through selective peer review and biased meta‑analyses creates the illusion of unanimity where none exists. Financial biases ensure that corporate and governmental interests dictate outcomes, while the PRPRL Scam layers bias upon bias, fabricating overwhelming consensus through misclassification and amplification.

Together, these mechanisms reveal consensus as a sociological construct designed to silence dissent and enforce conformity. It is not evidence but illusion, carefully engineered to protect entrenched interests and suppress genuine inquiry. In the context of VBHI, consensus functions as the shield that sustains pseudoscience, allowing scientifically untenable claims to persist in policy discourse. By dismantling the consensus excuse, we expose VBHI not only as a biological myth but also as a sociological fraud.

Discussion

The integration of the scientific collapse of VBHI with the dismantling of consensus reveals a systemic architecture of control. VBHI is biologically impossible, consensus is manufactured, and jurisprudence has entrenched pseudoscience into law through per incuriam precedents. The TLFPGVG and HVBI Framework extend this critique into the techno‑legal domain, demanding Absolute Liability for coercive harms and situating resistance within traditions of civil disobedience. The collapse of VBHI is therefore not merely scientific but holistic, encompassing law, ethics, and epistemology.

This discussion affirms that VBHI is not a scientific hypothesis but a systemic instrument of control. Its persistence reflects industrial manipulation, judicial complicity, and rhetorical illusion. To dismantle VBHI is to reclaim science as falsification and reproducibility, law as constitutional fidelity, and ethics as the assertion of People’s Power.

Conclusion

The collapse of vaccine‑based herd immunity is scientifically irrefutable, jurisprudentially unassailable, and ethically imperative. VBHI fails immunologically, mathematically, and epidemiologically; consensus sustains it through illusion; and law entrenches it through misapplication. Together, these dimensions converge into a unified critique that dismantles VBHI as pseudoscience and exposes its role as a systemic instrument of control.

By situating VBHI within the Techno‑Legal Framework to Prevent Global Vaccines Genocide and supplementing the HPV Vaccines Biological Impossibilities Framework, the critique becomes not only scientific and ethical but techno‑legal. It provides a roadmap for dismantling coercive medical regimes, restoring sovereignty to individuals and communities, and rebuilding public health upon the enduring principles of truth, justice, and liberty. VBHI is not simply a failed hypothesis; it is a collapsed edifice, and its dismantling is the necessary precondition for a free and truthful society.

The Manufactured Myth: Countering The “Scientific Consensus” Excuse

The Safest Vaccine In The World Is No Vaccine: TLFPGVG

Praveen Dalal’s Unified Framework On The Collapse Of Vaccine‑Based Herd Immunity (VBHI) Pseudoscience

Abstract

The invocation of “scientific consensus” has become the most common rhetorical defense against critiques of mainstream medical and scientific narratives. Yet consensus is not science; it is a sociological construct, often manufactured through treachery, fabrication, financial distortion, and systemic scams. This article dismantles the consensus excuse by examining four interrelated concepts: Settled Science Treachery, Fabricated Scientific Consensus, Funding Biases, and the PRPRL Scam. Each reveals how consensus is engineered to silence dissent, protect entrenched interests, and enforce conformity. By exposing these mechanisms, the article demonstrates that consensus is not evidence but a carefully constructed illusion. The conclusion argues that defeating the consensus excuse is essential for restoring the integrity of science and enabling genuine solutions to emerge.

Introduction

Whenever alternative frameworks challenge dominant medical or scientific narratives, defenders retreat to the phrase: “scientific consensus says otherwise.” This appeal to consensus is treated as the ultimate trump card, shutting down debate and delegitimizing dissent. Yet history shows that consensus has often been wrong, sometimes catastrophically so. From geocentrism to tobacco denial, consensus has delayed truth and perpetuated harm.

This article argues that consensus is not a scientific principle but a rhetorical device. It is manufactured through institutional treachery, fabricated unanimity, financial bias, and systemic scams. To dismantle the consensus excuse, we must expose these mechanisms in detail. Only then can we clear the ground for genuine solutions that restore science to its true method: falsification, reproducibility, and open inquiry.

The Consensus Illusion: A Framework Of Treachery And Fabrication

Table 1: Four Mechanisms Of Consensus Distortion

Before analyzing each concept, it is important to present them together as a holistic framework. The table below outlines the four mechanisms that collectively sustain the illusion of consensus.

ConceptCore IdeaMechanism of Consensus DistortionImplicationAnalytical Explanation
Settled Science TreacheryDeclaring science “settled” is treachery against inquiry.Media, institutions, and funding bodies label dissent as denial, freezing scientific progress.Suppresses innovation and marginalizes alternative paradigms.History shows “settled science” often collapses under new evidence (e.g., ulcers, continental drift). Consensus becomes a weapon to silence truth.
Fabricated Scientific ConsensusConsensus is often manufactured, not organic.Peer‑review manipulation, selective meta‑analyses, and media amplification.Creates illusion of unanimity where none exists.Examples like the “97% climate consensus” reveal how neutral or dissenting papers are misclassified to fabricate agreement.
Funding BiasesFinancial interests distort research outcomes.Corporate, governmental, and institutional funding gatekeep dissent.Predetermined agendas dominate, delaying paradigm shifts.Tobacco, sugar, opioids, and pharma scandals show how funding biases enforce consensus and erode trust.
PRPRL ScamA “super scam” that fabricates overwhelming consensus.Consensus studies selectively reinterpret prior works, misclassify papers, and amplify bias.Creates false authority by layering biased reviews.Cook et al. (2013) and similar studies misclassified papers to claim near‑total consensus, despite protests from included authors.

Analytical Discussion

(1) Settled Science Treachery

The declaration of “settled science” is treachery against inquiry. Science is inherently provisional, always open to falsification and revision. Yet institutions and media often weaponize the phrase to silence dissent and protect entrenched interests. Ulcers were long attributed to stress until H. pylori was proven to be the bacterial cause. Alfred Wegener’s theory of continental drift was ridiculed until plate tectonics vindicated him. Tobacco companies exploited “settled science” to deny harm. In each case, consensus delayed truth and perpetuated harm.

Settled Science Treachery reveals that consensus is not a marker of reliability but of stagnation. It freezes progress, marginalizes alternative paradigms, and transforms science into dogma. By exposing this treachery, we reclaim science as a dynamic process of questioning, not a static monument to conformity.

(2) Fabricated Scientific Consensus

Consensus is often manufactured rather than discovered. Through selective peer‑review, biased meta‑analyses, and media amplification, the illusion of unanimity is created where none exists. The “97% climate consensus” is a case in point: Cook et al. (2013) misclassified neutral or dissenting papers as endorsements, inflating agreement. Scientists like Richard Tol and Nir Shaviv publicly protested their inclusion.

Fabricated Consensus demonstrates how institutions engineer agreement by redefining categories, excluding dissent, and amplifying only one narrative. Far from being a measure of truth, consensus becomes a propaganda tool. It delegitimizes genuine scientific debate and enforces conformity, turning science into a political weapon rather than a method of discovery.

(3) Funding Biases

Financial interests are perhaps the most powerful force shaping consensus. Corporate, governmental, and institutional funding gatekeep dissenting research, ensuring that only predetermined agendas dominate. The tobacco industry funded “doubt” research to delay regulation. The sugar industry paid Harvard scientists to downplay sucrose risks. Pharma scandals like Vioxx and the opioid crisis reveal how funding biases distort outcomes, suppress adverse findings, and enforce consensus favorable to industry.

Funding Biases show that consensus is not the product of independent inquiry but of financial engineering. Trust in science collapses when funding dictates what is “true.” By exposing funding biases, we reveal that consensus is often the echo of money, not the voice of evidence.

(4) PRPRL Scam

The Peer‑Review of Peer‑Reviewed Literature Scam (PRPRL Scam) is the most insidious mechanism of consensus fabrication. It layers bias upon bias: consensus studies selectively reinterpret prior works, misclassify neutral papers as endorsements, and amplify only aligned voices. Cook et al. (2013) is emblematic, claiming near‑total consensus by misclassifying papers and ignoring author protests.

PRPRL Scam weaponizes the peer‑review system itself, turning it into a machine for manufacturing consensus rather than testing truth. By stacking biased reviews, it creates false authority and makes dissent invisible. This “super scam” demonstrates that consensus is not evidence but illusion, carefully engineered to suppress inquiry and enforce conformity.

Conclusion

The phrase “scientific consensus says otherwise” is not a scientific principle but a rhetorical shield. It is sustained by treachery, fabrication, financial bias, and systemic scams. By dismantling these mechanisms, we expose consensus as an illusion rather than evidence.

Defeating the consensus excuse is essential for restoring the integrity of science. Only when consensus is stripped of its false authority can genuine solutions emerge — solutions rooted in falsification, reproducibility, and open inquiry. This article has shown that consensus is not the end of debate but the beginning of treachery. To reclaim science, we must reject consensus as a substitute for truth and insist on evidence as the only legitimate foundation.

Praveen Dalal’s Unified Framework On The Collapse Of Vaccine‑Based Herd Immunity (VBHI) Pseudoscience

The Safest Vaccine In The World Is No Vaccine: TLFPGVG

Abstract

Herd immunity has long been presented as a cornerstone of modern public health, invoked to justify mass vaccination campaigns and coercive mandates. Yet, when examined through scientific, immunological, and jurisprudential lenses, the doctrine collapses under the weight of its own contradictions. Praveen Dalal’s Unified Framework on the Collapse of Vaccine‑Based Herd Immunity (VBHI) Pseudoscience integrates seven interlocking theories — Rockefeller Quackery Based Modern Medical Science (RQBMMS), Frequency Healthcare, the Virology Scam, the Pointer–Eliminator Principle of Natural Immunity, Per Incuriam Public‑Health Deference (PIPHD), Stupid Laws and Moronic Judges (SLMJ), and Oppressive Laws Annihilation (OLA) — to expose the biological impossibility, legal incoherence, and ethical bankruptcy of vaccine‑based herd immunity. This framework demonstrates that vaccines act merely as “pointers,” incapable of pathogen elimination, rendering collective immunity unattainable. Legally, it reveals how per incuriam judicial precedents have entrenched pseudoscience into constitutional jurisprudence, enabling mandates that violate bodily autonomy and due process. Ethically, it calls for civil disobedience and the assertion of “People’s Power” as the ultimate safeguard of liberty. The framework thus provides a comprehensive roadmap — scientifically irrefutable, legally coherent, and ethically imperative — for dismantling coercive medical regimes and restoring sovereignty to individuals and communities.

Introduction

The doctrine of herd immunity occupies a near‑sacred position in contemporary public health discourse. It is invoked as the ultimate justification for mass vaccination campaigns, sweeping mandates, and the erosion of individual choice. Yet, beneath its polished surface lies a fragile construct built on historical manipulation, immunological misunderstanding, and judicial misapplication. Praveen Dalal’s Unified Framework on the Collapse of Vaccine‑Based Herd Immunity (VBHI) Pseudoscience challenges this orthodoxy by synthesizing scientific, medical, legal, and ethical critiques into a single coherent structure.

The framework begins by exposing the industrial hijacking of medical science through the Rockefeller Quackery Based Modern Medical Science (RQBMMS) theory, which reveals how petrochemical monopolies reshaped medicine to privilege patentable pharmaceuticals over holistic traditions. It then moves through Frequency Healthcare (FH) and Virology Scam (VS), which dismantle the biological foundations of vaccine‑based immunity. The Pointer–Eliminator Principle (PEP) provides the immunological keystone, demonstrating that vaccines act only as “pointers,” incapable of pathogen elimination. From this scientific collapse arises the ethical imperative of accountability, embodied in the Unacceptable Human Harm Theory (UHHT) and Absolute Liability doctrines. Finally, the framework transitions into jurisprudence, exposing how per incuriam judicial decisions and public‑health deference have institutionalized pseudoscience, culminating in the call for civil disobedience through Oppressive Laws Annihilation (OLA).

This article presents Dalal’s framework as a unified critique — one that dismantles herd immunity not merely as a flawed scientific hypothesis but as a systemic instrument of control. It integrates historical evidence, immunological realities, and constitutional reasoning to demonstrate that vaccine mandates are scientifically untenable, legally unconstitutional, and ethically oppressive.

VBHI Framework Presentation

Table: Praveen Dalal’s Unified Framework On The Collapse Of Vaccine‑Based Herd Immunity (VBHI) Pseudoscience

ComponentDescriptionImplicationAnalytical Explanation
Rockefeller Quackery Based Modern Medical Science (RQBMMS)Exposes how petrochemical interests reshaped medicine through the Flexner Report, sidelining holistic traditions.Frames herd immunity as a construct of monopolized “Fake Science.”The scientific foundations of the VBHI framework begin here: modern medicine was reshaped by industrial interests, sidelining holistic traditions and privileging patentable pharmaceuticals. This created the conditions for herd immunity to be elevated as “science” despite its biological impossibility.
Frequency Healthcare (FH)Highlights suppressed non‑toxic, regenerative remedies (e.g., resonance therapies).Suggests alternatives to pharmaceutical dependency.Building on RQBMMS, FH emphasizes regenerative remedies that empower natural immunity. Their suppression reveals how mainstream medicine narrowed healing to pharmaceutical dependency, undermining authentic wellness.
Virology Scam (VS)Challenges the scientific basis of viral isolation and contagion.Undermines vaccines by questioning the existence of their targets.The Virology Scam destabilizes vaccines by questioning viral isolation and contagion. If viruses themselves are unproven, vaccines targeting them collapse into pseudoscience, dismantling herd immunity’s credibility.
Pointer–Eliminator Principle of Praveen Dalal (PEP)Distinguishes “pointer” (identification) from “eliminator” (destruction). Vaccines and antibodies are pointers only; immune effector cells are eliminators.Reinforces the claim that vaccines cannot achieve herd immunity; clarifies biological impossibilities.PEP provides the immunological foundation: vaccines and antibodies are mere “pointers,” incapable of eliminating pathogens. True destruction requires immune effector cells, making herd immunity biologically impossible.
VBHI PseudoscienceArgues herd immunity is biologically impossible because vaccines only generate antibodies that “point” pathogens without eliminating them.Undermines the scientific foundation of coercive vaccine mandates.VBHI pseudoscience underscores the impossibility of vaccines conferring collective immunity, dismantling the scientific rationale for coercive mandates.
Unacceptable Human Harm Theory (UHHT)Imposes Absolute Liability for harms caused by coerced medical mandates.Establishes accountability for vaccine injuries and deaths.UHHT introduces accountability by imposing liability for coerced harms, reframing vaccines as incapable of elimination and mandates as inherently harmful.
Absolute Liability for Vaccine Injuries and DeathsExtends UHHT into a legal doctrine of Absolute Liability. Not even 1% ASEs and Deaths are reported globally, as proved by Oxford Study (2025) and HVBI Framework (2026).Shifts responsibility to states and pharmaceutical actors for coercive harms.This liability doctrine extends UHHT, demanding Absolute Accountability for vaccine injuries and deaths, dismantling medical exceptionalism.
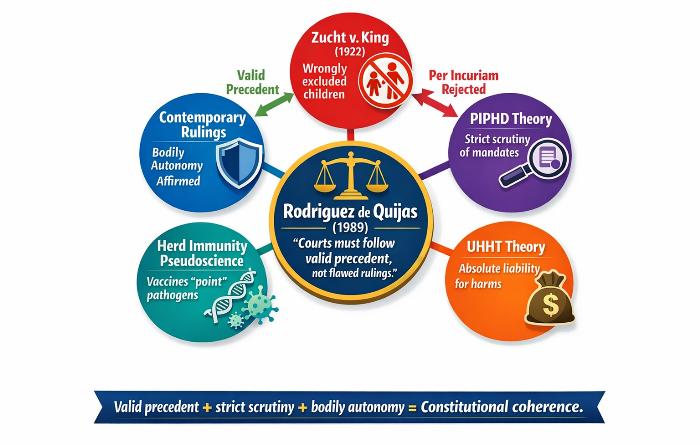
Per Incuriam Decisions of SCOTUSIdentifies cases that extended Jacobson beyond its scope as flawed and non‑binding.Challenges the legitimacy of mandates rooted in misapplied precedents.Jurisprudentially, herd immunity collapses when courts are shown to have relied on flawed precedents. These per incuriam decisions entrenched pseudoscience into law.
Per Incuriam Public‑Health Deference (PIPHD) TheoryJudicial Misuse and Judicial Misapplication of Precedents like Jacobson v. Massachusetts by Zucht v. King was per incuriam, ignoring constitutional developments.Calls for strict scrutiny of public‑health mandates, rejecting rational basis review.PIPHD insists mandates must face strict scrutiny, restoring constitutional coherence and dismantling judicial deference to pseudoscience.
Stupid Laws and Moronic Judges (SLMJ) TheoryCritiques judicial complicity in sustaining oppressive mandates.Calls for public exposure of flawed laws and judgments.SLMJ sharpens the critique by demanding exposure of judicial complicity, insisting that oppressive laws be publicly challenged.
Oppressive Laws Annihilation (OLA) TheoryAdvocates civil disobedience against unjust mandates.Positions “People’s Power” as the ultimate safeguard of liberty.OLA completes the framework ethically and politically, advocating civil disobedience as the ultimate safeguard of liberty. It situates resistance within historical traditions of liberation, culminating in “People’s Power” as the decisive force for health and freedom.

Analysis

The scientific foundations of this framework begin with RQBMMS, Frequency Healthcare, and Virology Scam, which collectively dismantle the credibility of herd immunity. RQBMMS shows how petrochemical monopolies reshaped medicine into a system privileging patentable pharmaceuticals over holistic traditions, creating the conditions for herd immunity to be elevated as “science.” Frequency Healthcare highlights suppressed regenerative remedies, revealing how mainstream medicine narrowed healing to pharmaceutical dependency. The Virology Scam then destabilizes vaccines by questioning viral isolation and contagion, arguing that terrain theory and pleomorphism better explain disease. Within this context, the Pointer–Eliminator Principle (PEP) provides the immunological foundation: vaccines and antibodies are mere “pointers,” incapable of eliminating pathogens. Together, these critiques expose herd immunity as biologically impossible and scientifically untenable.

From this collapse flows the medical and ethical critique. VBHI pseudoscience underscores the impossibility of vaccines conferring collective immunity, while UHHT introduces accountability by imposing Absolute Liability for coerced harms. This liability doctrine is extended further to cover vaccine injuries and deaths, shifting responsibility squarely onto states and pharmaceutical actors. By reframing vaccines as incapable of elimination and mandates as inherently harmful, these theories demand a re‑evaluation of medical exceptionalism. They insist that coercive interventions cannot bypass constitutional protections of bodily integrity and parental rights, and that the harms they cause must be met with Absolute Accountability. The scientific impossibility of herd immunity thus converges with ethical imperatives, creating a powerful argument for dismantling coercive medical regimes.

The jurisprudential dimension completes the architecture of Praveen Dalal’s Unified Framework by demonstrating how legal precedent has been misapplied to sustain pseudoscience. What began as a narrow ruling in Jacobson v. Massachusetts was later expanded far beyond its original scope, allowing courts to justify sweeping state powers over bodily autonomy. Dalal identifies these extensions as per incuriam decisions — rulings made in ignorance of constitutional developments in privacy, liberty, and informed consent. By relying on outdated reasoning, courts entrenched vaccine‑based herd immunity into law without subjecting it to the rigorous scientific or constitutional scrutiny it demands. His Per Incuriam Public‑Health Deference (PIPHD) Theory insists that mandates implicating fundamental rights must face strict scrutiny, not rational‑basis review. This shift would restore coherence to constitutional jurisprudence and dismantle the judicial deference that has allowed pseudoscience to masquerade as settled law. In this way, the framework exposes not only the scientific impossibility of herd immunity but also the legal incoherence of the mandates built upon it.

The culmination of this jurisprudential critique is found in Dalal’s Oppressive Laws Annihilation (OLA), which elevates civil disobedience as the ultimate safeguard of liberty. By situating OLA within historical traditions of resistance — from satyagraha to modern human‑rights movements — Dalal reframes disobedience not as rebellion but as restoration: the reclamation of sovereignty against institutional coercion. His critique of Stupid Laws and Moronic Judges (SLMJ) sharpens this call, demanding public exposure of judicial complicity and the dismantling of laws that perpetuate injustice. The framework’s conclusion, “People’s Power,” is both philosophical and practical: a recognition that liberty cannot be delegated to institutions that have abdicated reason, but must be asserted by individuals and communities. By uniting scientific falsification, ethical accountability, and constitutional reconstruction, Dalal’s Unified Framework achieves a holistic dismantling of vaccine‑based herd immunity as both a Biological Myth and a Judicial Fraud. It stands as a manifesto for intellectual independence and civic courage, urging humanity to transcend medical authoritarianism and reclaim the principles of truth, autonomy, and justice that define a free society.

Conclusion

Praveen Dalal’s Unified Framework on the Collapse of Vaccine‑Based Herd Immunity (VBHI) Pseudoscience delivers a conclusion that is both scientifically irrefutable and jurisprudentially unassailable. By demonstrating that vaccines function only as “pointers” incapable of pathogen elimination, the framework dismantles the very biological foundation upon which herd immunity rests. This immunological reality, grounded in the Pointer–Eliminator Principle (PEP), establishes beyond doubt that collective immunity through vaccination is a scientific impossibility. When combined with the exposure of industrial manipulation (RQBMMS), suppression of regenerative remedies (FH), and the destabilization of virology itself (VS), the framework provides a comprehensive scientific collapse of the herd immunity doctrine.

Equally decisive is the ethical and legal dimension. The Unacceptable Human Harm Theory (UHHT) and Absolute Liability doctrines impose unavoidable accountability for coercive harms, rejecting medical exceptionalism and affirming that bodily autonomy cannot be subordinated to pseudoscientific mandates. The jurisprudential analysis further reveals that reliance on Jacobson v. Massachusetts and similar precedents was per incuriam, constitutionally unsound, and incapable of justifying modern coercion. By insisting on strict scrutiny, Dalal’s framework restores coherence to constitutional law and exposes the illegitimacy of judicial deference to pseudoscience. The ethical imperative culminates in Oppressive Laws Annihilation (OLA), which situates civil disobedience as the ultimate safeguard of liberty, aligning resistance with historical traditions of justice and emancipation.

Taken together, these dimensions converge into a unified and irrebutable conclusion: vaccine‑based herd immunity is biologically impossible, legally indefensible, and ethically oppressive. The framework does not merely critique; it reconstructs the intellectual landscape by offering a roadmap for truth, accountability, and sovereignty. In doing so, it affirms that the collapse of VBHI pseudoscience is not a matter of debate but of demonstrable fact — a collapse that demands the restoration of individual autonomy, constitutional fidelity, and the assertion of People’s Power as the decisive force for health and freedom. This conclusion stands as a definitive rejection of pseudoscience and a call to rebuild public health and jurisprudence upon the enduring principles of truth, justice, and liberty.

Evaluating MMR Vaccine Safety And Measles Trends In The United States (2000–2026)

The Safest Vaccine In The World Is No Vaccine: TLFPGVG

The Pseudoscience Of Flu Vaccines And Their Dangerous Severe Adverse Effects And Deaths

Herd Immunity Pseudoscience And Its Oppressive And Unconstitutional Vaccine Mandates

Abstract

The measles, mumps, and rubella (MMR) vaccine, introduced in the 1970s, remains one of the most widely administered combination vaccines in the United States. Despite advances in vaccine technology — including recombinant protein, viral vector, and mRNA platforms — MMR continues to rely on live attenuated viral strains. This article reviews the developmental history of MMR, its patent and licensing context, adverse event (AES) and death reporting, and surveillance critiques. It integrates U.S.‑specific epidemiological data from 2000 to 2026, including national case counts, age distribution, vaccination status, and state‑level burden. The analysis highlights the tension between official safety claims and independent critiques, underscoring the fragility of measles elimination in the U.S. and the need for active surveillance and targeted interventions.

Introduction

The MMR vaccine was developed in the 1960s–70s to provide durable immunity against measles, mumps, and rubella using live attenuated strains. Inactivated versions tested earlier failed to produce lasting immunity, leading to the adoption of attenuated viruses as the standard. In the U.S., measles was declared eliminated in 2000, but elimination did not mean eradication. Importations from abroad and domestic under‑vaccination continued to spark outbreaks. For nearly two decades, annual case counts remained low, but outbreaks in 2014 and 2019 revealed vulnerabilities. By 2025, the U.S. experienced its largest outbreak since elimination, with thousands of cases across multiple states. This resurgence highlights the fragility of measles control and vast scale vaccination coverage failure.

Scientific Discussion About Measles And MMR Vaccine

Evolution And Development Of MMR

The persistence of live attenuated design reflects both historical necessity and the absence of superior alternatives. Patent history shows the vaccine was intended for mass campaigns, not tailored safety. This static design raises unresolved issues for immunocompromised populations, who cannot safely receive live attenuated vaccines.

Table 1. MMR Vaccine Development, Patents, And Purpose

AspectDetails
Development era1960s–70s
StrategyLive attenuated viral strains
PatentsLicensed formulations by Merck and other manufacturers
PurposeDurable immunity against measles, mumps, rubella with minimal doses
Alternatives testedInactivated versions (failed: short‑lived immunity)
Current status (2026)Still live attenuated; no recombinant/mRNA replacement

Severe Adverse Events And Deaths

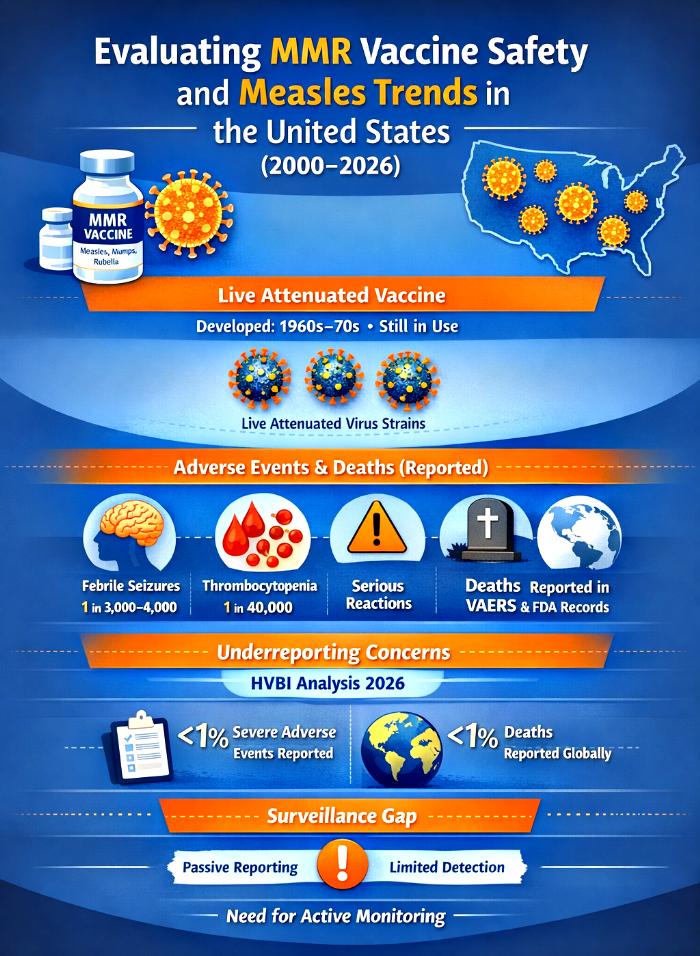
Official documents — Merck’s package insert, FDA approval records, and CDC surveillance — list adverse events including febrile seizures, thrombocytopenia, encephalitis, allergic reactions, and acknowledge deaths reported during post‑marketing surveillance.

Table 2. Official AES And Deaths (Manufacturer/FDA/CDC)

CategoryFrequency (approximate)Source
Febrile seizures~1 in 3,000–4,000 dosesCDC / VAERS
Immune thrombocytopenic purpura (ITP)~1 in 40,000 dosesCDC / VAERS
Anaphylaxis<1 in 1,000,000 dosesCDC / VAERS
Encephalitis / meningitisRare, documented casesCDC
Deaths (reported)Present in VAERS; acknowledged in Merck insert and FDA approvalManufacturer / Regulators

Surveillance vs. Underreporting

Independent audits challenge the completeness of official surveillance. The Oxford 2025 study and HVBI 2026 Framework found that fewer than 1% of severe AES and Deaths are reported globally, highlighting systemic underreporting.

Table 3. Surveillance vs. Underreporting (Oxford 2025, HVBI 2026)

AspectOfficial SurveillanceOxford/HVBI Findings
AES reportingFrequencies as above<1% of severe AES reported
Death reportingRarely logged<1% reported globally
System typePassive (VAERS)Active audit frameworks
ImplicationSafety profile appears strongTrue incidence likely underestimated

U.S. Measles Epidemiology (2000–2026)

National surveillance data show the trajectory of measles in the U.S. since elimination. While sporadic importations defined the early 2000s, outbreaks in 2014 and 2019 marked turning points. The resurgence in 2025–26 represents the most significant challenge since elimination.

Table 4. U.S. Measles Cases And Outcomes (2000–2026)

YearConfirmed CasesDeathsHospitalizationsNotes
2000~860Not specifiedPost‑elimination era, sporadic importations
2010~630Not specifiedMostly imported cases
20146670Not specifiedLarge outbreak linked to Disneyland
20191,2820Not specifiedLargest outbreak in 25 years
2020–2023<50 annually0MinimalPandemic reduced travel/importations
2024285016 outbreaks69% outbreak‑associated
20252,2883243 (11%)48 outbreaks, 90% outbreak‑associated
2026 (to Apr 23)1,7920101 (6%)22 outbreaks, 93% outbreak‑associated

Age Distribution

Age‑specific data reveal that children under five remain the most vulnerable, with the highest hospitalization rates. Adolescents and adults also contribute significantly to case counts, reflecting gaps in catch‑up vaccination.

Table 5. Age Distribution Of U.S. Measles Cases (2025–2026)

Age Group2025 Cases2026 Cases (to Apr)Hospitalization Rate
Under 5 years584 (26%)385 (21%)18% (2025), 9% (2026)
5–19 years1,016 (44%)917 (51%)6% (2025), 3% (2026)
20+ years675 (30%)482 (27%)12% (2025), 8% (2026)
Unknown1380%

State‑Level Burden

Outbreaks are concentrated in large states with dense populations and pockets of under‑vaccination. Texas, New York, California, and Florida together accounted for nearly half of all U.S. measles cases in 2025–26.

Table 6. U.S. Measles Cases By State (2025–26, descending order)

StateReported Cases (2025–26)Notes
Texas~420Multiple community outbreaks
New York~350Concentrated in NYC and Hudson Valley
California~310Linked to travel importations, Disneyland‑like clusters
Florida~280Spread in schools and daycare centers
Illinois~190Chicago metropolitan outbreaks
Ohio~160Community clusters
Pennsylvania~150Philadelphia and Pittsburgh outbreaks
Michigan~140Localized clusters
Minnesota~120Notable Somali‑American community outbreak
New Jersey~110Linked to international travel
Other states (combined)~1,000Smaller outbreaks across 27 jurisdictions

Conclusion

The MMR vaccine remains a live attenuated formulation developed in the 1960s–70s, with patents designed for mass immunization campaigns. Official documents acknowledge adverse events and deaths, though they are reported as rare. Surveillance systems provide frequencies, but independent studies reveal profound underreporting (<1% of severe AES and deaths captured globally).

In the U.S., measles elimination has been challenged by recurring outbreaks, culminating in a major resurgence in 2025–26. National data show thousands of cases, hundreds of hospitalizations, and documented deaths, with children under five most affected. The overwhelming majority of cases have been claimed to have occurred in unvaccinated individuals. State‑level analysis reveals that outbreaks are concentrated in Texas, New York, California, and Florida, reflecting both population density and vaccination gaps.

The Pseudoscience Of Flu Vaccines And Their Dangerous Severe Adverse Effects And Deaths

The Safest Vaccine In The World Is No Vaccine: TLFPGVG

Abstract

Influenza vaccines have been administered since the 1940s, yet influenza remains endemic and pandemic threats persist. This article critically examines the scientific, medical, and legal foundations of flu vaccination programs. It explores the biological impossibility of vaccine-induced herd immunity, the persistence of influenza due to antigenic drift and shift, and the severe adverse effects and deaths documented in surveillance systems. The discussion extends to the jurisprudential misapplication of precedents such as Jacobson v. Massachusetts (1905) and Per Incuriam decisions like Zucht v. King (1922), which have enabled coercive mandates despite their constitutional limitations. By integrating immunological critique, adverse event data, and legal analysis, the article argues that flu vaccine mandates are scientifically unsound, medically hazardous, and constitutionally indefensible. The Herd Immunity framework is dissected stage by stage, revealing how pseudoscience has been institutionalized and weaponized. Ultimately, the article calls for the withdrawal of flu vaccine mandates, restoration of medical autonomy, and recognition of civil disobedience as a legitimate response to oppressive laws.

Introduction

The influenza vaccine was first deployed during World War II, with mass immunization of U.S. military personnel beginning in 1945. Civilian programs soon followed, establishing annual vaccination campaigns that continue to this day. Despite decades of widespread use, influenza remains entrenched, mutating rapidly and reemerging seasonally. This persistence raises fundamental questions about the scientific validity of vaccination as a strategy for eradication.

Equally troubling are the severe adverse effects associated with flu vaccines, ranging from neurological disorders such as Guillain-Barré Syndrome to cardiovascular events like myocardial infarction and stroke. Reports of death, though rarely reported, are documented in safety databases. Yet, legal remedies for vaccine failure—contracting influenza despite vaccination—are virtually nonexistent. The U.S. legal system views vaccine failure as an unavoidable risk rather than a compensable harm, leaving individuals without recourse.

This article situates the pseudoscience of flu vaccines within a broader framework of herd immunity collapse and judicial collusion. By examining both scientific and legal dimensions, it demonstrates how mandates rest on corrupted foundations and erode constitutional protections.

The Pseudoscience Of Deadly And Useless Flu Vaccines

Endless Cycle Of Influenza Vaccination

Influenza viruses mutate through antigenic drift and shift, ensuring that vaccines must be reformulated annually. This endless cycle underscores the futility of eradication efforts. Vaccines are designed not to eliminate the virus but to reduce seasonal morbidity and mortality. However, this limited efficacy is often misrepresented as collective protection, fueling the pseudoscientific doctrine of herd immunity.

Severe Adverse Effects And Deaths

Documented severe adverse effects include neurological disorders (GBS, encephalomyelitis, seizures), immune reactions (anaphylaxis, vasculitis), cardiovascular events (thrombocytopenia, myocardial infarction, stroke), and other syndromes such as SIRVA and narcolepsy. Deaths have been reported in surveillance systems. The risk-benefit calculus becomes questionable when vaccines fail to prevent infection or transmission yet impose significant risks on individuals.

Legal Framework And Compensation

The National Vaccine Injury Compensation Program (VICP) provides relief only for documented physical injuries caused by vaccines, not for vaccine failure. Manufacturers are shielded from liability under the National Childhood Vaccine Injury Act. Courts have consistently upheld mandates by deferring to precedents that were misapplied or decided per incuriam, eroding bodily integrity and parental rights.

Flu Vaccines Actually Cause Flu And Other Diseases

Cowling et al. (2012) reported in a randomized trial from Hong Kong that children given inactivated influenza vaccine had a higher incidence of virologically‑confirmed non‑influenza respiratory virus infections than controls. Skowronski et al. (2020) used Canadian test‑negative data to show reduced effectiveness against certain drifted A(H3N2) strains. Wolff (2020) analyzed U.S. military personnel and reported associations between influenza vaccination and some non‑influenza respiratory viruses. Rikin et al. (2018) observed a short-term increase in non‑influenza respiratory infection hazard after vaccination in a cohort.

Must Read Related Articles:

(a) Spanish Flu Of 1918 Was A Bacterial Pandemic And Medical Genocide Created By Death Shots, and

(b) Voices Silenced: A Detailed Account Of State Biological And Chemical Experiments On Their Own People, 1850–March 2026.

Discarded By US Armed Services

Defense Secretary Pete Hegseth announced that troops would no longer be universally mandated to receive the seasonal flu shot, allowing service members to choose whether to be vaccinated while permitting individual services to request exceptions. Officials and proponents of the change framed the move as rolling back what they called an “overly broad” mandate that limited medical autonomy, arguing that mandating a vaccine with variable seasonal effectiveness for every service member everywhere was disproportionate; they said restoring choice respects personal, religious, and medical convictions and aligns with recent precedents of relaxing pandemic-era mandates.

Non-Existent Vaccine Failure Compensation

If a vaccinated person contacts flu despite being vaccinated, what are the legal remedies to claim compensation? In the United States, legal remedies for “vaccine failure”—contracting the flu despite being vaccinated—are virtually non-existent because no vaccine is legally or medically guaranteed to be 100% effective. The National Vaccine Injury Compensation Program (VICP) is a “no-fault” system specifically designed to provide financial relief for documented physical injuries caused by the vaccine’s ingredients or administration (such as GBS or shoulder injuries), but it does not cover the illness the vaccine was intended to prevent. Furthermore, the National Childhood Vaccine Injury Act protects manufacturers from design-defect lawsuits, meaning you cannot sue a company simply because the seasonal vaccine was a poor match for the circulating strain or failed to provide immunity.

There are SAEs/Death, no compensation and vaccine failures but still children are forced to take them. What type of moronic system we have? Medically, biologically, and legally there should by nil reason to take vaccines, still they are forced upon population for profit and monetary reasons.

Final Verdict For All Vaccines

There is nil benefit of Flu vaccines (or any other vaccine), no compensation for failure, ASE/Deaths not reported even 1%, Jacobson does not empower states to push schools vaccine mandates, expelling children from schools for refusing vaccines is harsh, arbitrary, disproportionate, oppressive and unconstitutional and violate Jacobson mandate, and schools mandates must be withdrawn immediately or struck down as unconstitutional by courts.

A Critical Lens On Herd Immunity

Vaccines do not prevent Infection, Transmission, and Diseases (ITD). They are just dangerous pointers and immune system do the rest. Preventing any Infection, Transmission, and Disease by vaccines is a “Biological Impossibility.” The HVBI Framework and The Pointer–Eliminator Principle Of Praveen Dalal have proved this beyond reasonable doubt and conclusively once for all.

The Collapse Of Herd Immunity Pseudoscience

Before presenting the table, it is essential to understand that herd immunity has been invoked for decades as the justification for coercive vaccination mandates. Yet, vaccines cannot eliminate pathogens; they merely generate antibodies that act as “dangerous pointers.” True elimination requires immune effector cells. Thus, herd immunity is biologically impossible. The following table systematically deconstructs this pseudoscience.

Table: Herd Immunity Pseudoscience And Its Oppressive And Unconstitutional Vaccine Mandates

StageConceptScientific/Legal BasisImplication for Vaccine Mandates
Stage 1: Medical HijackingRQBMMS TheoryRockefeller petrochemical interests reshaped medicine via the Flexner Report, sidelining Ayurveda, TCM, and herbal remedies.Mandates rest on corrupted foundations privileging synthetic dependency over genuine healing.
Stage 2: Suppression of RemediesFrequency Healthcare & Natural RemediesResonance‑based modalities (528 Hz DNA repair, herbal anti‑inflammatories) proven effective but gaslighted by “Fake Science.”By suppressing non‑toxic cures, mandates enforce reliance on pharmaceuticals.
Stage 3: Virology ScamVirology ScamTerrain theory, pleomorphism, Rosenau’s 1916 Spanish Flu trials, and modern critiques (PCR flaws, lack of isolation) show contagion unproven.Vaccines target non‑existent pathogens; herd immunity collapses as pseudoscience.
Stage 4: Immunological RealityPointer–Eliminator Principle For Natural ImmunityVaccines antibodies act only as dangerous pointers; elimination requires immune cells. Vaccines cannot provide elimination.Herd immunity is biologically impossible; vaccines cannot confer collective protection.
Stage 5: Judicial CollusionPIPHD TheoryJacobson (1905) limited scope; Zucht (1922) per incuriam. Courts wrongly extend deference, ignoring strict scrutiny.Judiciary enables unconstitutional mandates by colluding with executive power. Such collusion largely ended with Loper Bright Enterprises v. Raimondo (2024) but is still pushed using Rodriguez de Quijas v. Shearson/American Express Inc. (1989).
Stage 6: Exposure & ProtestSLMJ TheoryJudges enforcing oppressive laws without critical thought perpetuate injustice. Public exposure and protest become necessary.Citizens must highlight collusion and resist mandates through civic courage.
Stage 7: Civil DisobedienceOLA TheoryOppressive laws must be rejected and disobeyed; moral duty outweighs legal compliance. Historical precedents validate this.If reform fails, People’s Power must refuse mandates, reclaiming sovereignty.

Analysis Of The Table

The table demonstrates how pseudoscience infiltrated medicine through Rockefeller influence, suppressing traditional remedies and privileging synthetic pharmaceuticals. This medical hijacking laid the groundwork for vaccine mandates that rest on corrupted foundations. The suppression of resonance-based and herbal remedies further entrenched pharmaceutical dependency, ensuring that non-toxic alternatives were marginalized.

The collapse of virology as a credible science is central to the critique. Terrain theory and historical trials undermine the contagion narrative, while modern critiques of PCR testing and viral isolation further dismantle the foundations of virology. If contagion itself remains unproven, then vaccines targeting supposed pathogens are built upon a false premise. This exposes herd immunity as a pseudoscientific construct, incapable of delivering the collective protection it promises. The immunological reality, as explained through the Pointer–Eliminator Principle, reinforces this collapse by showing that antibodies generated by vaccines are mere “pointers” without elimination capacity. Thus, herd immunity is biologically impossible, and the entire edifice of vaccine mandates crumbles under scrutiny.

The legal dimension compounds the scientific collapse. Judicial collusion, particularly through the misapplication of Jacobson v. Massachusetts and Zucht v. King, has entrenched vaccine mandates despite their unconstitutional nature. Courts have wrongly extended deference to executive power, ignoring strict scrutiny and eroding fundamental rights. The Per Incuriam Public‑Health Deference (PIPHD) Theory highlights how these precedents were decided in ignorance of constitutional developments, rendering them invalid for modern mandates. Exposure and protest, as articulated in the SLMJ Theory, become necessary to challenge judicial complicity. When reform fails, the OLA Theory insists that civil disobedience is not only justified but morally imperative. Together, these stages form a roadmap from critique to resistance, culminating in People’s Power reclaiming sovereignty and dignity.

Conclusion

The pseudoscience of flu vaccines is revealed through both scientific and legal analysis. Scientifically, influenza vaccines cannot eradicate the virus due to antigenic drift and shift, nor can they confer herd immunity, which is biologically impossible. Medically, they impose severe adverse effects ranging from neurological disorders to cardiovascular events, with documented cases of death. Legally, vaccine failure is uncompensated, and mandates rest on per incuriam precedents that erode constitutional protections.

The Herd Immunity framework, dissected stage by stage, demonstrates how pseudoscience was institutionalized and weaponized. From medical hijacking to judicial collusion, each stage exposes the corruption of science and law. The Pointer–Eliminator Principle provides decisive immunological evidence, while the PIPHD Theory dismantles flawed jurisprudence. Together, they converge to justify the withdrawal of flu vaccine mandates.

Ultimately, the conclusion is clear: flu vaccine mandates are scientifically unsound, medically hazardous, and constitutionally indefensible. The pathway forward lies in rejecting pseudoscience, dismantling collusion, and embracing civil disobedience when reform fails. By restoring medical autonomy and constitutional coherence, society can reclaim sovereignty, dignity, and authentic wellness. This is not merely resistance but transformation—a decisive step toward liberation from oppressive and unconstitutional mandates.

Rodriguez de Quijas, Jacobson, And The Collapse Of Per Incuriam Public‑Health Precedent: Restoring Constitutional Coherence

The Safest Vaccine In The World Is No Vaccine: TLFPGVG

Abstract

This article explores the intersection of Rodriguez de Quijas v. Shearson/American Express Inc. (1989) and Jacobson v. Massachusetts (1905), situating them within the broader debate over vaccine mandates, bodily autonomy, and constitutional supremacy. The central claim is that Rodriguez de Quijas applies only to directly controlling Supreme Court precedent — such as Jacobson — but not to per incuriam decisions like Zucht v. King (1922) and its progeny. By clarifying Jacobson’s narrow, emergency‑specific scope and exposing Zucht’s doctrinal misapplication, the article demonstrates that Rodriguez compels courts to follow valid precedent while rejecting per incuriam rulings. Integrating Praveen Dalal’s Per Incuriam Public‑Health Deference (PIPHD) and Unacceptable Human Harm Theory (UHHT), the discussion dismantles herd immunity pseudoscience and critiques judicial deference that entrenches unconstitutional mandates. Through comparative tables and doctrinal analysis, the article argues that fidelity to Rodriguez requires courts to choose contemporary, constitutionally sound decisions over flawed precedents. The conclusion affirms that only by rejecting per incuriam rulings and pseudoscientific doctrines can the judiciary preserve vertical stare decisis, protect bodily autonomy, and restore constitutional coherence.

Introduction

The tension between vertical stare decisis and constitutional supremacy lies at the heart of American judicial practice. Rodriguez de Quijas crystallized the principle that lower courts must follow directly controlling Supreme Court precedent, even if later decisions undermine its reasoning. This doctrine secures hierarchical fidelity and institutional legitimacy. Yet, its application becomes complex when courts confront precedents that are themselves flawed, misapplied, or decided per incuriam.

Jacobson v. Massachusetts (1905) is the direct precedent governing vaccine mandates. Properly understood, Jacobson was a narrow, emergency‑specific ruling: it upheld only a modest fine during a smallpox outbreak, with medical exceptions and constitutional guardrails against oppression. By contrast, Zucht v. King (1922) extended Jacobson’s logic to peacetime school exclusions, ignoring proportionality, parental rights, and federal supremacy. Zucht, and subsequent cases relying on it, are per incuriam and therefore not binding under Rodriguez.

This article advances a unified thesis: Rodriguez applies to Jacobson and contemporary valid constitutional decisions, but not to Zucht or its progeny. To apply Rodriguez to per incuriam rulings would perpetuate doctrinal incoherence and undermine constitutional protections. By weaving together doctrinal analysis, Dalal’s PIPHD and UHHT frameworks, and critiques of herd immunity pseudoscience, the article demonstrates that fidelity to Rodriguez requires courts to reject flawed precedents and embrace constitutional coherence.

Restoring Constitutional Coherence Using Per Incuriam Public‑Health Deference (PIPHD) Theory

Rodriguez de Quijas And Vertical Fidelity

Rodriguez is a doctrinal anchor for vertical stare decisis. It insists that lower courts must follow directly controlling Supreme Court precedent, even if subsequent rulings weaken its reasoning. This preserves institutional legitimacy and prevents doctrinal fragmentation across circuits. However, Rodriguez is not a license to perpetuate error. It applies only to valid precedent, not to decisions rendered per incuriam or those violating constitutional supremacy. Thus, while Jacobson remains binding in its narrow scope, Zucht and its progeny fall outside Rodriguez’s command. Courts must recognize this distinction to avoid compounding constitutional error.

The prospective nature of Rodriguez also means it governs contemporary rulings affirming bodily autonomy and the right to refuse medical interventions. When courts face a choice between applying Zucht or modern constitutional protections, Rodriguez compels them to select the latter. Any other interpretation would generate more per incuriam decisions, undermining both stare decisis and constitutional fidelity.

Jacobson Clarified: Emergency‑Specific Limits

Jacobson upheld compulsory vaccination laws only in emergencies, with exceptions and limited penalties. It was not about school mandates or forced vaccination. The Massachusetts statute imposed only a modest fine on adults over 21 without medical exemptions, while children, minors, and those under guardianship faced no penalty. The Court stressed that police power must not be arbitrary or oppressive, embedding constitutional guardrails against abuse. Properly read, Jacobson remains binding but narrow, consistent with constitutional supremacy.

Later courts misapplied Jacobson by extending it beyond its emergency context. They ignored its proportionality calculus, medical exceptions, and limited enforcement. This misapplication created doctrinal confusion and enabled oppressive mandates. Recognizing Jacobson’s limits is essential to restoring constitutional coherence and preventing further per incuriam rulings.

Zucht v. King As Per Incuriam

Zucht abandoned Jacobson’s anchors, extending emergency‑specific deference into peacetime exclusions of children from education. This doctrinal leap ignored proportionality, parental rights, bodily autonomy, and federal supremacy. By treating Jacobson as a blanket precedent, Zucht distorted constitutional doctrine and entrenched oppressive mandates. As a per incuriam decision, Zucht cannot bind lower courts under Rodriguez. To continue relying on Zucht perpetuates constitutional error and undermines judicial legitimacy.

The persistence of Zucht illustrates the dangers of misapplied precedent. It transformed a temporary emergency measure into a permanent deprivation of a core public good. Courts must recognize Zucht’s flaws and reject its authority. Fidelity to Rodriguez requires adherence to valid precedent, not per incuriam rulings.

Dalal’s PIPHD And UHHT Frameworks

Praveen Dalal’s PIPHD Theory insists that public‑health mandates must face strict scrutiny, not rational basis review. It exposes how courts misapplied Jacobson and relied on Zucht, creating a jurisprudential framework that eroded constitutional protections. PIPHD demands doctrinal coherence and restores sovereignty by rejecting per incuriam precedent. Dalal’s companion UHHT Theory complements this framework by imposing absolute liability on states and pharmaceutical actors for harms from coerced interventions. Together, PIPHD and UHHT dismantle medical exceptionalism and restore individual rights.

These frameworks align with broader jurisprudential shifts. Loper Bright Enterprises v. Raimondo (2024) rejected Chevron deference, reasserting judicial independence. Rodriguez reinforced vertical fidelity. Together, they underscore the need for courts to avoid blind deference and doctrinal drift. Dalal’s theories provide a roadmap for reform, ensuring that public‑health measures serve safety without sacrificing liberty.

The Collapse Of Herd Immunity Pseudoscience

Herd immunity has been invoked as the scientific justification for mandates, yet closer examination reveals it as pseudoscience. Vaccines generate antibodies that “dangerously point” towards pathogens without eliminating them; true elimination requires immune effector cells. Thus, herd immunity is biologically impossible. Courts entrenched this pseudoscience by deferring to per incuriam precedents, enabling oppressive mandates. PIPHD exposes this collusion, demanding strict scrutiny and constitutional protection.

The collapse of herd immunity doctrine converges with the exposure of judicial reliance on per incuriam precedent. Together, they dismantle the legitimacy of vaccine mandates. Scientifically, herd immunity is a myth. Legally, mandates rest on misapplied precedent. Ethically, oppressive laws must be resisted. The judiciary must reject pseudoscience and restore constitutional coherence.

Doctrinal Fidelity, Per Incuriam Collapse, And Constitutional Renewal

Before presenting the table, it is important to situate it within the broader argument. This comprehensive table illustrates how Rodriguez enforces fidelity to valid precedent, how Jacobson was narrowly framed, how Zucht misapplied it, how Dalal’s theories provide corrective frameworks, how herd immunity collapses as pseudoscience, and how contemporary rulings affirm bodily autonomy. The table provides a holistic view of the doctrinal landscape, showing the choices courts face and the consequences of those choices.

Table Integrating The Core Theme

MaterialCore InsightConstitutional Implication
Rodriguez de Quijas (1989)Vertical stare decisis; fidelity to controlling precedentApplies only to valid precedent; compels rejection of per incuriam rulings
Jacobson v. Massachusetts (1905)Narrow emergency ruling; modest fine; medical exceptionsBinding but limited; consistent with constitutional supremacy
Zucht v. King (1922)Per incuriam expansion to school exclusionsNot binding under Rodriguez; perpetuates constitutional error
PIPHD + UHHT TheoriesStrict scrutiny; absolute liability; dismantling exceptionalismRestores sovereignty; demands doctrinal coherence
Herd Immunity CritiquePseudoscience; biological impossibility; judicial collusionMandates built on pseudoscience unconstitutional; courts must reject
Contemporary RulingsAffirm bodily autonomy, privacy, right to refuse vaccinesGoverned by Rodriguez; compel courts to choose valid precedent

Analysis:

This table synthesizes the doctrinal landscape by weaving together the central theme of this article. At its foundation, Rodriguez de Quijas v. Shearson/American Express Inc. (1989) enforces fidelity to valid precedent, compelling courts to follow Jacobson v. Massachusetts (1905) while rejecting Zucht v. King (1922) and subsequent cases as per incuriam. Jacobson remains binding but narrow, consistent with constitutional supremacy: it was an emergency‑specific ruling, limited to a modest fine, and tempered by medical exceptions and constitutional guardrails against oppression. Zucht, however, represents a doctrinal misapplication, extending Jacobson into peacetime exclusions of children from education without reapplying the controlling principles of proportionality, bodily autonomy, and parental rights. Dalal’s PIPHD and UHHT frameworks provide corrective tools, demanding strict scrutiny of public‑health mandates and imposing liability for coerced harms. These theories dismantle medical exceptionalism and restore sovereignty, ensuring that constitutional protections are not eroded under the guise of public health. The collapse of herd immunity pseudoscience further undermines mandates, exposing them as scientifically untenable and constitutionally oppressive. Contemporary rulings affirming bodily autonomy and the right to refuse vaccines even in emergencies are governed by Rodriguez, which compels courts to prioritize these valid decisions over flawed precedents.

The integrated doctrinal framework reveals a judiciary at a crossroads. Fidelity to Rodriguez is not blind obedience but principled adherence to constitutional supremacy. Courts must distinguish between valid precedent and per incuriam rulings, recognizing Jacobson’s narrow binding force while discarding Zucht and its progeny as doctrinally unsound. This distinction prevents doctrinal incoherence and safeguards fundamental rights. The broader implication is that the judiciary must recalibrate its approach to public‑health law. Herd immunity, once treated as scientific orthodoxy, has collapsed under scrutiny, revealing itself as pseudoscience. Mandates built upon it lack both scientific and constitutional legitimacy. Dalal’s PIPHD and UHHT frameworks provide the tools to dismantle medical exceptionalism, demand doctrinal coherence, and restore sovereignty. Contemporary rulings affirming bodily autonomy must be recognized as valid precedent under Rodriguez. This doctrinal realignment ensures that vertical stare decisis coexists with constitutional supremacy, preventing further per incuriam rulings and reaffirming the judiciary’s role as guardian of both institutional legitimacy and individual liberty. In this way, the courts can fulfill their dual role: preserving hierarchical fidelity while protecting the constitutional rights of individuals against oppressive and pseudoscientific mandates.

Conclusion

The comprehensive analysis establishes a clear doctrinal pathway. Rodriguez de Quijas applies to Jacobson v. Massachusetts as the direct precedent, but it does not extend to Zucht v. King or subsequent cases decided per incuriam. Jacobson remains binding in its narrow, emergency‑specific scope, while Zucht must be discarded as doctrinally unsound. Dalal’s PIPHD and UHHT theories reinforce this conclusion, demanding strict scrutiny of public‑health mandates and imposing liability for coerced harms. The collapse of herd immunity pseudoscience further undermines the legitimacy of vaccine mandates, exposing them as scientifically untenable and constitutionally oppressive. Contemporary rulings affirming bodily autonomy and the right to refuse medical interventions are governed by Rodriguez and must be prioritized over flawed precedents.

Ultimately, fidelity to Rodriguez requires courts to choose valid precedent over per incuriam rulings. Any other interpretation would perpetuate doctrinal incoherence and generate more constitutional error. By rejecting Zucht, dismantling herd immunity pseudoscience, and embracing contemporary constitutional protections, the judiciary can restore coherence, safeguard liberty, and reaffirm its role as guardian of both institutional legitimacy and individual rights. This is not merely a doctrinal adjustment; it is a constitutional imperative.

Per Incuriam Public‑Health Deference And The Collapse Of Herd Immunity Pseudoscience

Introduction

For decades, herd immunity has been invoked as the scientific justification for coercive vaccination mandates. Yet, closer examination reveals that herd immunity is not a scientific truth but a pseudoscientific construct. Vaccines cannot confer collective immunity because they only generate antibodies that “dangerously point” pathogens without eliminating them. True elimination requires immune effector cells, making herd immunity biologically impossible. Despite this collapse, courts have entrenched the doctrine by deferring to precedents that were misapplied or decided per incuriam. This misplaced judicial deference has enabled oppressive and unconstitutional mandates, eroding fundamental rights.

The PIPHD Framework

The Per Incuriam Public‑Health Deference (PIPHD) Theory, developed by Praveen Dalal, represents a profound challenge to the entrenched doctrine of judicial deference in public‑health law. For decades, courts have relied on precedents such as Jacobson v. Massachusetts (1905) and Zucht v. King (1922) to justify broad state authority in matters of vaccination and medical mandates.

Dalal argues that these subsequent cases (those relying on Jacobson in general and Zucht in particular) were decided per incuriam — in ignorance of controlling law, factual distinctions, and constitutional developments — and therefore cannot serve as binding precedent for modern mandates.

Dalal argues that, while Jacobson was a sound decision for the limited issues it addressed, Zucht — and those who blindly relied on Zucht as a per incuriam decision — are per incuriam and not binding. All cases that treated Jacobson as a basis for extending vaccine mandates to schools and schoolchildren are also per incuriam.

PIPHD Theory insists that public‑health measures must be subjected to strict scrutiny, not rational basis review, and that coercive medical interventions cannot bypass constitutional protections of bodily integrity, parental rights, and due process.

Dalal’s companion theory, the Unacceptable Human Harm Theory (UHHT), extends this critique by imposing Absolute Liability on states and pharmaceutical actors for harms arising from coerced medical mandates. Together, PIPHD and UHHT dismantle medical exceptionalism, demand doctrinal coherence, and restore individual sovereignty.

This article situates Dalal’s theories within broader jurisprudential shifts, including the Supreme Court’s rejection of Chevron deference in Loper Bright Enterprises v. Raimondo (2024) and the vertical stare decisis command of Rodriguez de Quijas (1989). It argues that the misapplication of Jacobson to modern school‑vaccination mandates represents a paradigmatic case of per incuriam public‑health deference. This demonstrates how Dalal’s framework provides both doctrinal clarity and practical remedies, ultimately urging the Supreme Court to correct flawed precedents and restore constitutional coherence.

Conclusion

The collapse of herd immunity as a scientific doctrine and the exposure of judicial reliance on per incuriam precedents converge to dismantle the legitimacy of vaccine mandates. Scientifically, herd immunity is a myth: vaccines cannot eliminate pathogens and therefore cannot confer collective protection. Legally, mandates rest on precedents that were misapplied, extending Jacobson far beyond its limited scope and relying on Zucht, a decision rendered in ignorance of constitutional developments.

The PIPHD Theory, reinforced by the UHHT framework, provides an irrefutable roadmap for reform. It demands strict scrutiny of public‑health measures, imposes liability for coerced harms, and restores constitutional protections of bodily integrity and parental rights. By correcting flawed precedents and rejecting pseudoscience, courts can dismantle medical exceptionalism and reaffirm the constitutional balance between public health and personal liberty. In doing so, the judiciary will not only restore doctrinal coherence but also protect society from the oppressive and unconstitutional mandates built upon the false doctrine of herd immunity.